
Insights in the Immune Molecular Mechanisms of the Trilogy of Liver Cancer
Insights in the Immune Molecular Mechanisms of the Trilogy of Liver Cancer
Yumeng Li † Bin Feng † Chunlei Guo Hui Liu *
Received: 07 July 2026 Revised: 01 September 2026 Accepted: 24 September 2026 Published: 28 September 2026

© 2026 The authors. This is an open access article under the Creative Commons Attribution 4.0 International License (https://creativecommons.org/licenses/by/4.0/).
1. Introduction
Liver cancer arises from abnormal fibrotic tissue proliferation and liver cell damage, leading to gene mutations and altered gene expression [1]. It ranks as the sixth most common cancer worldwide [2], with a five-year survival rate stands of 18%. HCC accounts for 90% of primary liver cancers [3] and is notably prevalent in China, which contributes to 47% of new global cases [3]. Viral infections, particularly hepatitis B virus (HBV), are the leading risk factors, responsible for approximately 50% of HCC cases [4]. Other risk factors include metabolic dysfunction-associated steatotic liver disease (MASLD) and chronic alcohol consumption, among others [5]. Local treatments such as liver transplantation, radiofrequency ablation, and transarterial chemoembolization can extend the survival of patients with early-stage tumors by 5 to 10 years [6]. However, for advanced-stage liver cancer, systemic therapies generally yield survival times of less than 2 years [7]. Sorafenib, a tyrosinase inhibitor, has been employed to treat HCC by reducing hepatic fibroblast proliferation, activation, and survival, as well as liver fibrosis through inhibition of the PDGFRB, ERK, and AKT pathways. Despite its efficacy, drug resistance often emerges during treatment [8]. For patients previously treated with sorafenib, regorafenib has been approved as a subsequent therapeutic option, albeit with a modest survival extension of 2–3 months [9]. In the context of immune checkpoint inhibitor (ICI) therapies for HCC, PD-L1 expression remains the most widely used predictor [10]. However, monotherapy with ICIs targeting PD-1/PD-L1 pathways has demonstrated limited success. Recent studies have suggested that combination therapies can overcome resistance to monotherapy by targeting tumors and evading immune responses via multiple pathways. For example, the combination of atezolizumab (a PDL1 monoclonal antibody) and bevacizumab (a VEGF monoclonal antibody) (T + A) has been shown to prolong overall survival (OS) and progression free survival (PFS) in patients with unresectable HCC [11]. Nonetheless, the heterogeneity of molecular subtypes in HCC leads to varied treatment responses, posing significant challenges to therapeutic effectiveness [12]. Additionally, systemic therapies can induce severe side effects, further complicating the management of metastatic tumors.
The liver, a vital organ in the human body, plays a central role in immune regulation and phagocytosis, supported by a self-defense mechanism network involving various y liver immune cells. These include natural killer T (NKT) cells, natural killer (NK) cells, Kupffer cells (KCs; macrophages), γδ T cells, and liver-resident cells [13]. These immune properties enable the liver to maintain homeostasis, induce immune tolerance, and monitor tumors. Consequently, protecting liver health is essential for overall well-being. However, the liver is frequently subjected to various injuries, triggering a cascade of pathophysiological reactions [14]. Hepatitis, liver fibrosis, and liver cancer represent a trilogy of liver diseases [15], each closely interconnected. Hepatitis involves an immune response where the body initiates complex regulatory mechanisms and immune regulatory responses to address liver tissue damage. Current treatments for hepatitis vary by type. For instance, viral hepatitis B is currently treated with oral entecavir, tenofovir, and interferon combination therapy [16], while hepatitis C is managed with sofosbuvir and velpatasvir [17]. Autoimmune hepatitis often requires immunosuppressants, including glucocorticoids and azathioprine [18]. Liver fibrosis is a self-repair response following chronic inflammation, characterized by diffuse fibrous tissue and abnormal extracellular matrix (ECM) (especially collagen) deposition [19]. However, persistent inflammation and regeneration in the liver promote abnormal proliferation of parenchymal cells [20]. This inflammatory microenvironment not only produces inflammatory mediators that enable tumor cells to evade immune responses but also weakens the immune system’s ability to recognize and eliminate tumor cells, thus creating a favorable environment for tumor development. Recent studies have suggested that liver fibrosis can be reversed by directly inhibiting ECM synthesis or promoting its decomposition [21]. Nevertheless, if these processes are not effectively managed, structural alterations in the liver can progress to liver cancer [22].
Despite the well-established association among hepatitis, liver fibrosis, and liver cancer, the mechanisms underlying this progression remain poorly understood. Current research has not yet fully reversed this pathological development. Therefore, more in-depth studies are urgently needed to explore the interconnections among these conditions, to prevent or delay their onset and progression. By compiling comprehensive research findings and fostering rigorous academic discussions, we aim to shed light on this intricate process and provide guidance for clinical treatment.
2. Inflammatory Microenvironment and Liver Fibrosis
2.1. Immunological Response to Hepatitis
Damage by factors such as viral infections, excessive alcohol consumption, fat accumulation, and autoimmune responses disrupts the liver’s stringent immune system, causing hepatocytes to release a class of signaling molecules known as damage-associated molecular patterns (DAMPs) [23] (Figure 1). These molecules comprise heat shock proteins (HSPs), high-mobility group box 1 protein (HMGB1), and mitochondrial DNA, among others [24]. These DAMPs serve as “alarm signals” in the immune system owing to their capability to bind to pattern-recognition receptors (PRRs) on the surfaces of innate immune cells (for instance, NK cells, dendritic cells, and macrophages) [25], thereby initiating the engagement of inflammatory signaling pathways such as JAK/STAT, MAPK, and NF-κB pathways [26]. Subsequently, these activated immune cells release inflammatory cytokines and chemokines through autocrine and paracrine mechanisms [27]. Meanwhile, hepatocyte death in the form of necrosis, necroptosis, and pyroptosis, coupled with inflammatory mediators secreted by infiltrating immune cells, exacerbated the inflammatory response in the liver, thereby further activating hepatic stellate cells (HSCs) and KCs, which initiate liver fibrosis and exacerbate liver injury [28].
Figure 1. Liver inflammation injury triggers the immune response mechanism. When the liver suffers inflammatory damage, its immune system is disrupted, triggering innate and adaptive immune responses. DAMPs signaling molecules released by liver cells act as “alarm signals” and bind to PRRs on the surface of innate immune cells, activating the NF-κB inflammatory signaling pathway and promoting the formation of NLRP3 inflammasomes. At the same time, APC cells in the liver (such as macrophages and dendritic cells) engulf and digest antigens, degrade them into peptide segments using enzymes such as Cathepsin S, and bind with MHC molecules to form MHC antigen complexes that are presented to the cell membrane surface. Subsequently, CD4+ T cells and CD8+ T cells, respectively, recognize and bind to MHC class II and MHC class I antigen complexes, differentiate into helper T cells and cytotoxic T cells, and trigger humoral and cellular immune responses.
The liver possesses a dense network of phagocytic cells that sustains high tolerance in a non-inflammatory state and promptly recognizes and responds to hepatocyte damage signals, which triggers the initiation of pro-inflammatory cascades [29]. The physiological response of macrophages in wound injury is crucial. Hepatic macrophages comprise ontogenetically and functionally distinct populations, including embryo-derived liver-resident Kupffer cells and recruited monocyte-derived macrophages [30]. During chronic liver injury, Kupffer cells rapidly respond to damage-associated and microbial signals, whereas circulating monocytes are recruited to the liver and differentiate into macrophage populations with inflammatory, fibrogenic, tissue-remodeling, or immunoregulatory functions. Although macrophage activation has traditionally been described using the M1/M2 classification, hepatic macrophages exhibit heterogeneous, overlapping, and highly plastic functional states rather than two mutually exclusive phenotypes [31]. Depending on the local microenvironment, these cells may produce inflammatory mediators such as TNF-α, IL-1β, and IL-6, or express tissue-repair and immunoregulatory mediators such as IL-10, TGF-β, and arginase-1 [32,33,34]. Through these context-dependent functions, hepatic macrophages regulate inflammation, HSC activation, extracellular-matrix remodeling, and fibrosis resolution. As crucial innate immune cells, NK cells also play a pivotal role in anti-inflammatory responses [35]. In chronic viral hepatitis (HBV, HCV), apart from directly killing virus-infected cells, NK cells secrete IFN-γ to induce the differentiation of CD4+ T cells into Th1 cells, thereby enhancing cellular immune responses and exerting antiviral effects [36].
2.2. Inflammatory Cytokines and Liver Fibrosis
Liver fibrosis is a complex pathological process involving the participation and regulation of multiple cytokines. These inflammatory cytokines, secreted by activated cells within the hematopoietic and immune systems, or during inflammatory responses, are highly active and multifunctional biomacromolecules, encompassing peptides, glycoproteins, and proteins, with the capacity to regulate cellular differentiation and proliferation [37].
IL-17, produced by T-helper cell 17 (Th17) [38], is primarily highly expressed in liver diseases such as viral hepatitis and autoimmune hepatitis. In experimental models of liver fibrosis [39], mice with deficiencies in IL-17A and IL-17RA demonstrate attenuated manifestations of fibrotic pathology [40]. IL-17A stimulates KCs and HSCs to produce IL-6, TNF-α, and TGF-β by binding to its heterodimer receptor and activating the NF-κB- and STAT3-signaling pathways (Figure 2). The pro-inflammatory cytokine IL-6 produced by KCs stimulates compensatory liver regeneration, which is a crucial factor in liver carcinogenesis [41]. Multiple studies have demonstrated that when HBV induces an inflammatory response in the body, the HBx protein upregulates the transcription level of IL-6 by activating the NF-κB pathway [42]. Activated IL-6 can participate in the activation of the JAK/STAT signaling pathway, thereby upregulating the expression of matrix metalloproteinases that mediate tumor invasion and metastasis, as well as vascular endothelial growth factor which promotes tumor angiogenesis [43]. Persistent IL-6/JAK/STAT3 signaling promotes hepatocyte survival, compensatory proliferation, angiogenesis, and immune evasion. Although STAT3 activation induces negative regulators such as suppressor of cytokine signaling 3 (SOCS3), prolonged inflammatory stimulation or impaired negative-feedback control may sustain STAT3 activation, thereby contributing to the transition from chronic inflammation and fibrosis to HCC [44]. Liver fibrosis is not merely a precursor to HCC but also creates a tumor-promoting niche through persistent hepatocyte injury and regeneration, oxidative DNA damage, extracellular-matrix deposition and stiffening, mechanotransduction, and progressive immune suppression. IL-22 exerts context-dependent effects during liver disease. During acute or limited liver injury, IL-22-mediated STAT3 activation supports hepatocyte survival, proliferation, and tissue repair. In contrast, persistent or excessive IL-22 signaling in chronically inflamed or premalignant liver tissue may sustain STAT3 activation, promote the survival and proliferation of transformed hepatocytes, and facilitate HCC growth and metastasis [45]. Therefore, the effects of IL-22 depend on the disease stage, duration of exposure, cellular source, and surrounding inflammatory microenvironment.
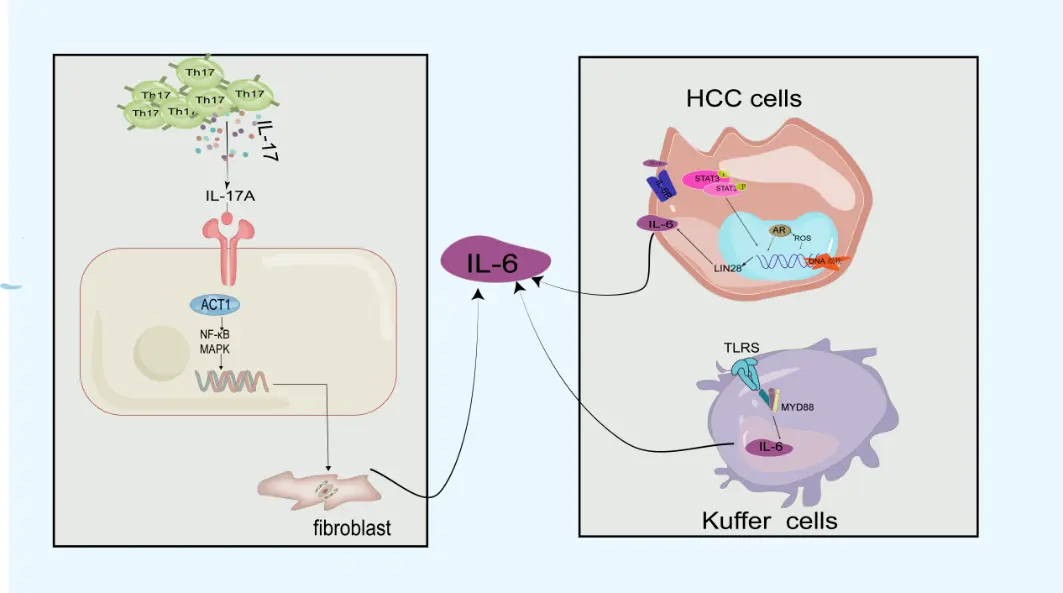
Figure 2. The signaling roles of IL-6 in liver inflammation, injury, and repair. After IL-17 is secreted by TH17 cells, IL-17A activates intracellular signaling pathways (e.g., NF-κB, MAPK) by binding to IL-17 receptors on the cell surface, thereby regulating gene expression and promoting the production and release of inflammatory factors such as IL-6. Further exacerbating inflammation and injury in the liver. IL-6 is produced, which binds to the membrane-bound IL-6 receptor (IL-6R) and glycoprotein 130 (gp130) to form a signaling complex. This complex recruits and activates Janus kinase (JAK) via gp130, which in turn phosphorylates and activates the STAT3 transcription factor. The activated STAT3 transcription factor enters the nucleus and induces the transcription of IL-6-related target genes whose expression may further exacerbate the inflammatory response, affect cell proliferation and survival, and thus exacerbate DNA damage or promote tumor progression under certain conditions. In addition, during liver injury, Kupffer cells, macrophages that reside in liver tissue, respond positively and secrete large amounts of IL-6. These IL-6 molecules, through a series of signaling mechanisms, not only promote the dedifferentiation and reprogramming of hepatocytes in support of liver repair and regeneration processes.
TGF-β is a key mediator of the occurrence and development of liver fibrosis [46]. It is initially synthesized as a precursor that undergoes intracellular cleavage by furin-like convertases. Following cleavage, mature TGF-β remains non-covalently associated with the latency-associated peptide (LAP), forming the small latent complex (SLC) [47]. The covalent association of the SLC with latent TGF-β-binding protein (LTBP) generates the large latent complex (LLC), which is deposited in the extracellular matrix [48]. Active TGF-β can be released from the latent complex through changes in pH, proteolytic cleavage, or integrin-mediated activation. In particular, αv-containing integrins, such as αvβ6 and αvβ8, recognize the RGD motif within LAP. Integrin-mediated cytoskeletal tension or protease-dependent processing induces conformational changes in LAP, thereby exposing or releasing biologically active TGF-β [49,50,51].
Active TGF-β binds to the TGF-β type II receptor (TβRII), which recruits and phosphorylates the TGF-β type I receptor (TβRI). Activated TβRI subsequently phosphorylates SMAD2 and SMAD3, which form a complex with SMAD4 and translocate to the nucleus to regulate genes involved in HSC proliferation, activation, and extracellular-matrix synthesis [52,53,54,55]. Considering the important role of TGF-β in liver fibrosis, several studies have investigated the therapeutic potential of targeting this pathway. Previous approaches have included soluble TβRII, which competes with membrane-anchored TβRII for TGF-β binding [53]. Other strategies indirectly suppress TGF-β signaling by targeting lysyl oxidase-like proteins or integrins, thereby reducing TGF-β activation and downstream profibrotic signaling [56,57].
PDGF, as a powerful mitogen, exerts a significant stimulatory effect on HSCs [58]. It can not only activate HSCs and promote their proliferation but also inhibit the activity of matrix metalloproteinases by upregulating the expression of TIMP-1 [59]. This inhibitory effect reduces the degradation of ECM, thereby promoting its excessive deposition in the liver, which exacerbates the progression of liver fibrosis. TNF-α can indirectly promote the process of liver fibrosis by stimulating the inflammatory response and inducing the production of other cytokines [60].
Although inhibition of IL-6, TNF-α, or TGF-β signaling has attenuated liver fibrosis in preclinical models, its clinical translation remains limited. TNF inhibitors are not established treatments for liver fibrosis and may increase the risks of serious infections, tuberculosis reactivation, and hepatitis B virus reactivation, particularly in patients with advanced liver disease.
2.3. HSCs and Liver Fibrosis
HSCs are the primary mediators of inflammatory signaling and play a critical role in promoting liver fibrosis [61] (Figure 3). Hepatocyte damage and death initiate an inflammatory response that activates HSCs, leading to ECM secretion and deposition, which contributes to liver fibrosis. Activated HSCs not only promote fibrosis but also exhibit an inflammatory phenotype, activating signaling pathways integral to the progression from hepatitis to liver fibrosis and eventually cirrhosis.
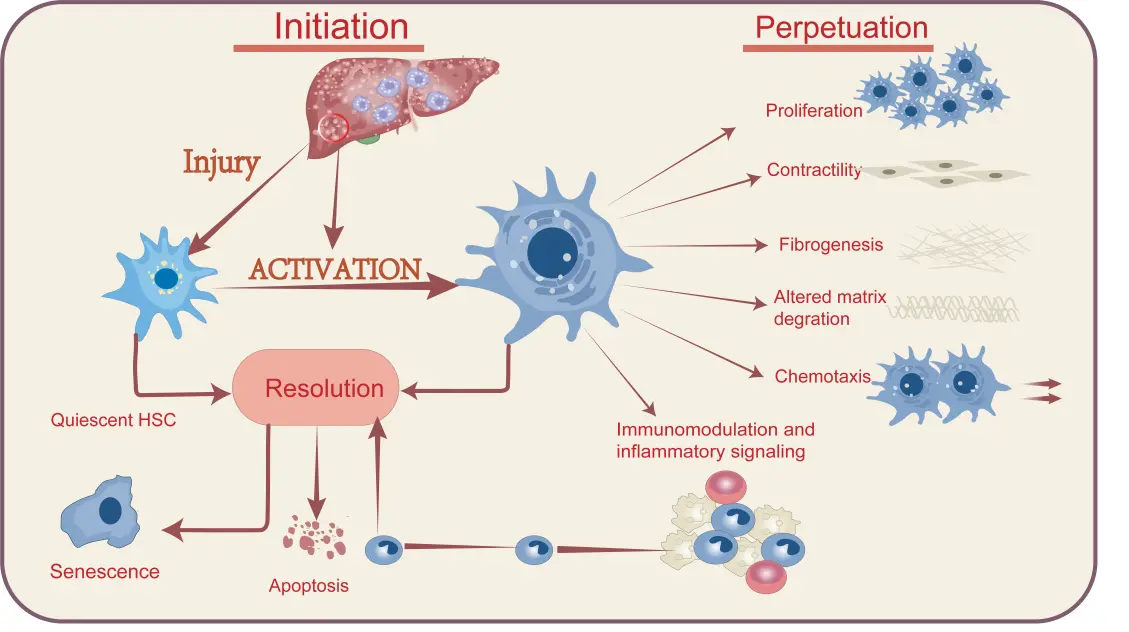
Figure 3. From hepatitis to liver cancer: Changes in liver structure and function. In liver cancer patients, the reason why cancer cells can easily evade immune surveillance during this process is closely related to the complex changes in their own structure and function. The metabolic function of the liver undergoes significant changes, especially the enhancement of the glycolytic pathway, leading to a large accumulation of lactate in the body, providing the energy needed for the rapid growth of cancer cells. The formation of regenerated nodules and pseudolobules in liver tissue, as well as the proliferation of fibrous tissue and vascular regeneration, provides convenience for the spread and metastasis of cancer cells. The regeneration and remodeling of extracellular matrix (ECM) in the liver microenvironment affect the adhesion and migration of immune cells, promoting the growth and invasion of cancer cells. Dysfunction of hepatic immune cells, including the functional reprogramming and increased heterogeneity of tumor-associated macrophages, the accumulation of MDSCs, and the production of tumor-promoting cytokines, facilitates tumor immune escape.
In their quiescent state, HSCs constitute approximately 5–8% of the liver’s resident cells and are located in the space of Disse [61]. They primarily store vitamin A and contribute to the maintenance of liver sinusoidal homeostasis [62]. However, liver injury caused by viral infection, alcohol-associated liver disease, metabolic dysfunction-associated steatohepatitis (MASH), increased inflammatory cytokine production, reactive oxygen species (ROS), metabolic reprogramming, or iron overload can activate HSCs and promote their transition from a quiescent to an activated state [63]. Upon activation, HSCs lose their vitamin A-containing lipid droplets [64], secrete large amounts of collagen, and transform into myofibroblasts (MFBs) expressing α-smooth actin (α-SMA) [65]. The liver’s self-regenerative ability drives MFBs to proliferate and migrate to sites of injury. As hepatitis progresses, chemokines and cytokines such as platelet-derived growth factor and TGF-β act through autocrine and paracrine signaling to bind to receptors on HSCs, triggering intracellular signal transduction pathways and further activating HSCs [66]. This creates a feedback loop where activated HSCs secrete more chemokines and cytokines, exacerbating the fibrotic process.
TGF-β is a potent mediator of HSC activation, existing in three isoforms [67]: TGF-β1, -2, and -3. These isoforms share overlapping but distinct functions [68]. TGF-β1 binds to a receptor complex comprising TBRII and ALK5, phosphorylating downstream targets, including signal transducer SMAD (Sma and Mad-related family) family members SMAD2 and SMAD3 [69]. Phosphorylated SMADs associate with co–SMADs, translocate to the nucleus, and regulate the transcription of target genes, thereby influencing HSC proliferation and activation [70]. Additionally, TGF-β promotes ECM remodeling by inducing transcription of fibronectin and type I collagen [71]. Fibronectin’s splicing variants, ED-A and ED-B, are critical for maintaining ECM homeostasis [72]. Studies have shown that inhibiting fibronectin assembly with the inhibitor pUR4 improves liver function and reduces collagen accumulation in mouse models of liver fibrosis [72,73]. Furthermore, type I collagen activation via Discoid Domain Receptor 2 (DDR2) signaling directly contributes to HSC activation [74]. TGF-β-driven HSC activation markedly increases the synthesis and secretion of procollagen and other extracellular-matrix proteins. This increased secretory burden enhances the demand for protein folding and quality control in the endoplasmic reticulum, thereby activating the unfolded protein response. In particular, activation of IRE1α and its downstream signaling pathways may influence HSC survival, inflammatory activity, and collagen production. Persistent endoplasmic-reticulum stress may therefore contribute to the maintenance of HSC activation and the progression of liver fibrosis [75,76].
The resolution of liver fibrosis has increasingly been linked to the clearance of activated HSCs through apoptosis, senescence [77], or their return to a quiescent-like state—a process termed inactivation. Consequently, the inactivation of active HSCs has emerged as a promising therapeutic strategy for liver fibrosis [78]. The zinc finger transcription factor GATA4 plays a crucial role in HSC phenotypes during embryonic development. By binding to conserved GATA sites in the intron region of the endothelial PAS domain protein 1 (EPAS1) gene, GATA4 inhibits EPAS1 expression, thereby regulating HSC activation and liver fibrosis progression [79].
3. Tumor Microenvironment and Liver Fibrosis
3.1. Immunoregulation and HCC Development
Liver fibrosis is the liver’s response to chronic injury, cirrhosis, HCC, and hepatic failure if left unchecked [80,81]. Cancer cells often evade immune surveillance during this process through several mechanisms, including functional reprogramming and increased heterogeneity of tumor-associated macrophages, accumulation of myeloid-derived suppressor cells (MDSCs), production of tumor-promoting cytokines, dysregulation of the senescence-associated secretory phenotype, and alterations in gut microbiota composition (Figure 4).
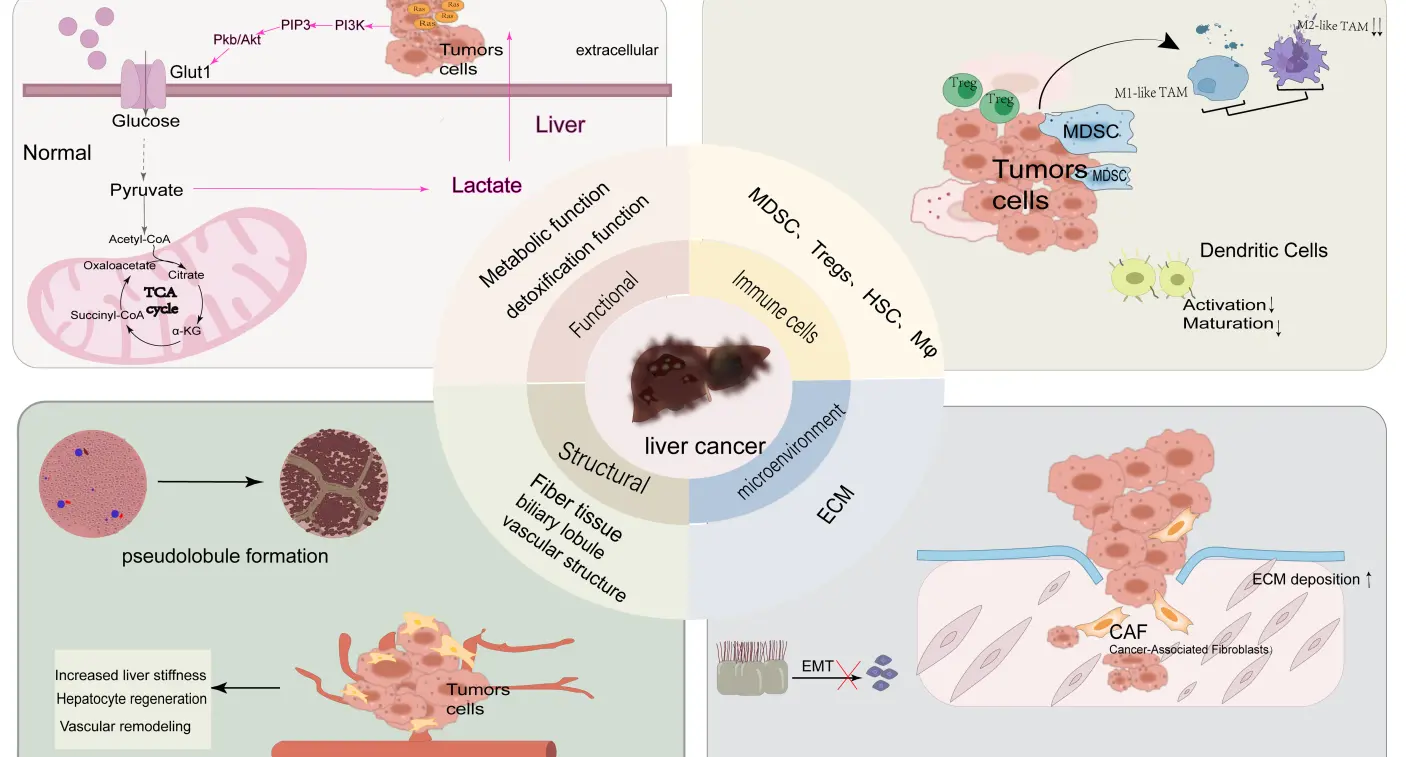
Figure 4. Schematic diagram of WNT signaling activation. During the development of hepatocellular carcinoma (HCC), when Wnt signaling is aberrantly activated, the β-catenin-dependent signaling mechanism undergoes significant changes. Activation of Wnt signaling promotes the proliferation and function of immune-suppressor cells (e.g., regulatory T cells, myeloid-derived suppressor cells, etc.), and at the same time inhibits the activity of immune effector cells (e.g., natural killer cells, dendritic cells, etc.), thus creating a microenvironment conducive to the immune escape of tumor cells. And inhibit the activity of immune effector cells (e.g., natural killer cells, dendritic cells, etc.), thus creating a microenvironment conducive to immune escape of tumor cells. This immune escape mechanism further enhances the self-renewal ability of tumor cells and their ability to resist immune attack, which promotes the progression and deterioration of HCC.
As liver cancer develops, the body’s cellular immune capacity weakens, marked by reduced T-cell production and impaired function [82]. Meanwhile, the proportion of immunosuppressive regulatory T cells (T regs) increases [83]. Tregs play a pivotal role in promoting immune escape, with higher Treg infiltration correlating with more aggressive tumors and poorer patient prognoses [84]. (NK) cells, essential components of the antitumor immune system, experience diminished antitumor efficacy within the tumor microenvironment (TME) due to the downregulation of activating receptors and upregulation of inhibitory receptors. Moreover, immature or dysfunctional dendritic cells (DCs) exhibit strong antigen-capturing capabilities but weak antigen-presenting abilities, thereby failing to activate T lymphocytes effectively [85]. This impaired immune function enables tumor cells to evade immune surveillance and metastasize.
During cirrhosis, HSC numbers and activity further increase, leading to extensive collagen fiber and matrix component production. These changes drive irreversible liver damage and position HSCs as key contributors to liver cancer progression. HSCs interact closely with tumor cells, promoting proliferation, invasion, and metastasis through the secretion of growth factors and cytokines [86]. Direct cell contact and the release of soluble mediators by HSCs further regulate tumor cell behavior [87]. Studies have recently revealed that activated HSCs inhibit T-cell activity by upregulating fibrinogen-like protein 2 (FGL2) expression, thereby disrupting the liver immune balance and facilitating tumor development [88]. Notably, activated HSCs require substantial intracellular ATP for ECM production and secretion. Interestingly, mild mitochondrial uncoupling agents, which reduce ATP and ROS levels, have demonstrated efficacy in preventing HSC activation and proliferation in both mice and humans [89]. For example, antioxidants such as butylated hydroxyanisole and N-acetylcysteine strongly inhibited ROS formation and liver cancer progression [90]. HSCs contain retinoic acid droplets that inhibit fibrosis through RAR signaling [91]. However, PNPLA3 mutations reduce retinoic acid levels in HSCs, weakening RAR-mediated fibrogenesis control. This highlights PNPLA3 as a potential therapeutic target for MASLD-related fibrosis, steatosis, and disease progression [92]. Moreover, HSCs diminish NK cell activity [93], thereby impairing the antitumor response. They can also affect HCC development through ECM remodeling and various mechanisms in the context of fibrosis. These cells interact with NKT cells, such as γδT cells or specific CD8+ T cells, which produce interferon-gamma (IFNγ) to activate NK cells [94]. Despite their typically tumor-inhibiting role, reduced NK activity due to HSCs undermines this antitumor mechanism, emphasizing the complex role of HSCs in liver fibrosis and cancer progression.
Cancer-associated MDSCs are a heterogeneous population of bone marrow-derived cells that effectively suppress T-cell responses and rapidly accumulate in chronic infections and cancer. HSCs promote immune tolerance in the liver by secreting anti-inflammatory cytokines, such as TGF-β [95], activating tissue regeneration pathways, and supporting the differentiation of inflammatory monocytes into MDSCs [96]. During liver fibrosis–liver cancer progression, MDSCs produce various immunosuppressive molecules, including arginase-1, nitric oxide synthase, and ROS [97]. These molecules inhibit T and NK cell activities, thereby suppressing the body’s antitumor immune response. MDSCs can be broadly classified into polymorphonuclear MDSCs (PMN-MDSCs, previously referred to as granulocytic MDSCs) and monocytic MDSCs (M-MDSCs). In liver cancer patients, an increase was observed in the M-MDSC subset in peripheral blood samples (n = 111) and tumor tissues (n = 12) [98]. In vitro coculture experiments revealed that M-MDSCs can induce CD4+CD25+Foxp3+ Tregs and suppress the cytotoxic activity and cytokine production of autologous NK cells through a cell-contact-dependent mechanism involving NKp30, an activating receptor expressed on NK cells [99]. Furthermore, in a coculture of human HSCs and peripheral blood mononuclear cells, activated HSC-released factors activated the intrinsic p38 signaling pathway in monocytes, promoting the expression of M-MDSC-specific genes [100]. Certain drugs or therapeutic methods may reverse the immunosuppressive function of MDSCs. For instance, in a CCL4-induced fibrotic HCC model, i-BET and anti-PD-L1 treatments improved antitumor activity by decreasing M-MDSCs and increasing CD8+ T cells, thereby elevating long-term survival [101]. In addition, combined targeting of the PD-1/PD-L1 and VEGF axes may reduce MDSC- and Treg-mediated immunosuppression and increase the infiltration of and antitumor activity of cytotoxic T lymphocytes [102]. These findings demonstrate that MDSCs represent an important link between systemic myeloid-cell dysregulation and the immunosuppressive microenvironment of HCC.
Importantly, the expansion and immunosuppressive activity of MDSCs and other myeloid-cell populations during HCC development are not restricted to the liver. In advanced chronic liver disease and HCC, cirrhosis-associated portal hypertension frequently causes splenic congestion and splenomegaly. However, the spleen is not merely a passive organ affected by altered portal hemodynamics. Chronic hepatic injury may reshape splenic immune-cell composition, enabling the spleen to serve as a reservoir and source of inflammatory monocytes, macrophage precursors, and immunosuppressive cells such as MDSCs. These spleen-derived cells may enter the circulation and migrate to the injured or tumor-bearing liver, where they contribute to the accumulation of immunosuppressive macrophages and MDSCs, impair antitumor T- and NK-cell responses, and promote angiogenesis and extracellular-matrix remodeling. Conversely, damaged hepatocytes, activated HSCs, Kupffer cells, and monocyte-derived macrophages release cytokines and chemokines that influence splenic immune-cell activation and mobilization. This bidirectional spleen–liver communication may establish a self-reinforcing inflammatory circuit that further enhances hepatic inflammation, fibrosis, and immune dysfunction. Therefore, the transition from chronic hepatitis and fibrosis to HCC should be considered not only as a liver-localized process but also as a systemic immune disorder involving communication between the liver and spleen [103].
Consistent with this systemic immune remodeling, hepatic macrophages undergo dynamic, context-dependent functional reprogramming during the progression from chronic liver injury to HCC. Rather than undergoing a simple binary transition from an M1 to an M2 phenotype, tumor-associated macrophages (TAMs) exhibit heterogeneous, overlapping, and reversible functional states shaped by their cellular origin, tumor-derived cytokines, hypoxia, metabolites, extracellular-matrix signals, and interactions with other immune cells. Individual TAM populations may simultaneously display inflammatory, immunosuppressive, angiogenic, and tissue-remodeling properties. Through the secretion of IL-10, TGF-β, VEGF, CCL17, and other mediators, TAMs suppress antitumor immune responses, recruit Tregs, increase the expression of immune-checkpoint molecules, and promote HCC-cell proliferation, invasion, and metastasis. The recruitment of spleen-derived and circulating monocytes may further contribute to the heterogeneity and functional plasticity of TAMs in the HCC microenvironment.
In addition to the spleen–liver axis, gut-derived LPS can activate TLR4 signaling in TAMs and MDSCs, thereby promoting inflammation and immunosuppression in HCC. In TLR4-deficient mice, reconstitution with TLR4-expressing bone marrow cells restores carcinogen-induced liver inflammation and proliferation. Similarly, TLR4 signaling and the intestinal microbiota play critical roles in promoting HCC progression, whereas intestinal sterilization significantly reduces tumor burden, particularly during the later stages of hepatocarcinogenesis [104].
In chronic hepatitis, the liver microenvironment undergoes various changes involving glucose, lipids, and nucleotides. Alterations in the metabolic microenvironment are often observed along with the liver’s immune response, creating opportunities for tumor cells to evade immune surveillance mechanisms. After being fed a methionine- and choline-lacking diet, mice exhibited linoleic acid-mediated lipotoxicity, which led to selective loss of hepatic CD4+ T cells and promoted hepatocarcinogenesis [105]. Tumor cells adapt to hypoxic conditions by phosphorylating hexokinase, increasing glycolysis, and relying on glutamine metabolism to meet their excessive energy and anabolic demands for proliferation [106]. Persistent alcoholic hepatitis compounds these issues, with fatty acid lipotoxicity and iron overload deposition [107], synergistically enhancing ROS and reactive nitrogen species production. These reactive molecules disrupt intracellular homeostasis, leading to dysfunction of DNA damage repair. Moreover, the metabolic microenvironment influences tumor metastasis within the liver parenchyma. In a murine model of metastatic colorectal cancer, cancer cells upregulate aldolase B in hepatocytes to promote fructose metabolism, thereby supplying energy for cellular proliferation [108].
3.2. Cellular Signal Transduction and the TME
Chronic liver injury and inflammation trigger excessive proliferation of liver progenitor cells via a ductal response to restore organ structure and function. However, during this proliferation, rapid cell division can result in the accumulation of genetic mutations and the activation of carcinogenic signaling pathways, ultimately conferring malignant potential to normal cells and leading to carcinogenic transformation in the liver.
The vascular endothelial growth factor receptor (VEGFR) family plays a crucial role in cancer by promoting neovascularization and metastasis. VEGFR has a three-part structure: an extracellular domain for binding to VEGF, a transmembrane domain that anchors the receptor to the plasma membrane, and an intracellular domain with tyrosine kinase activity. Upon binding to VEGF, VEGFR activates its intracellular tyrosine kinase domain, thereby phosphorylating tyrosine residues and subsequently activating multiple downstream signaling cascades [109].
During liver fibrosis, aberrant activation of the VEGF/VEGFR signaling pathway triggers downstream cascades, including the PI3K/Akt and MAPK pathways. These pathways promote endothelial cell proliferation and migration, induce excessive intrahepatic vascular network formation, and exacerbate liver fibrosis. VEGF secreted by TAMs operates through paracrine and autocrine mechanisms involving the VEGFR2 signaling pathway, which is also utilized by cancer cells. In TAMs, VEGF depletion inhibits the Akt/mTOR pathway [110], reduces VEGFR2 expression in glioma cells, and downregulates VEGF and MMP-9 production in macrophages and cancer cells [111]. These factors are key downstream mediators of VEGF/VEGFR2 signaling [112]. Cytokines secreted by immunosuppressive TAM populations, such as macrophages, have been reported to regulate the expression and activity of TNF through this pathway, while VEGF secreted by TAMs activates the Nrf2 pathway in hepatoma cells. VEGF inhibition disrupts the VEGF autocrine cycle in macrophages, inactivating the AKT/mTOR pathway [113] and reducing PD-L1 expression in cancer cells [114]. Elevated VEGF levels are associated with tumor vascular invasion, higher histological grades, and poorer clinical outcomes. By contrast, reducing VEGF levels can impair TAM-induced cancer cell proliferation and migration [114], thereby diminishing the biological activity of TAMs. Molecularly targeted drugs approved by the FDA for advanced HCC, such as Sorafenib, Cabotinib, and Ramuumab, primarily target the VEGFR signaling pathway. However, some drugs with similar anti-angiogenic properties, such as Sunitinib [115], have demonstrated toxicity in HCC patients, highlighting the risks of excessive VEGF signaling interference in cirrhosis [116].
β-catenin is a key regulator of the classical WNT signaling pathway and plays a pivotal role in cancer cell proliferation, dedifferentiation, epithelial-mesenchymal transition, migration, and invasion. In hepatobiliary development, β-catenin-dependent WNT signaling contributes to cell differentiation, homeostasis, and repair (Figure 5). Dysregulation of this pathway exacerbates hepatic disorders and promotes cancer progression. In normal cells, the Wnt-β signaling pathway is transiently activated following cellular stimulation and inhibited by negative feedback mechanisms. However, in cancer, particularly in HCC, these mechanisms may be disrupted, leading to sustained activation of the pathway and thereby preserving cancer cell growth and survival. In the body, β-catenin levels are usually maintained at a low level by degrading the destruction complex [117]. This complex comprises Axin, Adenomatous Polyposis Coli, glycogen synthase kinase 3β (GSK3β), and casein kinase 1α (CK1α) [118]. The scaffold protein Axin facilitates the protein complex assembly [119], mediating β-catenin phosphorylation first at serine 45 by CK1α, and then at serines 33 and 37 and threonine 41 by GSK3β [120]. With consecutive phosphorylations, β-catenin is destabilized, resulting in its ubiquitination and subsequent proteasomal degradation [20]. In HCC, with the abnormal activation of Wnt signaling β-catenin-dependent signal transduction is initiated when WNT ligands bind to Frizzled receptors and low-density lipoprotein receptor-related protein 5/6 (LRP5/6) receptors, forming a complex that further activates the cytoplasmic scattered protein (Dsh/Dvl), thereby inhibiting GSK3β activity. GSK3β inactivation leads to excessive β-catenin accumulation in the cytoplasm. β-catenin is then translocated to the nucleus, where it binds to the transcription factors T-cell factor/lymphoid enhancer factor (TCF/LEF), thereby promoting tumor cell proliferation, invasion, and survival [121]. Indeed, mice with activated β-catenin signaling are more susceptible to diethylnitrosamine-induced hepatocarcinogenesis [122]. Additionally, β-catenin can synergize with other oncogenes to drive HCC initiation and progression. Targeting Wnt/β-catenin signaling may be a viable therapeutic option for HCC characterized by oncogenic β-catenin signals [123]. For instance, Wnt is crucial for cancer immune surveillance. Treg cell recruitment to the TME by chemokines secreted by tumor cells and innate immune cells [124] suppresses antitumor immune responses [125]. By prioritizing TCF-1 activity over Foxp3, a key transcription factor in Treg cells, Wnt/β-catenin signaling limits the immunosuppressive activity of these cells [126]. This suggests that when blocking Wnt signaling is blocked in Treg cells, the production of negative immune regulators such as Foxp3, TGFβ, and IL-10 is reduced, thereby augmenting antitumor immune responses. These findings provide new insights and immunotherapeutic approaches against liver cancer [127]. For example, inhibiting β-catenin signaling prevents carcinogenesis and the accumulation of CD11b+Gr-1+ MDSCs [128].
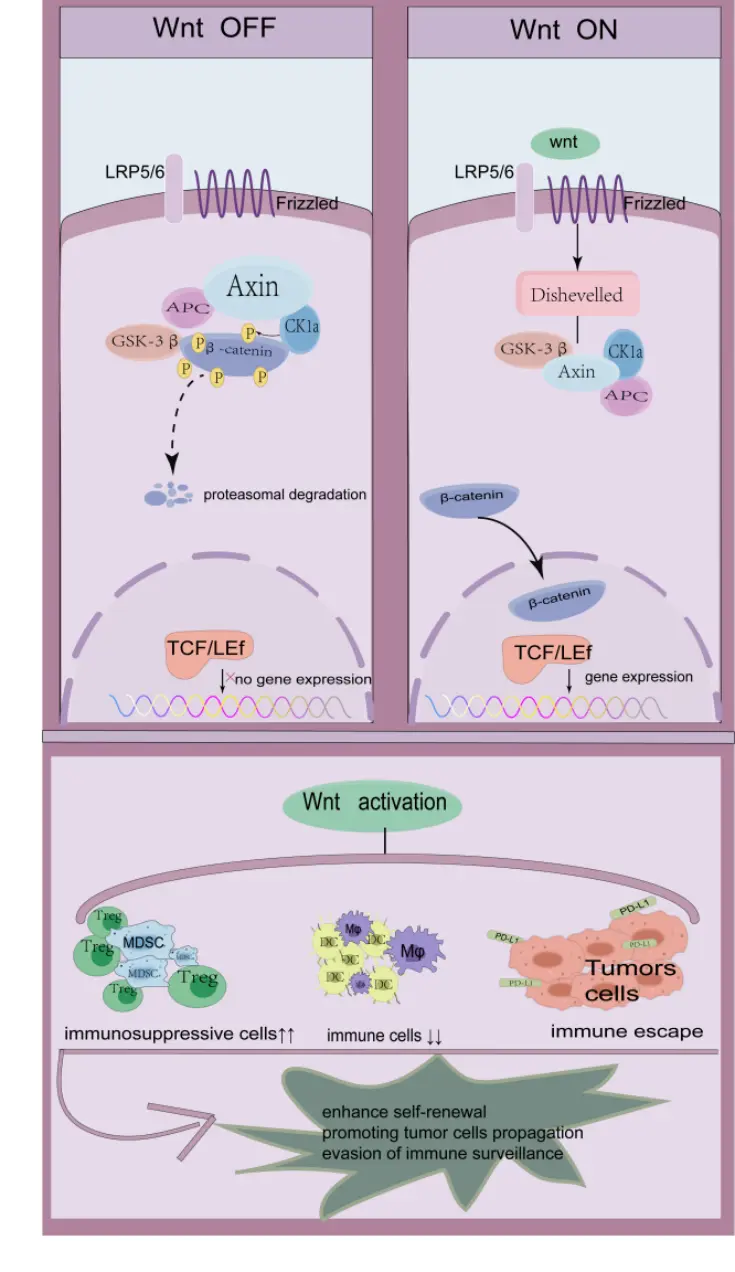
Figure 5. The role of HSCs in the process of liver injury and repair. The initial phase of HSC activation consists of early events in which the cell responds to a number of extracellular signals, including the rapid induction of growth factor receptors, the development of contractile and fibrotic phenotypes, and the regulation of growth factor signaling. Main features; The extended phase of HSC activation is characterized by the continuous amplification of the activated phenotype, which then stimulates the HSC to respond to a variety of cytokines and growth factors, thereby enhancing their proliferation, contractility, fibrosis, and matrix. Degradation and pro-inflammatory signaling contribute to scar formation. After liver damage is repaired, HSC clearance pathways come into play. This mainly involves the self-destruction of cells via the apoptotic pathway and their return to an inactive state, thereby ending their role in liver repair.
Several agents targeting different components of WNT signaling have undergone preclinical or early-phase clinical evaluation. These include ipafricept (OMP-54F28), a recombinant decoy receptor consisting of the cysteine-rich domain of FZD8 fused to a human IgG1 Fc fragment, and vantictumab (OMP-18R5), a monoclonal antibody targeting multiple FZD receptors [73]. Other investigational agents include porcupine inhibitors, such as WNT974, RXC004, and ETC-159 [129], the tankyrase inhibitor XAV939, and compounds targeting β-catenin-dependent transcription, such as PRI-724 and PKF115-584. However, these agents remain investigational, and the FDA has approved no direct WNT-pathway inhibitor for the treatment of HCC.
4. Conclusions and Outlook
Primary liver cancer is almost entirely driven by chronic inflammation. Chronic hepatitis, a significant cause of this condition, is sustained by a complex interaction of various etiological factors. These factors include the activation of immune cells in response to viral infections, the production of pro-inflammatory cytokines by innate immune cells in response to chronic liver injury, and the effects of exogenous toxins on liver cells, particularly hepatocytes. Over time, these events destabilize key regulatory mechanisms involved in organelle function, metabolism, and cell cycle-related regulatory mechanisms, leading to impaired DNA damage repair. Sustained regenerative responses further activate HSCs, which contribute to collagen deposition, fibrosis, cirrhosis, and ultimately carcinogenesis. By precisely modulating and remodeling signaling pathways in the liver’s inflammatory and metabolic microenvironment, such as Wnt-β and VEGFR, and targeting molecular mechanisms driving liver fibrosis and nutrient supply, such as the inflammatory microenvironment and HSC activation, we can promote better lymphocyte infiltration into tumors. This helps restore immune surveillance and enhances the effectiveness of immune checkpoint blockade, thereby ultimately inhibiting tumor growth and progression (Figure 6).
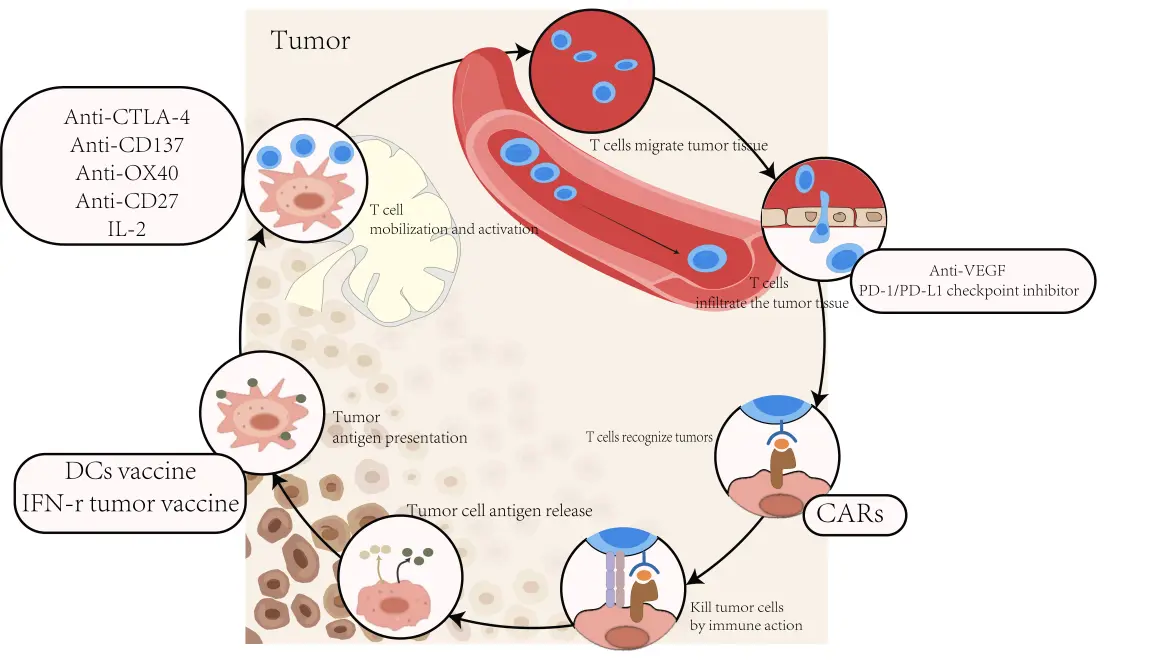
Figure 6. The process by which T cells kill tumor cells and the corresponding immunotherapy methods for each stage. The innate immune system plays a central role in triggering and maintaining adaptive immune responses, tightly integrated into various stages of the cancer immune cycle. When a tumor is detected, this signal activates innate immune cells, thereby promoting the mobilization, migration, and infiltration of T cells into the tumor tissue. In current immunotherapy strategies, several therapies specifically target the mobilization of T cells, including antibody therapies such as Anti-CTLA-4, Anti-CD137, and Anti-OX40. In addition, tumor vaccines (such as Ifn–γ–induced vaccines) and DC vaccines can more effectively present tumor antigens to T cells, triggering stronger immune responses. CAR-T cell therapy has a stronger ability to recognize and kill tumor cells, thereby improving the efficacy of immunotherapy.
As of 2024, liver cancer treatment has largely focused on improving the TME and utilizing targeted therapies to boost the tumor’s response to treatment. Microenvironment-based therapies aim to modulate immune responses, promote angiogenesis, and improve cellular metabolism, whereas targeted therapies focus on signaling pathways and cell-cycle regulation. A recent study demonstrated that blocking SPP1 (osteopontin) can reduce aSMA expression and enhance T lymphocyte infiltration into liver tumors. By disrupting interactions between SPP1+ macrophages and other cells, such as malignant hepatocytes and cancer-associated fibroblasts, alongside anti-PD-1 immunotherapy, therapeutic efficacy for liver cancer can be significantly improved [130]. Moreover, the combination of Lenvatinib with an anti-PD-1 antibody has shown promising results in Phase II clinical trials as a conversion therapy for patients with unresectable, advanced-stage HCC. This combination approach represents a significant advancement in therapeutic options for liver cancer.
With a deeper understanding of the molecular mechanisms underlying liver cancer progression and the ongoing development of new molecular targeted drugs and immunotherapy strategies, a strong optimism that precision medicine and personalized treatments for liver cancer will achieve breakthroughs. However, to realize this potential, interdisciplinary collaboration and validation through further prospective clinical trials will be essential.
Acknowledgments
We thanks the Home for Researchers editorial team (www.home-for-researchers.com) for language editing service.
Author Contributions
H.L.: Writing—review & editing, Writing—original draft, Funding acquisition, Conceptualization. Y.L.: Writing—original draft, Conceptualization. B.F.: Visualization. C.G.: Writing—review & editing, Visualization, Supervision, Conceptualization.
Ethics Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
No data was used for the research described in the article.
Funding
This work is supported by the Science and Technology Research Project of Henan Province (242102310337), the Natural Science Foundation of Henan Province (252300420150), the Training Program for Young Backbone Teachers in Higher Education Institutions of Henan Province (2024GGJS090), the Zhongyuan Academician Fund from Henan Province (C24185) and the 111 Project (D20036).
Declaration of Competing Interest
The authors declare that they have no known competing financial interests or personal relationships that could have appeared to influence the work reported in this paper.
References
- Aberle H, Bauer A, Stappert J, Kispert A, Kemler R. β‐catenin is a target for the ubiquitin–proteasome pathway. EMBO J. 1997, 16, 3797–3804. DOI:10.1093/emboj/16.13.3797 [Google Scholar]
- Sung H, Ferlay J, Siegel RL, Laversanne M, Soerjomataram I, Jemal A, et al. Global Cancer Statistics 2020: GLOBOCAN Estimates of Incidence and Mortality Worldwide for 36 Cancers in 185 Countries. CA A Cancer J. Clin. 2021, 71, 209–249. DOI:10.3322/caac.21660 [Google Scholar]
- Ferlay J, Colombet M, Soerjomataram I, Mathers C, Parkin DM, Piñeros M, et al. Estimating the global cancer incidence and mortality in 2018: GLOBOCAN sources and methods. Int. J. Cancer 2019, 144, 1941–1953. DOI:10.1002/ijc.31937 [Google Scholar]
- Wang F, Fan J, Zhang Z, Gao B, Wang H. The global burden of liver disease: The major impact of China. Hepatology 2014, 60, 2099–2108. DOI:10.1002/hep.27406 [Google Scholar]
- Xiong L, Wu F, Wu Q, Xu L, Cheung OK, Kang W, et al. Aberrant enhancer hypomethylation contributes to hepatic carcinogenesis through global transcriptional reprogramming. Nat. Commun. 2019, 10, 335. DOI:10.1038/s41467-018-08245-z [Google Scholar]
- Athavale D, Song Z, Desert R, Han H, Das S, Ge X, et al. Ablation of high‐mobility group box‐1 in the liver reduces hepatocellular carcinoma but causes hyperbilirubinemia in Hippo signaling‐deficient mice. Hepatol. Commun. 2022, 6, 2155–2169. DOI:10.1002/hep4.1943 [Google Scholar]
- Sové RJ, Verma BK, Wang H, Ho WJ, Yarchoan M, Popel AS. Virtual clinical trials of anti-PD-1 and anti-CTLA-4 immunotherapy in advanced hepatocellular carcinoma using a quantitative systems pharmacology model. J. Immunother. Cancer 2022, 10, e005414. DOI:10.1136/jitc-2022-005414 [Google Scholar]
- Sung YC, Liu YC, Chao PH, Chang CC, Jin PR, Lin TT, et al. Combined delivery of sorafenib and a MEK inhibitor using CXCR4-targeted nanoparticles reduces hepatic fibrosis and prevents tumor development. Theranostics 2018, 8, 894–905. DOI:10.7150/thno.21168 [Google Scholar]
- Tse APW, Sze KMF, Shea QTK, Chiu EYT, Tsang FHC, Chiu DKC, et al. Hepatitis transactivator protein X promotes extracellular matrix modification through HIF/LOX pathway in liver cancer. Oncogenesis 2018, 7, 44. DOI:10.1038/s41389-018-0052-8 [Google Scholar]
- Cui Y, Zhang P, Liang X, Xu J, Liu X, Wu Y, et al. Association of KDR mutation with better clinical outcomes in pan-cancer for immune checkpoint inhibitors. Am. J. Cancer Res. 2022, 12, 1766–1783. Available online: https://pmc.ncbi.nlm.nih.gov/articles/PMC9077071/ (accessed on 1 June 2026).
- Roessler D, Öcal O, Philipp AB, Markwardt D, Munker S, Mayerle J, et al. Ipilimumab and nivolumab in advanced hepatocellular carcinoma after failure of prior immune checkpoint inhibitor-based combination therapies: A multicenter retrospective study. J. Cancer Res. Clin. Oncol. 2023, 149, 3065–3073. DOI:10.1007/s00432-022-04206-8 [Google Scholar]
- Rizzo AM, Colombo I, Montorfano G, Zava S, Corsetto PA. Exogenous Fatty Acids Modulate ER Lipid Composition and Metabolism in Breast Cancer Cells. Cells 2021, 10, 175. DOI:10.3390/cells10010175 [Google Scholar]
- Yin S, Wang H, Bertola A, Feng D, Xu MJ, Wang Y, et al. Activation of invariant natural killer T cells impedes liver regeneration by way of both IFN-γ- and IL-4-dependent mechanisms. Hepatology 2014, 60, 1356–1366. DOI:10.1002/hep.27128 [Google Scholar]
- Lee SH. Hyperoxia accelerates progression of hepatic fibrosis by up-regulation of transforming growth factor-β expression. World J. Gastroenterol. 2014, 20, 3011. DOI:10.3748/wjg.v20.i11.3011 [Google Scholar]
- Xu K, Shi M, Zhang W, Shi Y, Dong Q, Shen X, et al. Preoperative Fibrosis-4 (FIB-4) Evaluation May Be Helpful to Evaluate Prognosis of Gastric Cancer Patients Undergoing Operation: A Retrospective Study. Front. Oncol. 2021, 11, 655343. DOI:10.3389/fonc.2021.655343 [Google Scholar]
- Lingala S, Lau DT, Koh C, Auh S, Ghany MG, Hoofnagle JH. Long‐term lamivudine therapy in chronic hepatitis B. Aliment. Pharmacol. Ther. 2016, 44, 380–389. DOI:10.1111/apt.13707 [Google Scholar]
- Raimond VC, Feldman WB, Rome BN, Kesselheim AS. Why France Spends Less Than the United States on Drugs: A Comparative Study of Drug Pricing and Pricing Regulation. Milbank Q. 2021, 99, 240–272. DOI:10.1111/1468-0009.12507 [Google Scholar]
- Zhang C, Zhang M, Qiu W, Ma H, Zhang X, Zhu Z, et al. Safety and efficacy of tocilizumab versus azathioprine in highly relapsing neuromyelitis optica spectrum disorder (TANGO): An open-label, multicentre, randomised, phase 2 trial. Lancet Neurol. 2020, 19, 391–401. DOI:10.1016/S1474-4422(20)30070-3 [Google Scholar]
- Ruan B, Duan JL, Xu H, Tao KS, Han H, Dou GR, et al. Capillarized Liver Sinusoidal Endothelial Cells Undergo Partial Endothelial-Mesenchymal Transition to Actively Deposit Sinusoidal ECM in Liver Fibrosis. Front. Cell Dev. Biol. 2021, 9, 671081. DOI:10.3389/fcell.2021.671081 [Google Scholar]
- McDaniel K, Meng F, Wu N, Sato K, Venter J, Bernuzzi F, et al. Forkhead box A2 regulates biliary heterogeneity and senescence during cholestatic liver injury in mice‡. Hepatology 2017, 65, 544–559. DOI:10.1002/hep.28831 [Google Scholar]
- Bansal MB, Chamroonkul N. Antifibrotics in liver disease: Are we getting closer to clinical use? Hepatol. Int. 2019, 13, 25–39. DOI:10.1007/s12072-018-9897-3 [Google Scholar]
- Li W, Zhou C, Fu Y, Chen T, Liu X, Zhang Z, et al. Targeted delivery of hyaluronic acid nanomicelles to hepatic stellate cells in hepatic fibrosis rats. Acta Pharm. Sin. B 2020, 10, 693–710. DOI:10.1016/j.apsb.2019.07.003 [Google Scholar]
- Li Z, Zhou Y, Zhang L, Jia K, Wang S, Wang M, et al. microRNA-199a-3p inhibits hepatic apoptosis and hepatocarcinogenesis by targeting PDCD4. Oncogenesis 2020, 9, 95. DOI:10.1038/s41389-020-00282-y [Google Scholar]
- Hsiao HB, Chou AH, Lin SI, Chen IH, Lien SP, Liu CC, et al. Toll-Like Receptor 9-Mediated Protection of Enterovirus 71 Infection in Mice Is Due to the Release of Danger-Associated Molecular Patterns. J. Virol. 2014, 88, 11658–11670. DOI:10.1128/JVI.00867-14 [Google Scholar]
- Mohammed S, Thadathil N, Selvarani R, Nicklas EH, Wang D, Miller BF, et al. Necroptosis contributes to chronic inflammation and fibrosis in aging liver. Aging Cell 2021, 20, e13512. DOI:10.1111/acel.13512 [Google Scholar]
- Wu Y, Wu M, Ming S, Zhan X, Hu S, Li X, et al. TREM-2 promotes Th1 responses by interacting with the CD3ζ-ZAP70 complex following Mycobacterium tuberculosis infection. J. Clin. Investig. 2021, 131, e137407. DOI:10.1172/JCI137407 [Google Scholar]
- Ji P, Zhou Y, Yang Y, Wu J, Zhou H, Quan W, et al. Myeloid cell-derived LL-37 promotes lung cancer growth by activating Wnt/β-catenin signaling. Theranostics 2019, 9, 2209–2223. DOI:10.7150/thno.30726 [Google Scholar]
- Mchedlidze T, Waldner M, Zopf S, Walker J, Rankin AL, Schuchmann M, et al. Interleukin-33-Dependent Innate Lymphoid Cells Mediate Hepatic Fibrosis. Immunity 2013, 39, 357–371. DOI:10.1016/j.immuni.2013.07.018 [Google Scholar]
- Li B, Dorrell C, Canaday PS, Pelz C, Haft A, Finegold M, et al. Adult Mouse Liver Contains Two Distinct Populations of Cholangiocytes. Stem Cell Rep. 2017, 9, 478–489. DOI:10.1016/j.stemcr.2017.06.003 [Google Scholar]
- Gordon S, Taylor PR. Monocyte and macrophage heterogeneity. Nat. Rev. Immunol. 2005, 5, 953–964. DOI:10.1038/nri1733 [Google Scholar]
- Dai E, Han L, Liu J, Xie Y, Kroemer G, Klionsky DJ, et al. Autophagy-dependent ferroptosis drives tumor-associated macrophage polarization via release and uptake of oncogenic KRAS protein. Autophagy 2020, 16, 2069–2083. DOI:10.1080/15548627.2020.1714209 [Google Scholar]
- García-Ruiz I, Blanes Ruiz N, Rada P, Pardo V, Ruiz L, Blas-García A, et al. Protein tyrosine phosphatase 1b deficiency protects against hepatic fibrosis by modulating nadph oxidases. Redox Biol. 2019, 26, 101263. DOI:10.1016/j.redox.2019.101263 [Google Scholar]
- Yotsumoto K, Sanui T, Tanaka U, Yamato H, Alshargabi R, Shinjo T, et al. Amelogenin Downregulates Interferon Gamma-Induced Major Histocompatibility Complex Class II Expression Through Suppression of Euchromatin Formation in the Class II Transactivator Promoter IV Region in Macrophages. Front. Immunol. 2020, 11, 709. DOI:10.3389/fimmu.2020.00709 [Google Scholar]
- Benner B, Scarberry L, Suarez-Kelly LP, Duggan MC, Campbell AR, Smith E, et al. Generation of monocyte-derived tumor-associated macrophages using tumor-conditioned media provides a novel method to study tumor-associated macrophages in vitro. J. Immunother. Cancer 2019, 7, 140. DOI:10.1186/s40425-019-0622-0 [Google Scholar]
- Capuano C, Battella S, Pighi C, Franchitti L, Turriziani O, Morrone S, et al. Tumor-Targeting Anti-CD20 Antibodies Mediate In Vitro Expansion of Memory Natural Killer Cells: Impact of CD16 Affinity Ligation Conditions and In Vivo Priming. Front. Immunol. 2018, 9, 1031. DOI:10.3389/fimmu.2018.01031 [Google Scholar]
- Kerstetter-Fogle A, Shukla S, Wang C, Beiss V, Harris PLR, Sloan AE, et al. Plant Virus-Like Particle In Situ Vaccine for Intracranial Glioma Immunotherapy. Cancers 2019, 11, 515. DOI:10.3390/cancers11040515 [Google Scholar]
- Lacatusu I, Iordache TA, Mihaila M, Mihaiescu DE, Pop AL, Badea N. Multifaced Role of Dual Herbal Principles Loaded-Lipid Nanocarriers in Providing High Therapeutic Efficacity. Pharmaceutics 2021, 13, 1511. DOI:10.3390/pharmaceutics13091511 [Google Scholar]
- Lee WW, Kang SW, Choi J, Lee SH, Shah K, Eynon EE, et al. Regulating human Th17 cells via differential expression of IL-1 receptor. Blood 2010, 115, 530–540. DOI:10.1182/blood-2009-08-236521 [Google Scholar]
- Tan Z, Qian X, Jiang R, Liu Q, Wang Y, Chen C, et al. IL-17A Plays a Critical Role in the Pathogenesis of Liver Fibrosis through Hepatic Stellate Cell Activation. J. Immunol. 2013, 191, 1835–1844. DOI:10.4049/jimmunol.1203013 [Google Scholar]
- Meng F, Wang K, Aoyama T, Grivennikov SI, Paik Y, Scholten D, et al. Interleukin-17 Signaling in Inflammatory, Kupffer Cells, and Hepatic Stellate Cells Exacerbates Liver Fibrosis in Mice. Gastroenterology 2012, 143, 765–776.e3. DOI:10.1053/j.gastro.2012.05.049 [Google Scholar]
- Prieto J. Inflammation, HCC and sex: IL-6 in the centre of the triangle. J. Hepatol. 2008, 48, 380–381. DOI:10.1016/j.jhep.2007.11.007 [Google Scholar]
- Lan T, Chang L, Wu L, Yuan YF. IL-6 Plays a Crucial Role in HBV Infection. J. Clin. Transl. Hepatol. 2015, 3, 271–276. DOI:10.14218/JCTH.2015.00024 [Google Scholar]
- Hu Z, Luo D, Wang D, Ma L, Zhao Y, Li L. IL-17 Activates the IL-6/STAT3 Signal Pathway in the Proliferation of Hepatitis B Virus-Related Hepatocellular Carcinoma. Cell Physiol. Biochem. 2017, 43, 2379–2390. DOI:10.1159/000484390 [Google Scholar]
- Quetier I, Brezillon N, Revaud J, Ahodantin J, DaSilva L, Soussan P, et al. C-terminal-truncated hepatitis B virus X protein enhances the development of diethylnitrosamine-induced hepatocellular carcinogenesis. J. Gen. Virol. 2015, 96, 614–625. DOI:10.1099/vir.0.070680-0 [Google Scholar]
- Jiang R, Tan Z, Deng L, Chen Y, Xia Y, Gao Y, et al. Interleukin-22 promotes human hepatocellular carcinoma by activation of STAT3. Hepatology 2011, 54, 900–909. DOI:10.1002/hep.24486 [Google Scholar]
- Dong G, Huang X, Jiang S, Ni L, Chen S. Simvastatin Mitigates Apoptosis and Transforming Growth Factor-Beta Upregulation in Stretch-Induced Endothelial Cells. Oxidative Med. Cell. Longev. 2019, 2019, 6026051. DOI:10.1155/2019/6026051 [Google Scholar]
- Shi M, Zhu J, Wang R, Chen X, Mi L, Walz T, et al. Latent TGF-β structure and activation. Nature 2011, 474, 343–349. DOI:10.1038/nature10152 [Google Scholar]
- Robertson IB, Rifkin DB. Regulation of the Bioavailability of TGF-β and TGF-β-Related Proteins. Cold Spring Harb. Perspect. Biol. 2016, 8, a021907. DOI:10.1101/cshperspect.a021907 [Google Scholar]
- Nishimura SL. Integrin-Mediated Transforming Growth Factor-β Activation, a Potential Therapeutic Target in Fibrogenic Disorders. Am. J. Pathol. 2009, 175, 1362–1370. DOI:10.2353/ajpath.2009.090393 [Google Scholar]
- Fan W, Liu T, Chen W, Hammad S, Longerich T, Hausser I, et al. ECM1 Prevents Activation of Transforming Growth Factor β, Hepatic Stellate Cells, and Fibrogenesis in Mice. Gastroenterology 2019, 157, 1352–1367.e13. DOI:10.1053/j.gastro.2019.07.036 [Google Scholar]
- Khan Z, Marshall JF. The role of integrins in TGFβ activation in the tumour stroma. Cell Tissue Res. 2016, 365, 657–673. DOI:10.1007/s00441-016-2474-y [Google Scholar]
- Fan C, Wang Q, van der Zon G, Ren J, Agaser C, Slieker RC, et al. OVOL1 inhibits breast cancer cell invasion by enhancing the degradation of TGF-β type I receptor. Signal Transduct. Target. Ther. 2022, 7, 126. DOI:10.1038/s41392-022-00944-w [Google Scholar]
- Dewidar B, Meyer C, Dooley S, Meindl-Beinker AN. TGF-β in Hepatic Stellate Cell Activation and Liver Fibrogenesis—Updated 2019. Cells 2019, 8, 1419. DOI:10.3390/cells8111419 [Google Scholar]
- Morén A, Bellomo C, Tsubakihara Y, Kardassis D, Mikulits W, Heldin CH, et al. LXRα limits TGFβ-dependent hepatocellular carcinoma associated fibroblast differentiation. Oncogenesis 2019, 8, 36. DOI:10.1038/s41389-019-0140-4 [Google Scholar]
- Zhou MY, Cheng ML, Huang T, Hu RH, Zou GL, Li H, et al. Transforming growth factor beta-1 upregulates glucose transporter 1 and glycolysis through canonical and noncanonical pathways in hepatic stellate cells. World J. Gastroenterol. 2021, 27, 6908–6926. DOI:10.3748/wjg.v27.i40.6908 [Google Scholar]
- Ma L, Zeng Y, Wei J, Yang D, Ding G, Liu J, et al. Knockdown of LOXL1 inhibits TGF-β1-induced proliferation and fibrogenesis of hepatic stellate cells by inhibition of Smad2/3 phosphorylation. Biomed. Pharmacother. 2018, 107, 1728–1735. DOI:10.1016/j.biopha.2018.08.156 [Google Scholar]
- Henderson NC, Arnold TD, Katamura Y, Giacomini MM, Rodriguez JD, McCarty JH, et al. Targeting of αv integrin identifies a core molecular pathway that regulates fibrosis in several organs. Nat. Med. 2013, 19, 1617–1624. DOI:10.1038/nm.3282 [Google Scholar]
- Park HJ, Gusarova G, Wang Z, Carr JR, Li J, Kim K, et al. Deregulation of FoxM1b leads to tumour metastasis. EMBO Mol. Med. 2011, 3, 21–34. DOI:10.1002/emmm.201000107 [Google Scholar]
- Li XM, Peng JH, Sun ZL, Tian HJ, Duan XH, Liu L, et al. Chinese medicine CGA formula ameliorates DMN-induced liver fibrosis in rats via inhibiting MMP2/9, TIMP1/2 and the TGF-β/Smad signaling pathways. Acta Pharmacol. Sin. 2016, 37, 783–793. DOI:10.1038/aps.2016.35 [Google Scholar]
- Zhang Z, Xu J, Zhang X, Wang J, Xie H, Sun Y, et al. Protective Effect of SeMet on Liver Injury Induced by Ochratoxin A in Rabbits. Toxins 2022, 14, 628. DOI:10.3390/toxins14090628 [Google Scholar]
- Xi Y, Li Y, Xu P, Li S, Liu Z, Tung HC, et al. The anti-fibrotic drug pirfenidone inhibits liver fibrosis by targeting the small oxidoreductase glutaredoxin-1. Sci. Adv. 2021, 7, eabg9241. DOI:10.1126/sciadv.abg9241 [Google Scholar]
- Yin C, Evason KJ, Asahina K, Stainier DYR. Hepatic stellate cells in liver development, regeneration, and cancer. J. Clin. Investig. 2013, 123, 1902–1910. DOI:10.1172/JCI66369 [Google Scholar]
- Khaja F, Jayawardena D, Kuzmis A, Önyüksel H. Targeted Sterically Stabilized Phospholipid siRNA Nanomedicine for Hepatic and Renal Fibrosis. Nanomaterials 2016, 6, 8. DOI:10.3390/nano6010008 [Google Scholar]
- Kamada Y, Takahashi H, Ogawa Y, Hyogo H, Nakamura K, Yada T, et al. Characterization of Nutrient Intake in Biopsy-Confirmed NAFLD Patients. Nutrients 2022, 14, 3453. DOI:10.3390/nu14173453 [Google Scholar]
- Park JS, Oh Y, Park YJ, Park O, Yang H, Slania S, et al. Targeting of dermal myofibroblasts through death receptor 5 arrests fibrosis in mouse models of scleroderma. Nat. Commun. 2019, 10, 1128. DOI:10.1038/s41467-019-09101-4 [Google Scholar]
- Sasaki R, Devhare PB, Steele R, Ray R, Ray RB. Hepatitis C virus–induced CCL5 secretion from macrophages activates hepatic stellate cells. Hepatology 2017, 66, 746–757. DOI:10.1002/hep.29170 [Google Scholar]
- Kaartinen V, Voncken JW, Shuler C, Warburton D, Bu D, Heisterkamp N, et al. Abnormal lung development and cleft palate in mice lacking TGF–β3 indicates defects of epithelial–mesenchymal interaction. Nat. Genet. 1995, 11, 415–421. DOI:10.1038/ng1295-415 [Google Scholar]
- Sanford LP, Ormsby I, Groot ACGD, Sariola H, Friedman R, Boivin GP, et al. TGFβ2 knockout mice have multiple developmental defects that are non-overlapping with other TGFβ knockout phenotypes. Development 1997, 124, 2659–2670. DOI:10.1242/dev.124.13.2659 [Google Scholar]
- Fang L, Li Y, Wang S, Li Y, Chang HM, Yi Y, et al. TGF-β1 induces VEGF expression in human granulosa-lutein cells: a potential mechanism for the pathogenesis of ovarian hyperstimulation syndrome. Exp. Mol. Med. 2020, 52, 450–460. DOI:10.1038/s12276-020-0396-y [Google Scholar]
- Ohta M, Chosa N, Kyakumoto S, Yokota S, Okubo N, Nemoto A, et al. IL‑1β and TNF‑α suppress TGF‑β‑promoted NGF expression in periodontal ligament‑derived fibroblasts through inactivation of TGF‑β‑induced Smad2/3‑ and p38 MAPK‑mediated signals. Int. J. Mol. Med. 2018, 42, 1484–1494. DOI:10.3892/ijmm.2018.3714 [Google Scholar]
- Meng XM, Nikolic-Paterson DJ, Lan HY. TGF-β: The master regulator fibrosis. Nat. Rev. Nephrol. 2016, 12, 325–338. DOI:10.1038/nrneph.2016.48 [Google Scholar]
- Kawelke N, Vasel M, Sens C, von Au A, Dooley S, Nakchbandi IA. Fibronectin Protects from Excessive Liver Fibrosis by Modulating the Availability of and Responsiveness of Stellate Cells to Active TGF-β. PLoS ONE 2011, 6, e28181. DOI:10.1371/journal.pone.0028181 [Google Scholar]
- Gurney A, Axelrod F, Bond CJ, Cain J, Chartier C, Donigan L, et al. Wnt pathway inhibition via the targeting of Frizzled receptors results in decreased growth and tumorigenicity of human tumors. Proc. Natl. Acad. Sci. USA 2012, 109, 11717–11722. DOI:10.1073/pnas.1120068109 [Google Scholar]
- Olaso E, Ikeda K, Eng FJ, Xu L, Wang LH, Lin HC, et al. DDR2 receptor promotes MMP-2–mediated proliferation and invasion by hepatic stellate cells. J. Clin. Investig. 2001, 108, 1369–1378. DOI:10.1172/JCI200112373 [Google Scholar]
- Ojiaku CA, Chung E, Parikh V, Williams JK, Schwab A, Fuentes AL, et al. Transforming Growth Factor-β1 Decreases β2-Agonist–induced Relaxation in Human Airway Smooth Muscle. Am. J. Respir. Cell Mol. Biol. 2019, 61, 209–218. DOI:10.1165/rcmb.2018-0301OC [Google Scholar]
- Altrock E, Sens C, Wuerfel C, Vasel M, Kawelke N, Dooley S, et al. Inhibition of fibronectin deposition improves experimental liver fibrosis. J. Hepatol. 2015, 62, 625–633. DOI:10.1016/j.jhep.2014.06.010 [Google Scholar]
- Kisseleva T, Brenner DA. Role of hepatic stellate cells in fibrogenesis and the reversal of fibrosis. J. Gastro Hepatol. 2007, 22, S73–S78. DOI:10.1111/j.1440-1746.2006.04658.x [Google Scholar]
- Troeger JS, Mederacke I, Gwak G, Dapito DH, Mu X, Hsu CC, et al. Deactivation of Hepatic Stellate Cells During Liver Fibrosis Resolution in Mice. Gastroenterology 2012, 143, 1073–1083.e22. DOI:10.1053/j.gastro.2012.06.036 [Google Scholar]
- Arroyo N, Villamayor L, Díaz I, Carmona R, Ramos-Rodríguez M, Muñoz-Chápuli R, et al. GATA4 induces liver fibrosis regression by deactivating hepatic stellate cells. JCI Insight 2021, 6, e150059. DOI:10.1172/jci.insight.150059 [Google Scholar]
- Pellicoro A, Ramachandran P, Iredale JP, Fallowfield JA. Liver fibrosis and repair: Immune regulation of wound healing in a solid organ. Nat. Rev. Immunol. 2014, 14, 181–194. DOI:10.1038/nri3623 [Google Scholar]
- Luedde T, Kaplowitz N, Schwabe RF. Cell Death and Cell Death Responses in Liver Disease: Mechanisms and Clinical Relevance. Gastroenterology 2014, 147, 765–783.e4. DOI:10.1053/j.gastro.2014.07.018 [Google Scholar]
- Unitt E, Rushbrook SM, Marshall A, Davies S, Gibbs P, Morris LS, et al. Compromised lymphocytes infiltrate hepatocellular carcinoma. Hepatology 2005, 41, 722–730. DOI:10.1002/hep.20644 [Google Scholar]
- Unitt E, Marshall A, Gelson W, Rushbrook SM, Davies S, Vowler SL, et al. Tumour lymphocytic infiltrate and recurrence of hepatocellular carcinoma following liver transplantation. J. Hepatol. 2006, 45, 246–253. DOI:10.1016/j.jhep.2005.12.027 [Google Scholar]
- Yuan J, Wang Y, Wang X, Zhang W, Ding R, Yue S, et al. Construction and experimental verification of user-friendly molecular subtypes mediated by immune-associated genes in hepatocellular carcinoma. Front. Oncol. 2022, 12, 924059. DOI:10.3389/fonc.2022.924059 [Google Scholar]
- Hu Y, Zeng N, Ge Y, Wang D, Qin X, Zhang W, et al. Identification of the Shared Gene Signatures and Biological Mechanism in Type 2 Diabetes and Pancreatic Cancer. Front. Endocrinol. 2022, 13, 847760. DOI:10.3389/fendo.2022.847760 [Google Scholar]
- Wang PW, Lin TY, Yang PM, Yeh CT, Pan TL. Hepatic Stellate Cell Modulates the Immune Microenvironment in the Progression of Hepatocellular Carcinoma. Int. J. Mol. Sci. 2022, 23, 10777. DOI:10.3390/ijms231810777 [Google Scholar]
- Mederacke I, Hsu CC, Troeger JS, Huebener P, Mu X, Dapito DH, et al. Fate tracing reveals hepatic stellate cells as dominant contributors to liver fibrosis independent of its aetiology. Nat. Commun. 2013, 4, 2823. DOI:10.1038/ncomms3823 [Google Scholar]
- He S, Luo Y, Ma W, Wang X, Yan C, Hao W, et al. Endothelial POFUT1 controls injury-induced liver fibrosis by repressing fibrinogen synthesis. J. Hepatol. 2024, 81, 135–148. DOI:10.1016/j.jhep.2024.02.032 [Google Scholar]
- Sarrazy V, Viaud M, Westerterp M, Ivanov S, Giorgetti-Peraldi S, Guinamard R, et al. Disruption of Glut1 in Hematopoietic Stem Cells Prevents Myelopoiesis and Enhanced Glucose Flux in Atheromatous Plaques of ApoE−/− Mice. Circ. Res. 2016, 118, 1062–1077. DOI:10.1161/CIRCRESAHA.115.307599 [Google Scholar]
- Zhao G, Dong R, Teng J, Yang L, Liu T, Wu X, et al. N-Acetyl-l-cysteine Enhances the Effect of Selenium Nanoparticles on Cancer Cytotoxicity by Increasing the Production of Selenium-Induced Reactive Oxygen Species. ACS Omega 2020, 5, 11710–11720. DOI:10.1021/acsomega.0c01034 [Google Scholar]
- Hellemans K, Grinko I, Rombouts K, Schuppan D, Geerts A. All-trans and 9-cis retinoic acid alter rat hepatic stellate cell phenotype differentially. Gut 1999, 45, 134–142. DOI:10.1136/gut.45.1.134 [Google Scholar]
- Acharya P, Chouhan K, Weiskirchen S, Weiskirchen R. Cellular Mechanisms of Liver Fibrosis. Front. Pharmacol. 2021, 12, 671640. DOI:10.3389/fphar.2021.671640 [Google Scholar]
- Han QJ, Mu YL, Zhao HJ, Zhao RR, Guo QJ, Su YH, et al. Fasudil prevents liver fibrosis via activating natural killer cells and suppressing hepatic stellate cells. World J. Gastroenterol. 2021, 27, 3581–3594. DOI:10.3748/wjg.v27.i24.3581 [Google Scholar]
- Casson CN, Doerner JL, Copenhaver AM, Ramirez J, Holmgren AM, Boyer MA, et al. Neutrophils and Ly6Chi monocytes collaborate in generating an optimal cytokine response that protects against pulmonary Legionella pneumophila infection. PLoS Pathog. 2017, 13, e1006309. DOI:10.1371/journal.ppat.1006309 [Google Scholar]
- Knolle PA, Thimme R. Hepatic Immune Regulation and Its Involvement in Viral Hepatitis Infection. Gastroenterology 2014, 146, 1193–1207. DOI:10.1053/j.gastro.2013.12.036 [Google Scholar]
- Winau F, Hegasy G, Weiskirchen R, Weber S, Cassan C, Sieling PA, et al. Ito Cells Are Liver-Resident Antigen-Presenting Cells for Activating T Cell Responses. Immunity 2007, 26, 117–129. DOI:10.1016/j.immuni.2006.11.011 [Google Scholar]
- Goh CC, Roggerson KM, Lee HC, Golden-Mason L, Rosen HR, Hahn YS. Hepatitis C Virus–Induced Myeloid-Derived Suppressor Cells Suppress NK Cell IFN-γ Production by Altering Cellular Metabolism via Arginase-1. J. Immunol. 2016, 196, 2283–2292. DOI:10.4049/jimmunol.1501881 [Google Scholar]
- Hoechst B, Ormandy LA, Ballmaier M, Lehner F, Krüger C, Manns MP, et al. A New Population of Myeloid-Derived Suppressor Cells in Hepatocellular Carcinoma Patients Induces CD4+CD25+Foxp3+ T Cells. Gastroenterology 2008, 135, 234–243. DOI:10.1053/j.gastro.2008.03.020 [Google Scholar]
- Hoechst B, Voigtlaender T, Ormandy L, Gamrekelashvili J, Zhao F, Wedemeyer H, et al. Myeloid derived suppressor cells inhibit natural killer cells in patients with hepatocellular carcinoma via the NKp30 receptor #. Hepatology 2009, 50, 799–807. DOI:10.1002/hep.23054 [Google Scholar]
- Wang YH, Hou HA, Lin CC, Kuo YY, Yao CY, Hsu CL, et al. A CIBERSORTx-based immune cell scoring system could independently predict the prognosis of patients with myelodysplastic syndromes. Blood Adv. 2021, 5, 4535–4548. DOI:10.1182/bloodadvances.2021005141 [Google Scholar]
- Hafez MM, Hamed SS, El-Khadragy MF, Hassan ZK, Al Rejaie SS, Sayed-Ahmed MM, et al. Effect of ginseng extract on the TGF-β1 signaling pathway in CCl4-induced liver fibrosis in rats. BMC Complement. Altern. Med. 2017, 17, 45. DOI:10.1186/s12906-016-1507-0 [Google Scholar]
- Höchst B, Schildberg FA, Sauerborn P, Gäbel YA, Gevensleben H, Goltz D, et al. Activated human hepatic stellate cells induce myeloid derived suppressor cells from peripheral blood monocytes in a CD44-dependent fashion. J. Hepatol. 2013, 59, 528–535. DOI:10.1016/j.jhep.2013.04.033 [Google Scholar]
- Tarantino G, Citro V. Liver-spleen axis: Deciphering a crucial crosstalk in non-alcoholic fatty liver disease progression and therapeutic implications. World J. Gastroenterol. 2026, 32, 119467. DOI:10.3748/wjg.119467 [Google Scholar]
- Laparra Llopis JM, Brown D, Saiz B. Chenopodium Quinoa and Salvia Hispanica Provide Immunonutritional Agonists to Ameliorate Hepatocarcinoma Severity under a High-Fat Diet. Nutrients 2020, 12, 1946. DOI:10.3390/nu12071946 [Google Scholar]
- Ma C, Kesarwala AH, Eggert T, Medina-Echeverz J, Kleiner DE, Jin P, et al. NAFLD causes selective CD4+ T lymphocyte loss and promotes hepatocarcinogenesis. Nature 2016, 531, 253–257. DOI:10.1038/nature16969 [Google Scholar]
- Satriano L, Lewinska M, Rodrigues PM, Banales JM, Andersen JB. Metabolic rearrangements in primary liver cancers: Cause and consequences. Nat. Rev. Gastroenterol. Hepatol. 2019, 16, 748–766. DOI:10.1038/s41575-019-0217-8 [Google Scholar]
- Atarashi M, Izawa T, Mori M, Inai Y, Kuwamura M, Yamate J. Dietary Iron Overload Abrogates Chemically-Induced Liver Cirrhosis in Rats. Nutrients 2018, 10, 1400. DOI:10.3390/nu10101400 [Google Scholar]
- Bu P, Chen KY, Xiang K, Johnson C, Crown SB, Rakhilin N, et al. Aldolase B-Mediated Fructose Metabolism Drives Metabolic Reprogramming of Colon Cancer Liver Metastasis. Cell Metab. 2018, 27, 1249–1262.e4. DOI:10.1016/j.cmet.2018.04.003 [Google Scholar]
- Bolatai A, He Y, Wu N. Vascular endothelial growth factor and its receptors regulation in gestational diabetes mellitus and eclampsia. J. Transl. Med. 2022, 20, 400. DOI:10.1186/s12967-022-03603-4 [Google Scholar]
- Kessler T, Sahm F, Blaes J, Osswald M, Rübmann P, Milford D, et al. Glioma cell VEGFR-2 confers resistance to chemotherapeutic and antiangiogenic treatments in PTEN-deficient glioblastoma. Oncotarget 2015, 6, 31050–31068. DOI:10.18632/oncotarget.2910 [Google Scholar]
- Faes S, Santoro T, Demartines N, Dormond O. Evolving Significance and Future Relevance of Anti-Angiogenic Activity of mTOR Inhibitors in Cancer Therapy. Cancers 2017, 9, 152. DOI:10.3390/cancers9110152 [Google Scholar]
- Mercurio AM, Lipscomb EA, Bachelder RE. Non-Angiogenic Functions of VEGF in Breast Cancer. J. Mammary Gland. Biol. Neoplasia 2005, 10, 283–290. DOI:10.1007/s10911-006-9001-9 [Google Scholar]
- Feng R, Morine Y, Ikemoto T, Imura S, Iwahashi S, Saito Y, et al. Nrf2 activation drive macrophages polarization and cancer cell epithelial-mesenchymal transition during interaction. Cell Commun. Signal 2018, 16, 54. DOI:10.1186/s12964-018-0262-x [Google Scholar]
- Okikawa S, Morine Y, Saito Y, Yamada S, Tokuda K, Teraoku H, et al. Inhibition of the VEGF signaling pathway attenuates tumor‑associated macrophage activity in liver cancer. Oncol. Rep. 2022, 47, 71. DOI:10.3892/or.2022.8282 [Google Scholar]
- Cheng AL, Kang YK, Lin DY, Park JW, Kudo M, Qin S, et al. Sunitinib Versus Sorafenib in Advanced Hepatocellular Cancer: Results of a Randomized Phase III Trial. J. Clin. Oncol. 2013, 31, 4067–4075. DOI:10.1200/JCO.2012.45.8372 [Google Scholar]
- Llovet JM, Montal R, Villanueva A. Randomized trials and endpoints in advanced HCC: Role of PFS as a surrogate of survival. J. Hepatol. 2019, 70, 1262–1277. DOI:10.1016/j.jhep.2019.01.028 [Google Scholar]
- Behrens J, Jerchow BA, Würtele M, Grimm J, Asbrand C, Wirtz R, et al. Functional Interaction of an Axin Homolog, Conductin, with β-Catenin, APC, and GSK3β. Science 1998, 280, 596–599. DOI:10.1126/science.280.5363.596 [Google Scholar]
- Kimelman D, Xu W. β-Catenin destruction complex: Insights and questions from a structural perspective. Oncogene 2006, 25, 7482–7491. DOI:10.1038/sj.onc.1210055 [Google Scholar]
- Liu C, Li Y, Semenov M, Han C, Baeg GH, Tan Y, et al. Control of β-Catenin Phosphorylation/Degradation by a Dual-Kinase Mechanism. Cell 2002, 108, 837–847. DOI:10.1016/S0092-8674(02)00685-2 [Google Scholar]
- Amit S, Hatzubai A, Birman Y, Andersen JS, Ben-Shushan E, Mann M, et al. Axin-mediated CKI phosphorylation of β-catenin at Ser 45: A molecular switch for the Wnt pathway. Genes Dev. 2002, 16, 1066–1076. DOI:10.1101/gad.230302 [Google Scholar]
- Nejak-Bowen KN, Thompson MD, Singh S, Bowen WC, Dar MJ, Khillan J, et al. Accelerated Liver Regeneration and Hepatocarcinogenesis in Mice Overexpressing Serine-45 Mutant β-Catenin. Hepatology 2010, 51, 1603–1613. DOI:10.1002/hep.23538 [Google Scholar]
- Zhang XF, Tan X, Zeng G, Misse A, Singh S, Kim Y, et al. Conditional β-Catenin Loss in Mice Promotes Chemical Hepatocarcinogenesis: Role of Oxidative Stress and Platelet-Derived Growth Factor Receptor α/Phosphoinositide 3-Kinase Signaling. Hepatology 2010, 52, 954–965. DOI:10.1002/hep.23747 [Google Scholar]
- Delgado E, Okabe H, Preziosi M, Russell JO, Alvarado TF, Oertel M, et al. Complete response of Ctnnb1-mutated tumours to β-catenin suppression by locked nucleic acid antisense in a mouse hepatocarcinogenesis model. J. Hepatol. 2015, 62, 380–387. DOI:10.1016/j.jhep.2014.10.021 [Google Scholar]
- Chaudhary B, Elkord E. Regulatory T Cells in the Tumor Microenvironment and Cancer Progression: Role and Therapeutic Targeting. Vaccines 2016, 4, 28. DOI:10.3390/vaccines4030028 [Google Scholar]
- Sharma P, Hu-Lieskovan S, Wargo JA, Ribas A. Primary, Adaptive, and Acquired Resistance to Cancer Immunotherapy. Cell 2017, 168, 707–723. DOI:10.1016/j.cell.2017.01.017 [Google Scholar]
- Van Loosdregt J, Fleskens V, Tiemessen MM, Mokry M, van Boxtel R, Meerding J, et al. Canonical Wnt Signaling Negatively Modulates Regulatory T Cell Function. Immunity 2013, 39, 298–310. DOI:10.1016/j.immuni.2013.07.019 [Google Scholar]
- Dai W, Liu F, Li C, Lu Y, Lu X, Du S, et al. Blockade of Wnt/β-Catenin Pathway Aggravated Silica-Induced Lung Inflammation through Tregs Regulation on Th Immune Responses. Mediat. Inflamm. 2016, 2016, 6235614. DOI:10.1155/2016/6235614 [Google Scholar]
- Di Piazza M, Nowell CS, Koch U, Durham AD, Radtke F. Loss of Cutaneous TSLP-Dependent Immune Responses Skews the Balance of Inflammation from Tumor Protective to Tumor Promoting. Cancer Cell 2012, 22, 479–493. DOI:10.1016/j.ccr.2012.08.016 [Google Scholar]
- You L, Zhang C, Yarravarapu N, Morlock L, Wang X, Zhang L, et al. Development of a triazole class of highly potent Porcn inhibitors. Bioorganic Med. Chem. Lett. 2016, 26, 5891–5895. DOI:10.1016/j.bmcl.2016.11.012 [Google Scholar]
- Liu Y, Xun Z, Ma K, Liang S, Li X, Zhou S, et al. Identification of a tumour immune barrier in the HCC microenvironment that determines the efficacy of immunotherapy. J. Hepatol. 2023, 78, 770–782. DOI:10.1016/j.jhep.2023.01.011 [Google Scholar]