
Recent Applications of mRNA-Based Technology for Disease Therapy
Recent Applications of mRNA-Based Technology for Disease Therapy
Jun Zhao
1,2,†
 Xiang Wen
1,2,†
Yang Su
1,2,†
Qiang Huang
2,3
Wei Jiang
2
Haoyang Wang
2,4
Jia Zhang
2
Yuting Li
2,*
Xiangsheng Liu
1,2,*
Received: 28 May 2026 Revised: 18 August 2026 Accepted: 01 September 2026 Published: 15 September 2026

© 2026 The authors. This is an open access article under the Creative Commons Attribution 4.0 International License (https://creativecommons.org/licenses/by/4.0/).
1. Introduction
In recent years, messenger RNA (mRNA) drugs have been recognized as an emerging therapeutic approach for the prevention and treatment of various diseases [1]. During the COVID-19 pandemic, two highly effective mRNA vaccines, Spikevax (mRNA-1273) from Moderna and Comirnaty (BNT162b2) from Pfizer-BioNTech, have achieved remarkable therapeutic efficacy [2]. Moreover, a recent study showed that the COVID-19 vaccine could also sensitize tumors to immune checkpoint blockade [3]. The remarkable success of these vaccines has catalyzed the rapid expansion of mRNA therapeutics into other disease areas [4]. mRNA can produce almost any functional protein or polypeptide, and thus can be applied to the treatment of any protein-related disease, including cancer immunotherapy, protein replacement therapy, gene editing, and in vivo chimeric antigen receptor (CAR) therapy [5].
Since the discovery of mRNA in the 1960s, it has taken just over 60 years for mRNA-based drugs to evolve into a diverse array of therapeutic modalities (Figure 1) [6]. In 1978, it was first found that mRNA could be delivered into mouse or human cells to express encoded proteins when packaged into lipid carriers [7]. In 1990, Wolff et al. first reported that intramuscular injection of naked mRNA or plasmid DNA could produce functional proteins in vivo [8]. Since then, research on mRNA therapy has become increasingly diversified, and its clinical applications are growing ever more widespread [9]. mRNA therapy offers great advantages and is suitable for various treatment scenarios. mRNA serves as the template for protein synthesis and acts as the intermediary that transfers genetic information from DNA to proteins [10]. Eukaryotic mRNA consists of five parts, including the 5′ cap, 5′ untranslated region (UTR), open reading frame (ORF), 3′ UTR, and poly(A) tail [11] Compared with DNA-based approaches, mRNA expresses the encoded protein only transiently, which avoids the risk of insertion mutations and does not require entry into the nucleus [12]. mRNA can be synthesized via in vitro transcription, which features lower production costs, shorter preparation cycles, and rapid scalability for diverse therapeutic applications [13]. In theory, mRNA can express any functional protein or polypeptide, making it applicable to nearly any disease area [14]. Despite these advantages, several challenges remain in the development of mRNA therapeutics. For example, mRNA drugs require suitable delivery vehicles to reduce immunogenicity and overcome multiple biological barriers, including tissue-specific obstacles and endosomal entrapment. Lipid nanoparticles (LNPs), cationic polymers, and other delivery systems have made significant contributions to the targeted delivery of mRNA to specific tissues and cells [15].
Figure 1. History of mRNA technology. mRNA, messenger RNA; DCs, dendritic cells; CRISPR/Cas9, clustered regularly interspaced short palindromic repeats/CRISPR-associated protein 9; COVID-19, coronavirus disease 2019; FDA, United States Food and Drug Administration; RSV, respiratory syncytial virus; EMA, European Medicines Agency.
By delivering mRNA encoding infectious disease antigens, cancer antigens, gene editing components, or disease-related therapeutic proteins, mRNA technology enables clinical applications in vaccines, gene editing, protein replacement therapy, and chimeric antigen receptor therapy (Figure 2). This review categorizes mRNA therapeutics by clinical application, summarizes strategies for using mRNA across different diseases and the modification methods tailored to each therapeutic context, and finally presents future perspectives on the development of mRNA-based therapies.
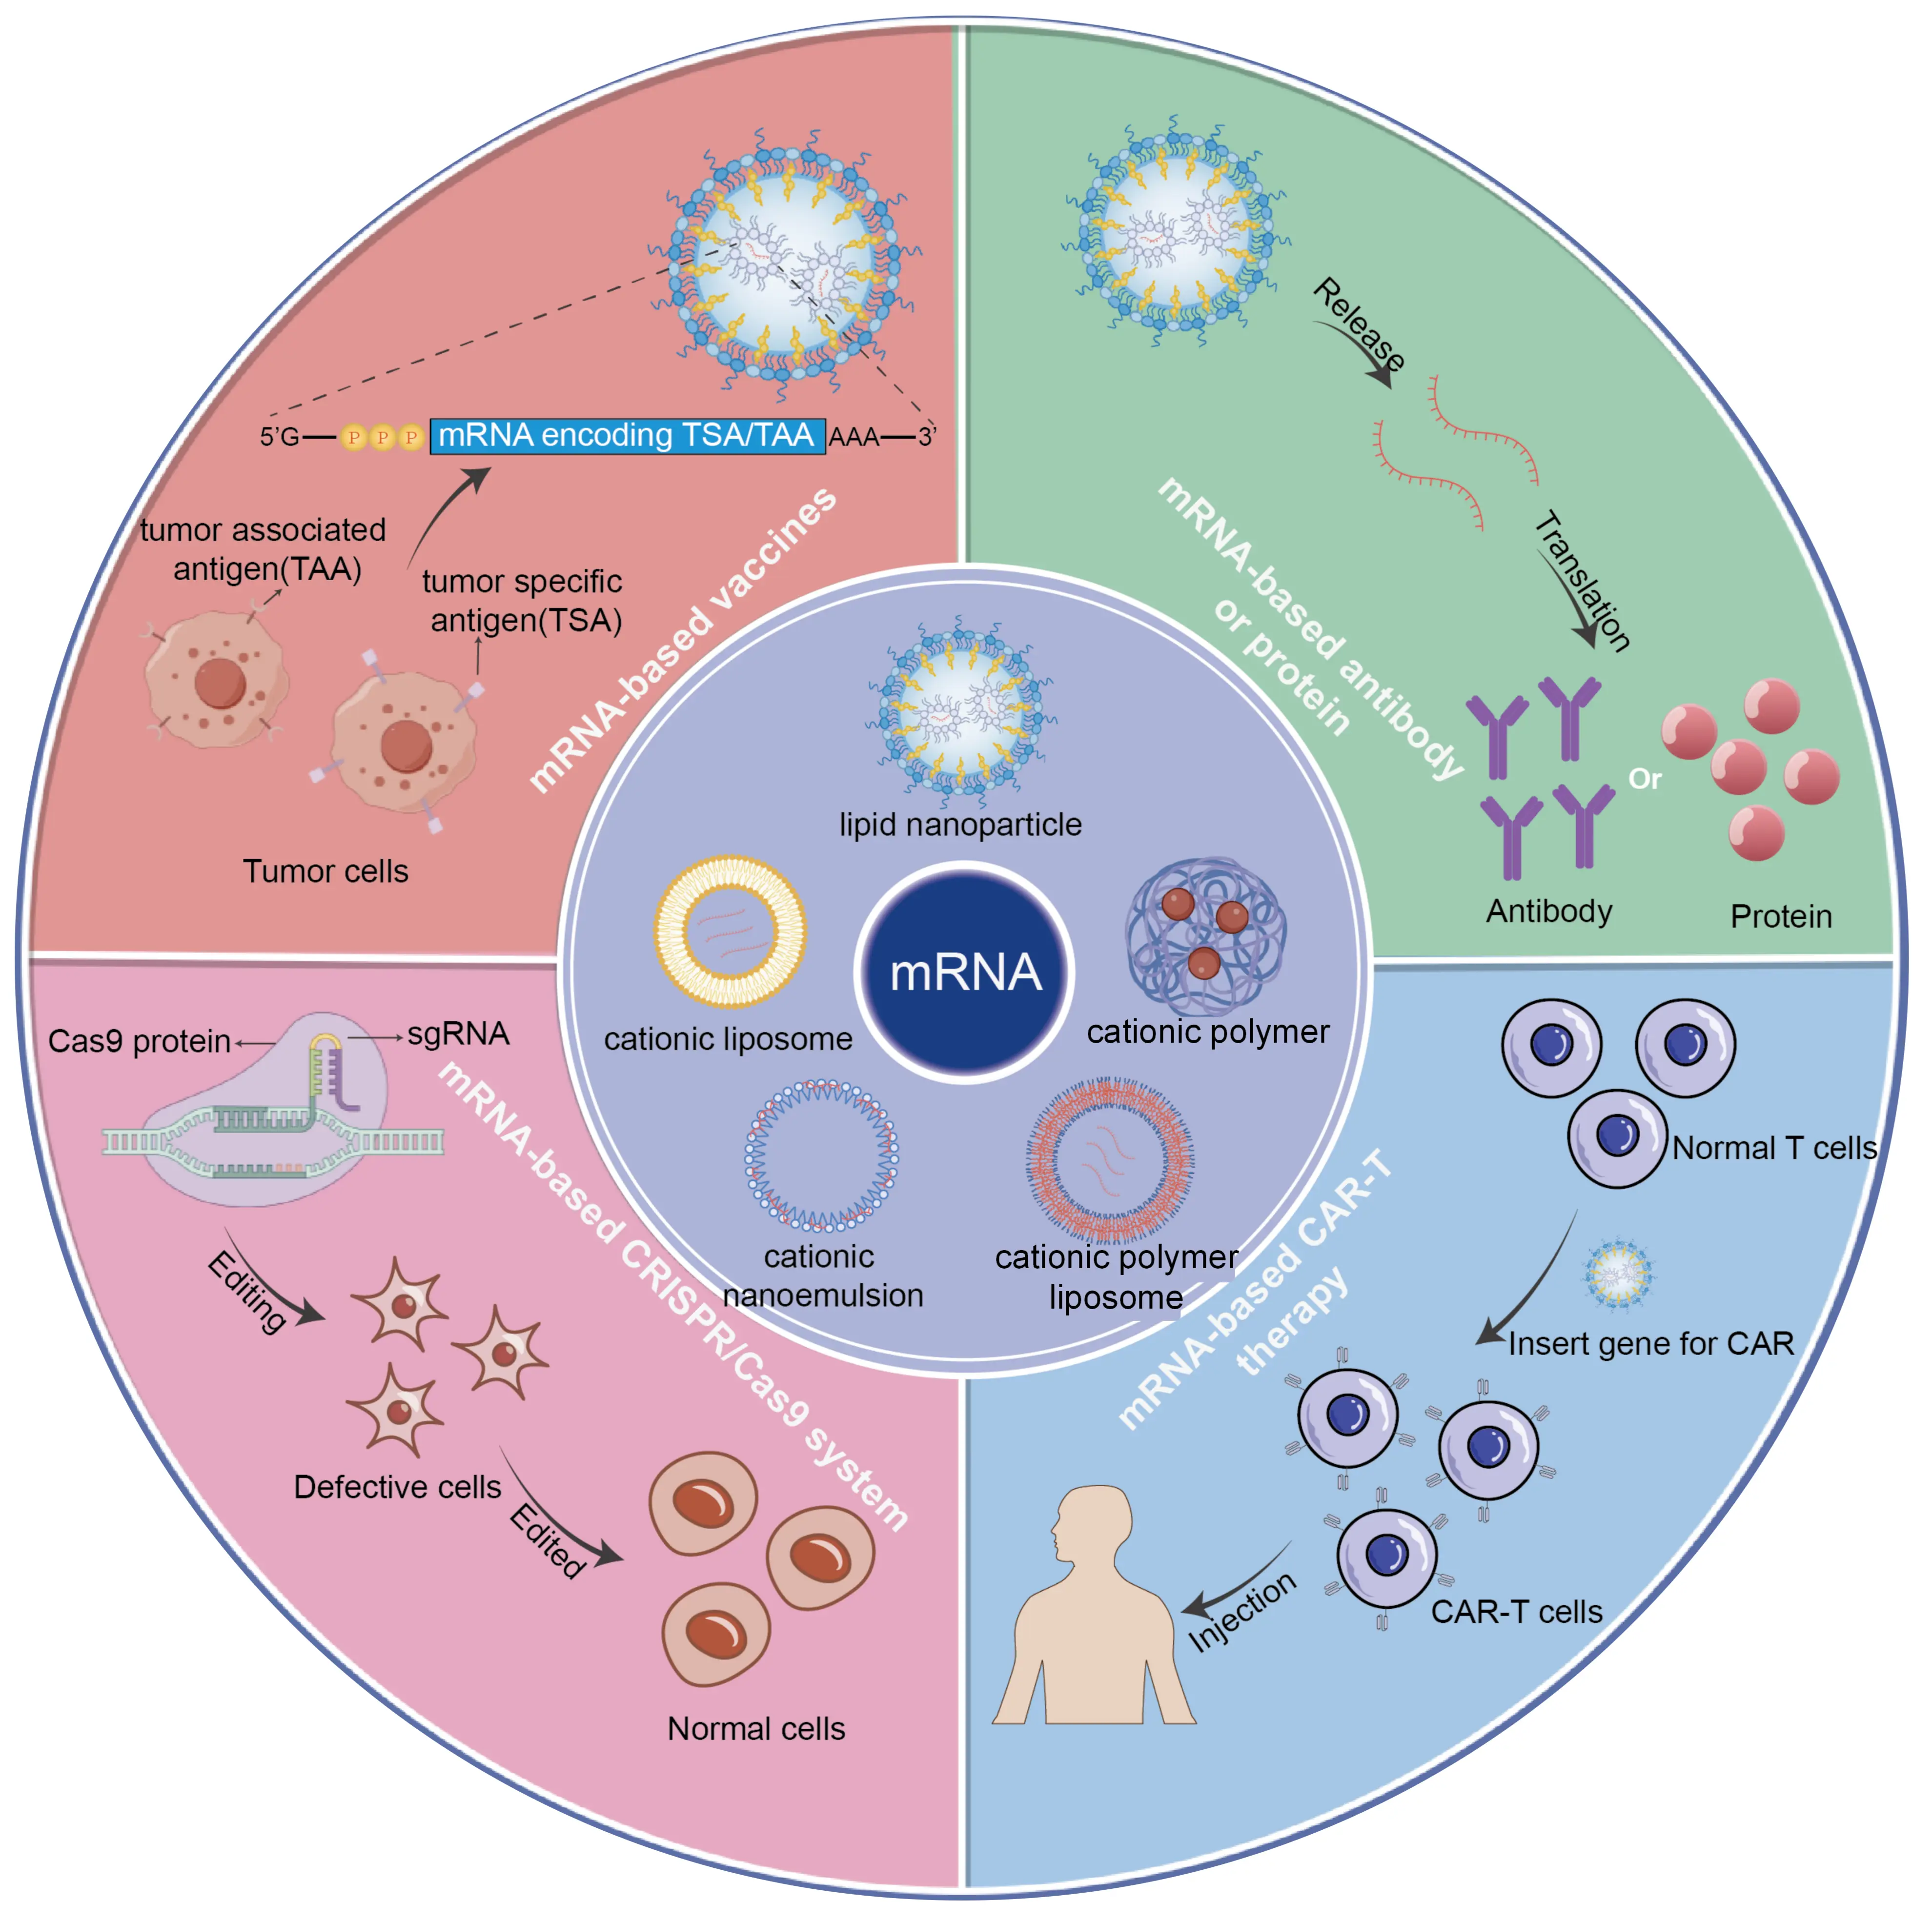
Figure 2. Overview of different delivery systems and applications of mRNA drugs. For mRNA delivery, various systems have been developed, including lipid nanoparticles, cationic liposomes, cationic polymers, and cationic nanoemulsions. For therapeutic applications, mRNA drugs are used in cancer vaccines, protein replacement therapy, gene editing, and chimeric antigen receptor therapy.
2. mRNA Vaccines
The development of COVID-19 vaccines in recent years has demonstrated the potential of mRNA vaccine technology. Compared with traditional vaccines, mRNA vaccines offer advantages including high potency, low manufacturing cost, and rapid development [16]. A key advantage of mRNA for vaccine development lies in its immune-activating ability and its capacity to serve as an immune adjuvant (Figure 3). However, to achieve a safe and effective product for clinical use, a balance must be struck between immune activation and safety [17].
Modification of specific sites on nucleobases can significantly enhance the stability and reduce immunogenicity. Unmodified mRNA entering the organism is recognized by pattern recognition receptors, resulting in immune stimulation [18]. Katalin Karikó and other scientists have found that the incorporation of modified nucleosides into mRNA can greatly improve translation efficiency [19,20]. Typical nucleoside analogs generated by base modification include 5-methylcytidine (m5C), 5-fluorouracil (5-FU), N7-methylguanosine (m7G), pseudouridine (Ψ), N6-methyladenosine (m6A), and 2′-deoxy-2′-fluorouridine (2′-FU). Modifications with m5C and Ψ can reduce the activity of cytokines and other biomarkers in dendritic cells, thereby helping mRNA evade immune detection and thus improving safety [21].

Figure 3. The mechanism of mRNA vaccines. mRNA encoding viral or tumor antigens is delivered by nanocarriers via endocytosis. Host ribosomes translate the mRNA into antigenic proteins, which are processed and presented on MHC class I and II molecules to activate CD8+ cytotoxic T cells and CD4+ helper T cells, respectively. B cells produce neutralizing antibodies, mediating humoral immunity.
2.1. Cancer Vaccine
Dendritic cells (DCs) are the most commonly used target cells for cancer vaccines, as they play a critical role in inducing specific antitumor immune responses. Adoptive transfer of mRNA-transfected DCs was the first mRNA therapeutic tumor vaccine to enter clinical trials [22]. These DCs are primarily derived from patients and can be transfected ex vivo to generate personalized tumor vaccines [23]. Recently, new platforms based on non-viral vectors have begun to be used in cancer vaccines, as summarized in Table 1. These vectors can directly deliver antigen-encoding mRNA to achieve in situ therapy.
Table 1. The clinical trials of mRNA cancer vaccines.
|
NCT Number |
Phase |
Cancer Type |
mRNA |
Combination |
Route |
Sponsor |
|---|---|---|---|---|---|---|
|
NCT05202561 |
I |
Advanced Solid Tumor |
RNA tumor vaccine |
With Nivolumab |
Intravenous |
First Affiliated Hospital, Bengbu Medical College |
|
NCT04573140 |
I |
Glioblastoma |
Formulation with pp65 LAMP and tumor mRNA |
None |
Intravenous |
University of Florida |
|
NCT03418480 |
I/II |
HPV16-positive solid tumors |
BNT113 (HPV16 E6 and E7 oncoproteins) |
With anti-CD40 antibodies |
Intravenous |
University of Southampton |
|
NCT04161755 |
I |
Pancreatic |
BNT122 (personalized cancer vaccine encoding individual tumor mutations) |
With oxaliplatin, irinotecan, fluorouracil, leucovorin, and atezolizumab |
Intravenous |
Memorial Sloan Kettering Cancer Center |
|
NCT03313778 |
I |
Solid tumors (resected) |
mRNA-4157 (personalized cancer vaccine encoding several neoantigens) |
With pembrolizumab |
Intramuscular |
Moderna |
|
NCT03897881 |
II |
Melanoma |
mRNA-4157 (personalized cancer vaccine encoding 20 different mutated neoepitopes) |
With pembrolizumab |
Intramuscular |
Moderna |
|
NCT03815058 |
II |
Advanced melanoma |
BNT122 (personalized cancer vaccine encoding individual tumor mutations) |
With pembrolizumab |
Intravenous |
Genentech |
|
NCT03289962 |
I |
Solid tumors |
BNT122 (personalized cancer vaccine encoding individual tumor mutations) |
With atezolizumab |
Intravenous |
Genentech |
|
NCT04526899 |
II |
Melanoma |
BNT111 (NY-ESO-1, tyrosinase, MAGE-A3, and TPTE) |
With cemiplimab |
Intravenous |
BioNTech |
|
NCT04382898 |
I/II |
Prostate |
BNT112 (PAP, PSA, and three undisclosed antigens) |
With cemiplimab |
Intravenous |
BioNTech |
|
NCT04534205 |
II |
Head and neck squamous cell carcinoma |
BNT113 (HPV16 E6 and E7 oncoproteins) |
With pembrolizumab |
Intravenous |
BioNTech |
|
NCT05142189 |
I |
Non-small-cell lung cancer |
BNT116 (non-small-cell lung cancer tumor-associated antigens) |
With cemiplimab plus docetaxel |
Intravenous |
BioNTech |
|
NCT04486378 |
II |
Colorectal |
BNT122 (personalized cancer vaccine encoding individual tumor mutations) |
None |
Intravenous |
BioNTech |
|
NCT04503278 |
I/II |
Solid tumors |
CARVac (CLDN6) |
With chimeric antigen receptor therapy |
Intravenous |
BioNTech and Gene Therapies |
In general, tumor antigens include two broad categories: tumor-associated antigens (TAAs) and tumor-specific antigens (TSAs). TAAs are typically overexpressed in tumor cells but can also be present in normal tissues, resulting in weak tumor specificity and immunogenicity. TSAs are neoantigens derived from tumor cell mutations. They exhibit high tumor specificity and immunogenicity and are less subject to immune tolerance [24]. Upon administration, mRNA vaccines introduce tumor antigens and initiate the antigen presentation cascade via the major histocompatibility complex (MHC). Antigen-presenting cells (APCs) present tumor antigens through MHC class I and class II molecules, thereby activating CD8+ and CD4+ T cells [25]. mRNA vaccines have been used to treat aggressive, hard-to-treat, and metastatic solid tumors, including non-small cell lung cancer, colorectal cancer, and melanoma. Additionally, early proof-of-concept studies have explored the application of mRNA vaccines in glioblastoma treatment [26].
2.1.1. mRNA Encoding TAAs
The selection of appropriate TAAs is a fundamental determinant of cancer vaccine efficacy. However, the human body tends to exhibit considerable immune tolerance toward a single TAA. Therefore, the use of multiple TAA combinations to improve vaccine efficacy has become increasingly popular. Mixtures encoding multiple TAAs have been extensively explored in preclinical and clinical studies across various tumor types [27]. For example, a Phase I/II trial (NCT01734304) targeting acute myeloid leukemia (AML) used an mRNA vaccine encoding tumor-associated antigens, including WT1, PRAME, and CMV pp65. The vaccine was delivered via electroporation into Toll-like receptor (TLR) 7- and TLR8-matured DCs. This study demonstrated that the vaccine was well tolerated and provided a treatment option for patients at high risk of recurrence, with a favorable safety profile [28]. Moreover, total tumor RNA (ttRNA) is a set of RNA molecules derived from tumor tissues and tumor stem cells that encode a series of tumor-related proteins. ttRNA can be directly used to design tumor vaccines that induce polyclonal anti-tumor immune responses against diverse antigenic epitopes. Clinical trials have demonstrated the potential efficacy of this approach (NCT04837547) [29].
The isolation of DCs from a patient’s blood, followed by in vitro culture, differentiation, and tumor antigen loading, results in a production process that is costly and complex. Consequently, recent research has focused on exploring non-viral vectors as alternative delivery systems for tumor vaccines. Kranz et al. developed a platform called RNA-liposome (RNA-LPX), which enabled the concurrent delivery of four antigens (MAGE-A3, NY-ESO-1, tyrosinase, and TPTE). This platform not only induces dendritic cell maturation but also elicits robust anti-tumor cellular immunity in melanoma patients. BioNTech’s Lipo-MERIT vaccine, which comprises mRNA and cationic lipids such as 1,2-di-octadecenyl-3-trimethylpropane ammonium (DOTMA), 1,2-dioleoyl-3-trimethylpropane ammonium (DOTAP), and 1,2-dioleoyl-SN-glycerol-3-phosphate ethanolamine (DOPE), represents another advancement. Notably, this vaccine exhibits charge-tunable properties. Negatively charged nanoparticles target DCs in the spleen and stimulate T cell responses, whereas cationic nanoparticles primarily target the lung [30].
In a completed Phase I clinical trial (NCT02410733), a total of 115 melanoma patients were treated with the Lipo-MERIT vaccine (BNT111) encoding melanoma-associated TAAs (NY-ESO-1, MAGE-A3, TPTE, and tyrosinase), administered alone or in combination with a PD-1 inhibitor. Although some patients experienced mild influenza-like adverse reactions during treatment, patients who continued to receive the vaccine showed a durable and strong anti-tumor cell immune response [31]. The following Phase II trial (NCT04526899) met its primary endpoint, with an objective response rate of 18.1% for the BNT111/cemiplimab combination and 17.4% for BNT111 monotherapy. At a median follow-up of 15.7 months, the median overall survival was 20.7 months in the combination arm.
2.1.2. mRNA Encoding TSAs
Although incorporating multiple TAAs into a single vaccine can enhance antitumor immunity, TAA vaccines still risk inducing central or peripheral immune tolerance. In contrast, TSAs arise from tumor-specific mutations and are absent in normal tissues, and therefore, they do not induce immune tolerance. Consequently, TSA vaccines are more attractive than TAA vaccines [32]. The formulation of TSA vaccines first requires sampling a patient’s tumor tissue for comprehensive sequencing, including whole-exome, RNA, or transcriptome analysis. Comparative assessment between tumor and normal tissue sequencing discerns non-synonymous somatic mutations in the tumor, including point mutations and insertion-deletions. Subsequently, screening and analysis identify mutations exhibiting heightened immunogenicity using MHC I epitope prediction algorithms (Figure 4). A judicious selection of TSA involves integrating analytical results with in vitro binding experiments [33]. This patient-specific workflow directly supports the customization of mRNA vaccines, as each individual’s unique mutational landscape dictates the final neoantigen composition. The entire pipeline can be completed within a clinically actionable timeframe, enabling rapid, tailored intervention. Recent breakthroughs with the personalized mRNA-4157 vaccine (NCT05933577) have validated this customized strategy, demonstrating improved outcomes in melanoma patients when combined with immune checkpoint blockade.

Figure 4. (A) Workflow of a tumor neoantigen mRNA vaccine. Tumor cells are isolated from the patient, followed by next-generation sequencing to identify neoantigens. After sequence verification, the mRNA corresponding to the identified neoantigens is synthesized and used in clinical trials. (B) Mechanisms of neoantigen-mediated mRNA tumor vaccine. Antigens derived from tumor cells are presented by antigen-presenting cells (APCs) via MHC class I and class II molecules. APCs activate CD4+ and CD8+ T cells through T-cell receptor (TCR) engagement. Activated T cells secrete cytokines and mediate tumor cell death.
Several TSA vaccines have advanced into clinical trials. IVACMUTANOME, a naked mRNA vaccine encoding multiple neoantigens, was developed by BioNTech for melanoma treatment. In a clinical trial (NCT02035956), intravenous administration of IVACMUTANOME to patients with advanced melanoma was well tolerated and elicited a cellular immune response in 75 out of 125 patients [34]. In a collaborative effort between Moderna and Merck, mRNA-5671, a TSA vaccine targeting KRAS driver mutations (G12C, G12D, G12V, and G13C), was developed. It is used for the treatment of pancreatic cancer by intramuscular injection through the combination of lipid nanoparticles with Pembrolizumab (PD-1 specific antibody). The results of the Phase I clinical trial showed limited KRAS-specific T-cell responses and manageable safety, with further evaluation needed to determine clinical activity (NCT03948763) [35]. Another notable TSA vaccine, mRNA-4157, comprises mRNA encoding up to 34 TSAs. It was formulated in conjunction with Pembrolizumab for adjuvant therapy in high-risk melanoma patients post complete resection. Results from the Phase IIb clinical trial (NCT03897881) showed a 49% reduction in the risk of recurrence or death compared with Pembrolizumab alone, accompanied by a significant TSA-specific cellular immune response [36]. Autogene cevumeran (BNT122), a TSA vaccine co-developed by BioNTech and Genentech, a subsidiary of Roche, was used to treat pancreatic ductal adenocarcinoma (PDAC). BNT122 was synthesized in real time from surgically resected tumors and was used to treat patients in combination with chemotherapy (mFOLFIRINOX, comprising folinic acid, fluorouracil, irinotecan, and oxaliplatin) and atezolizumab (anti-PD-L1 monoclonal antibody) (NCT04161755). 8 out of 16 produced significant T-cell responses and had a longer median relapse-free survival than those without vaccine-expanded T cells [37].
These results show the robust immunogenicity and favorable tolerability of TSA vaccines. However, the current cost of research and development significantly limits the widespread application of TSA vaccines.
2.2. Infectious Disease Vaccines
mRNA vaccines introduce mRNA encoding antigens into the body and utilize the host cell’s protein synthesis machinery to produce antigens that trigger immune responses. Typically, the mRNA sequence of a specific antigen can be constructed according to the characteristics of different diseases. The mRNA is encapsulated within nanocarriers, delivered into cells, and then the ribosome translates the mRNA sequence to produce antigen proteins. After antigen proteins are secreted, these proteins are recognized by the immune system, eliciting protective immune responses to prevent disease [2]. The use of mRNA as viral vaccines offers several advantages: (1) mRNA vaccines can activate the immune system by mimicking natural viral infection, potentially inducing stronger and more durable immune responses; (2) Multiple mRNAs can be packaged in the same vaccine, which improves the suitability of the vaccine; (3) mRNA vaccines can be discovered and produced more rapidly than protein-based vaccines, enabling faster responses to infectious outbreaks; (4) Different mRNA vaccines can be made using the same manufacturing process and facilities [25].
The first COVID-19 vaccine, BNT162b2 (Pfizer/BioNTech), received emergency use authorization from the FDA. It is delivered via LNPs through intramuscular injection, and the mRNA is translated into spike proteins in the body, triggering B cell and T cell immune responses [38]. The subsequent COVID-19 vaccine, mRNA-1273, follows a similar principle. After vaccination, cells produce the S protein found on the surface of SARS-CoV-2. The body recognizes this antigen and generates antibodies to resist subsequent viral infection [39].
In the early stages of the COVID-19 pandemic, the BNT162b2 vaccine from Pfizer/BioNTech and the mRNA-1273 vaccine from Moderna employed different codon optimization strategies. mRNA-1273 almost exclusively used codons corresponding to the most abundant tRNA species, whereas BNT162b2 also incorporated some rare codons [40]. This difference may reflect that the tRNAs considered most abundant by BioNTech are also heavily consumed, and that moderate use of rare codons can improve protein expression efficiency. BNT162b2 uses a split poly(A) tail design, where the poly(A) sequence is segmented into A(30) and A(70) linked by a GCATATGACT spacer. Both vaccines replace uridine triphosphate (UTP) with N1-methylpseudouridine triphosphate, contributing to their high efficacy, 94.1% for mRNA-1273 and 95% for BNT162b2 against symptomatic COVID-19 [41].
Rabies is an acute, fatal, zoonotic infectious disease with a 100% case fatality rate once symptoms appear. According to WHO statistics, more than 150 countries and regions in the world have rabies epidemics, and about 59,000 people die from rabies every year [42]. The traditional rabies vaccine requires four doses, and the administration schedule is complicated. CureVacAG developed CV7201, an mRNA vaccine encoding the rabies virus glycoprotein (RABV-G), formulated with cationic protamine [43]. This was the first proof-of-concept clinical trial of a prophylactic mRNA vaccine in humans. Subsequently, CureVacAG optimized the LNP formula and produced CV7202.
3. Protein Replacement Therapy
mRNA can carry information from any gene; thus, in theory, it can produce almost any functional protein/peptide for protein replacement therapy. Since mRNA is a template for protein translation, protein replacement therapies based on mRNA drugs overcome the obstacles of post-translational modification (PTM), folding, assembly, and localization of exogenously expressed proteins [44]. In addition, mRNA can be produced and manufactured faster, more flexibly, more conveniently, and at a lower cost than protein drugs. Furthermore, unlike DNA therapy, mRNA does not need to enter the nucleus to function, which confers a very low risk of genomic integration or insertional mutagenesis [45].
Protein replacement therapy requires either high levels of protein expression or prolonged mRNA expression, which can be achieved by improving mRNA stability (Figure 5). Self-amplifying mRNA (saRNA) encodes not only the antigen but also sequences derived from viral replication machinery, enabling it to replicate within cells and enhance protein expression [46]. saRNA encoding target proteins is conducive to achieving higher and more durable protein expression. However, the expression level of saRNA-encoded proteins gradually declines over time due to host innate immune responses. Therefore, it is necessary to optimize the backbone sequence of saRNA vectors, enhance their expression intensity and duration, and reduce the host innate immune response [47]. A series of strategies has been employed to optimize saRNA sequences, including in vitro evolution of saRNA, split-saRNA systems, construction of trans-amplifying mRNA (taRNA), and co-expression of IFN signaling inhibitors [48]. Trans-amplifying mRNA (taRNA) is a split-vector derivative of saRNA and represents a promising vaccine platform. In this system, the replicase and the antigen-encoding gene are placed on two separate mRNA molecules, thereby improving safety and reducing the size of each mRNA. Upon translation, the replicase amplifies the trans-replicon (TR) RNA that codes for the antigen, thereby achieving effective immunization with a minimal amount of TR [49,50].
Circular RNA (circRNA) is a class of single-stranded, covalently closed RNA molecules generated from pre-mRNA through alternative splicing [51]. circRNA can be expressed for a long duration and exhibits low immunogenicity. In contrast to linear mRNA, circRNA lacks a 5′ cap and can therefore undergo cap-independent translation. In protein replacement therapy, the activation of innate immunity may inhibit the protein translation process and cause cytotoxicity, which should be avoided. circRNA has higher cellular stability and lower immunogenicity than its linear counterpart, resists exonuclease degradation in vitro, and also evades immune-induced decay mechanisms in vivo [52]. The design of circRNA should focus on three key elements, including autocatalytic introns, internal ribosome entry sites (IRES), and ORFs. Autocatalytic introns significantly affect the circularization efficiency of RNA, so screening and optimizing highly activated autocatalytic introns can also help improve the effect of circRNAs [53]. The ORF design of circRNA is similar to that of linear mRNA, but it does not involve base modifications. IRES are critical for circRNA translation efficiency and the regulation of tissue-specific expression, making them the primary focus of sequence design [54].
Figure 5. Schematic of mRNA-based protein replacement therapy. LNPs loaded with therapeutic mRNA are taken up by cells via endocytosis. After endosomal release, mRNA binds to ribosomes and is translated into functional proteins. Compared with conventional linear mRNA, three alternative formats offer distinct advantages: (1) Self-amplifying RNA (saRNA) enhances the intensity and duration of protein expression through backbone optimization while reducing host immune responses. (2) Trans-amplifying RNA (taRNA) avoids the size limitation of the gene of interest (GOI) and promotes efficient protein expression. (3) Circular RNA (circRNA), which lacks a 5′ cap and base modifications, supports efficient cap-independent translation and exhibits low immunogenicity.
3.1. Cancer Therapy
3.1.1. mRNA Encoding Immunostimulatory Factors
Immunostimulatory factors, primarily cytokines and chemokines, play a pivotal role in promoting the maturation and activation of APCs. These factors generate anti-tumor cellular immunity and influence immune cell phenotypes, thereby modulating the tumor microenvironment (TME). Notably, interleukin-2 (IL-2), approved by the FDA in 1992 for metastatic renal cell carcinoma, and interferon-α2b (IFNα2b), approved in 1995 for high-risk resectable melanoma, represent groundbreaking achievements in immunotherapy [55]. However, the clinical approval of cytokines remains limited, mainly due to their short half-lives and the difficulty of achieving optimal concentrations within the TME. The advent of mRNA technology holds promise in swiftly and cost-effectively generating substantial quantities of cytokines intracellularly. Encapsulation of cytokine-encoding mRNA in nanoparticles prolongs its half-life in the TME [56].
Administration of IL-2 variant mRNA encapsulated in lipid nanoparticles via intravenous injection enhanced the proliferation of antigen-specific CD8+ T cells in tumor-bearing mice, with no significant increase in regulatory T (Treg) cell numbers [57]. In recent years, IL-12 has emerged as a prominent cytokine that activates T lymphocytes, promotes IFN-γ secretion to kill tumor cells, and recruits immune cells for cancer therapy. Studies employing IL-12 mRNA in hepatocellular carcinoma (HCC) mouse models showcased potent anti-tumor immune responses, inducing CD4+ T cell infiltration, IFN-γ production, and substantial tumor suppression [58]. MEDI1191, an mRNA-based therapy developed by Moderna, showed promising outcomes in patients with advanced solid tumors when administered in combination with durvalumab (NCT03946800) [59].
Notably, mRNA mixtures encoding multiple cytokines exhibit enhanced anti-tumor immune responses. For instance, intratumoral administration of LNPs containing a mixture of IL-23, IL-36, and OX40L mRNA, developed by ModernaTX, produced a robust anti-tumor response in Phase I clinical evaluation (NCT03739931) [60]. In addition, TriMix-based mRNA immune adjuvants, consisting of three naked mRNA molecules encoding CD70, CD40L, and constitutively active TLR4 (caTLR4), are undergoing clinical evaluation. CD70 and CD40L induce CD8+ and CD4+ T cell activation, respectively, while caTLR4 promotes antigen presentation. These adjuvants exhibited favorable tolerance and immunogenicity in several clinical trials. A clinical investigation using mRNAs encoding TAAs such as MAGE-A3, tyrosinase, gp100, and PRAME in melanoma treatment demonstrated robust immune responses at tumor sites, yielding promising clinical outcomes and improved patient survival (NCT01676779) [61].
3.1.2. mRNA Encoding Monoclonal Antibodies
Antibody-mediated tumor immunotherapy has garnered significant attention and witnessed rapid advancements in recent years. However, the susceptibility and high production costs of individual antibodies have somewhat constrained their widespread application. In contrast, antibodies encoded by mRNA offer prolonged half-lives and diminished production costs compared to directly administered monoclonal antibodies [62]. To date, mRNA has been engineered to express a variety of antibodies, including monoclonal antibodies (mAbs), bispecific T cell-engaging antibodies (bsAbs), and their derivatives. Notably, mRNA encoding the anti-HER2 antibody (trastuzumab), when delivered via the LNP system, effectively suppressed the growth of HER2-expressing tumors and significantly improved pharmacokinetics compared to direct injection of the trastuzumab protein [63].
In contemporary tumor immunology, the programmed cell death protein 1/programmed death ligand 1 (PD-1/PD-L1) pathway has been widely studied for its role in immune inhibition within tumors. Consequently, numerous anti-tumor immunotherapies centered on this pathway have emerged. Wu et al. investigated the delivery of mRNA encoding pembrolizumab (an anti-PD-1 monoclonal antibody) using LNPs to treat mice bearing MC38 tumors. This approach exhibited superior pharmacokinetics and triggered a more potent anti-tumor immune response compared to direct injection of the pembrolizumab protein [64]. Bispecific T cell-engaging antibodies (bsAbs) have shown significant efficacy in several hematologic malignancies, such as acute lymphoblastic leukemia and non-Hodgkin lymphoma. However, the complexity of the production process and the transient half-life of the antibodies synthesized in serum necessitate further optimization of this approach. More recently, Huang et al. employed an LNP-based system to deliver mRNA encoding B7H3×CD3 bsAbs, effectively extending the half-life of bsAbs and demonstrating robust efficacy in the treatment of hematologic malignancies and melanoma. This study highlights the potential research value and extensive clinical application prospects of bsAbs in cancer therapy [65].
3.1.3. mRNA Encoding Tumor Suppressors
Tumor suppressor genes play a pivotal role in inhibiting cell proliferation and thereby preventing tumor progression. However, they are frequently lost or inactivated in various tumors. Delivery of mRNA encoding tumor suppressors to the tumor site accelerates the expression of these genes, thereby modulating tumor cell proliferation. Currently, extensive research has focused on the tumor suppressor genes PTEN and TP53 [66]. Systemic delivery of synthetic PTEN mRNA using polymer-lipid hybrid nanoparticles restores the missing PTEN protein at the tumor site. These nanoparticles, composed of the lipid compound G0-C14, polylactic-co-glycolic acid (PLGA), and DSPE-PEG, encapsulate PTEN mRNA and inhibit the intracellular phosphatidylinositol 3-kinase (PI3K-AKT) pathway, thereby promoting cell apoptosis. Notably, this approach inhibits tumor growth in a murine model of prostate cancer [67]. Furthermore, PTEN expression enhances tumor sensitivity to chemotherapy and immune checkpoint blocking therapy, thus impacting the tumor immune microenvironment. Lin et al. developed a nanoparticle composed of G0-C14 and mPEG-PLGA copolymers and encapsulating PTEN mRNA. This nanoparticle induced autophagy in tumor cells, promoting the release of damage-associated molecular patterns, which greatly enhances immune checkpoint blockade (ICB) sensitivity. Combined treatment with anti-PD-1 antibodies showed potent anti-tumor effects in a mouse model of PTEN-null prostate cancer [68].
Another important tumor suppressor gene, TP53, is pivotal in preventing aberrant cell cycle progression and promoting apoptosis. Mutation of TP53 occurs in approximately 50% of human cancers. Delivery of TP53 mRNA coated within redox-responsive nanoparticles for tumor therapy has demonstrated significant therapeutic effects in TP53-deficient hepatocellular carcinoma and non-small cell lung cancer models. This approach enhances tumor sensitivity to Everolimus, an mTOR inhibitor [69]. Furthermore, innovative strategies combining TP53 mRNA with other treatments have been explored. For instance, ROS-responsive polymer nanoparticles delivering TP53 mRNA and indocyanine green (ICG) trigger the production of p53 protein in the ROS-rich tumor environment. Concurrently, the released ICG generates ROS under 808 nm laser irradiation, inducing effective photodynamic therapy, thus demonstrating safe and efficacious anti-tumor effects in a murine lung cancer model [70].
3.2. Infectious Disease
COVID-19 neutralizing antibodies are used for the prevention and treatment of COVID-19 infection as monoclonal antibody drugs. With rapid antibody elevation and a long half-life, neutralizing antibodies can prevent COVID-19 in immunocompromised individuals and those unsuitable for vaccination. Compared with small-molecule drugs, neutralizing antibodies offer the advantages of better safety, fewer contraindications, and suitability for a broader patient population [71]. Neutralizing antibodies are part of the immune system’s response to invading pathogens. In a collaboration between the University of Washington and Vir Biotechnology, memory B cells from a patient who had recovered from SARS-CoV-1 infection in 2003 were analyzed, leading to the identification of a neutralizing antibody named S309. This antibody binds to a highly conserved epitope in the receptor-binding domain of the spike protein. It not only neutralizes SARS-CoV-1 but also shows neutralizing activity against SARS-CoV-2 and many other coronaviruses. S309 is the precursor of sotrovimab, which has received emergency use authorization from the FDA [72].
For human respiratory syncytial virus (RSV), Tiwari et al. developed an engineered mRNA-encoded membrane-anchored neutralizing antibody based on palivizumab, which exhibited higher efficiency than palivizumab and significantly inhibited RSV when measured 7 days after transfection [73]. A neutralizing monoclonal antibody CHKV-24, originally isolated from B cells of a survivor of natural chikungunya virus infection, was successfully expressed from synthetic mRNA, achieving high levels in vivo and reducing viremia to undetectable levels 2 days after inoculation [74]. Intramuscular delivery of replicon RNA encoding the ZIKV117 monoclonal antibody via lipid nanocarriers boosted antibody expression and protected mice from ZIKV117 infection [75].
3.3. Autoimmune Disease
Autoimmune diseases (AIDs) are caused by a breakdown of immune tolerance to self-antigens, leading to immune responses against the body’s own tissues. Typical examples include systemic lupus erythematosus, rheumatoid arthritis, and myasthenia gravis. Currently, the main therapeutic approaches for AIDs include drug therapies such as immunosuppressants, nonsteroidal anti-inflammatory drugs (NSAIDs), and glucocorticoids [76]. However, current drug therapies for AIDs are broad-spectrum and highly non-specific, often causing side effects such as infections and malignancies. Therefore, developing novel medicine for precise treatment, along with integrating therapy and prevention, represents a key direction for current research [77].
mRNA therapy offers significant advantages for the treatment of AIDs. In theory, mRNA drugs can be used to treat any disease by directly producing the required proteins and enabling continuous regulation of AIDs. Moreover, mRNA drugs are much more cost-effective than protein drugs for achieving comparable efficacy [78]. Moderna has developed two potential drugs, mRNA-6231 and mRNA-6981, designed to engage peripheral tolerance pathways, inhibit autoimmune activation, and help restore immune homeostasis, thereby reducing autoimmune responses. IL-2 is a key survival factor for Tregs, promoting Foxp3 expression and the production of immunomodulatory cytokines. mRNA-6231 is an LNP-formulated mRNA encoding an IL-2 mutant protein fused with human serum albumin, which completed its first Phase I clinical trial in 2024. Another Moderna mRNA drug, mRNA-6981, was designed to encode PD-L1 to treat autoimmune diseases [79].
3.4. Genetic Disease
Moderna developed mRNA-3927 to treat propionic acidemia (PA) by encoding the α and β subunits of the mitochondrial enzyme propionyl-CoA carboxylase (PCC) and delivering it to patients [80]. In a first-in-human Phase 1/2 trial, interim analyses reported a 76% relative reduction in the risk of metabolic decompensation events, with early signs of clinical benefit and infrequent treatment-limiting side effects [81]. Moreover, in January 2026, Moderna entered a strategic collaboration with Recordati to accelerate the clinical development and future commercialization of mRNA-3927 for PA.
In addition, Arcturus Therapeutics has developed the ARCT-810 therapy, which is designed to enable ornithine carbamyltransferase (OTC) deficient patients’ own liver cells to naturally produce functional enzymes to treat OTC deficiency [82]. Preclinical data in mouse models of OTC deficiency suggest that administration of ARCT-810 enhances the expression and activity of the OTC enzyme, thereby improving urea production and plasma ammonia, and improving survival [83]. The treatment is currently being evaluated in a Phase II clinical study.
3.5. Cardiovascular Disease
To date, most drugs used to treat cardiovascular disease are still small molecule drugs. Currently, cardiovascular-related RNA therapies entering clinical trials mainly involve antisense oligonucleotide (ASO) or small interfering RNA (siRNA) technologies to knock down the expression of target proteins. In addition, mRNA therapy has shown relevant applications in cardiovascular disease, with several clinical trials already underway [84].
Vascular endothelial growth factor (VEGF) promotes cell proliferation, induces angiogenesis, improves local blood flow, and nourishes surrounding cardiomyocytes, thereby preventing tissue damage [85]. mRNA-based VEGF therapy has attracted considerable attention. The first cardiovascular-related mRNA drug to enter clinical trials was Moderna’s mRNA encoding VEGF-A. Using modified mRNA encoding VEGF-A, Gan et al. administered intradermal injections to male patients with type 2 diabetes mellitus. Skin microdialysis revealed elevated VEGF-A protein levels at the mRNA treatment site for approximately 4 to 24 h after administration, and the therapy was well tolerated [86]. Based on these studies, the Phase IIa EPICCURE trial (NCT03370887) was conducted, evaluating epicardial AZD8601 injections in patients with moderately decreased left ventricular function undergoing elective coronary artery bypass grafting surgery. The EPICCURE trial reported that epicardial AZD8601 injection was well-tolerated. After six months, all seven treated patients had NT-proBNP levels below the heart-failure threshold, compared with one of four placebo patients, indicating potential improvement in cardiac function [87].
3.6. Cystic Fibrosis
Cystic fibrosis is a monogenic autosomal recessive disorder caused by mutations in the cystic fibrosis transmembrane conductance regulator (CFTR) gene, which encodes epithelial ion channels responsible for chloride and bicarbonate transport. These mutations impair mucus hydration and clearance, leading to the disease, and restoring CFTR function is a common therapeutic strategy. Previous studies have shown that CFTR mRNA can be highly expressed in human epithelial cells, and that CFTR mRNA transfection represents a new gene therapy option for restoring defective CFTR function [88]. Robinson et al. intranasally administered CFTR mRNA-loaded LNPs to CFTR knockout mice, achieving 55% of the net chloride efflux observed in healthy mice [89]. Additionally, MRT5005, a CFTR mRNA-based drug, was evaluated in a Phase I/II clinical trial, though it did not meet the primary efficacy endpoint [90].
4. Gene Editing Therapy
Gene editing is a genetic engineering technology that enables precise modification of specific target genes within an organism’s genome. Gene editing therapy mainly relies on CRISPR-based technologies. (Figure 6) According to the latest evolutionary classification, CRISPR-Cas systems are divided into two classes, seven types, and forty-six subtypes. Class I systems utilize a multiprotein CRISPR RNA (crRNA) effector complex and currently include types I, III, IV, and VII. Class II systems employ a single Cas protein as the endonuclease effector and encompass types II, V, and VI [91].
Researchers have attempted to optimize various components of the CRISPR system, and current efforts focus on the chemical modification of crRNA, which can rationally optimize crRNA-protein interactions. Native Cas9 uses two RNAs, a 42-nucleotide long crRNA and an 80-nucleotide long trans-activated crRNA (tracrRNA), to guide sequence-specific recognition and dsDNA cutting. crRNA and tracrRNA form a partially complementary complex, in which crRNA carries the DNA-recognition sequence, while tracrRNA mediates association with the Cas9 protein. In genome editing and related techniques, the two RNAs are typically joined via a GAAA tetra-loop to form a 102-nucleotide single guide RNA (sgRNA) [92]. The earliest proposed method to improve crRNA specificity is to reduce the number of base pairs in the target DNA complex, which likely reflects a reduction in the binding energy between sgRNA and the target DNA [93]. Ribose modifications of Cas9 crRNA include 2′-F, 2′-OMe substitutions, and the formation of bicyclic ribose. 2′-F modification increases the metabolic stability of antisense oligonucleotides, whereas 2′-OMe improves metabolic stability and reduces off-target activity [94]. A study by Bennett et al. found that 2′-F modification in the PAM-distal region of the crRNA spacer was well tolerated, as detected by the Surveyor assay in HEK293T cells transfected with protein granules encoding tracrRNA and Cas9 [95]. Another common modification targets the phosphate groups of Cas9 crRNA. Substituting sulfur for a non-bridging phosphate oxygen to form a phosphorothioate linkage can improve enzymatic stability but reduce the affinity between the modified oligonucleotide and its complementary target [96]. This approach is widely used for antisense oligonucleotides and siRNAs. Moreover, other studies have shown that conserved regions of sgRNA cannot be completely modified, and even partial modification can reduce its activity [97].
Figure 6. Schematic of mRNA-based gene editing. Cas9 mRNA and single-guide RNA (sgRNA) are assembled in vivo to form a ribonucleoprotein (RNP) complex, which binds to the target DNA for gene knockout. The broken DNA is then repaired via non-homologous end joining (NHEJ) or homology-directed repair (HDR).
4.1. Cancer Therapy
Genome editing enables the deletion, insertion, or alteration of specific DNA sequences within the host genome. Compared with conventional cancer therapies, CRISPR-Cas9 can permanently disrupt tumor cell survival genes, avoid the need for multiple repeated doses, and thereby improve therapeutic outcomes [98]. Currently, CRISPR-Cas9 systems can be delivered in the form of RNA, DNA, or ribonucleoprotein (RNP). Compared with DNA and RNP delivery, the co-delivery of Cas9 mRNA and sgRNA is a more attractive approach, offering higher efficacy and safety. After entering the target cell, Cas9 mRNA is translated into Cas9 nuclease in the cytoplasm, which then forms Cas9/sgRNA complexes with specific sgRNAs, ultimately enabling efficient genome editing [99]. Most current studies employ LNPs for the co-delivery of Cas9 mRNA and sgRNA. Rosenblum et al. used a developed LNP platform to co-deliver Cas9 mRNA and sgPLK1, achieving approximately 70% gene editing and 50% tumor suppression in glioblastoma cells [100]. When using LNP systems, organ-targeted gene editing can be achieved by modulating LNP composition. For example, adding selective organ targeting (SORT) molecules to LNPs enables targeting to the liver, spleen, or lung based on different surface charges [101]. In addition to gene knockdown, gene correction via homology-directed repair can also be used for tumor therapy. A study showed that simultaneous delivery of Cas9 mRNA, sgRNA, and single-stranded DNA via LNPs achieved efficient reporter gene correction in xenograft tumors [102].
4.2. Infectious Disease
Using CRISPR tools to knock in resistance genes or destroy pathogenic genes offers a promising strategy for preventing or treating infectious diseases. Xu et al. identified a 27-year-old male patient suffering from both acquired immunodeficiency syndrome (AIDS) and acute lymphoblastic leukemia. Using the CRISPR-Cas9 system, they edited the C-C chemokine receptor type 5 (CCR5) gene in CD34+ hematopoietic stem and progenitor cells and successfully performed the first gene-edited stem cell treatment for both AIDS and leukemia [103]. A follow-up study reported by the same team in NEJM in 2019 confirmed that no CCR5-edited cells carried off-target mutations, and the patient remained in stable remission without requiring antiretroviral therapy for over 18 months [104]. In November 2020, researchers from Temple University and the University of Nebraska Medical Center successfully excised simian immunodeficiency virus (SIV) from the genomes of non-human primates [105]. This breakthrough brought humanity closer than ever to developing a complete cure for AIDS, and the team subsequently licensed the technology to Excision BioTherapeutics, paving the way for clinical translation.
4.3. Autoimmune Disease
CAR-T therapy is now widely being explored for AIDs. CRISPR technology enables reprogramming of human T cells without viral CAR vectors, but ethical and legal issues remain. Roth et al. developed a CRISPR/Cas9 system that inserts large DNA sequences at specific T cell genomic loci while maintaining cell viability. This strategy corrected the IL2RA mutation in cells from patients with monogenic autoimmune diseases and restored signal transduction [106]. CRISPR-based neoantigen identification for cancer may later be applied to uncover hidden self-antigens in autoimmune diseases.
4.4. Genetic Disease
Hereditary amyloidosis (ATTR) is a rare, progressive disease caused by TTR gene mutations, leading to misfolded transthyretin protein and amyloid deposition in the heart, nerves, and digestive system. NTLA-2001 is the first intravenously administered CRISPR therapy. In a Phase I trial, LNPs delivering spCas9 mRNA and sgRNA to the liver achieved over 90% reduction in mutant TTR protein in a dose-dependent manner, with maximal effect by day 28. The reduction persisted throughout the observation, supporting NTLA-2001 as a potential single-dose therapy [107].
Hereditary angioedema (HAE) is a complement disorder characterized by episodic skin and mucosal edema and associated with decreased C1 inhibitor levels. An in vivo CRISPR therapy, NTLA-2002, was evaluated in a Phase 1/2 trial involving 10 adults. It demonstrated dose-dependent kallikrein reduction, with reductions of 64% at a dose of 25 mg, 81% at 50 mg, and 92% at 75 mg. During weeks 1 to 16, attack frequency decreased by 91% in the 25 mg group and by 78% in the 75 mg group. The first three patients remained attack-free for 5.5 to 10.6 months. NTLA-2002 was well tolerated with only mild adverse events, demonstrating the efficacy and translational potential of CRISPR-based gene editing [108].
Hemophilia is an X-linked disorder due to mutations in factor VIII or IX, causing bleeding episodes. Han et al. developed LNPs to deliver Cas9 mRNA and sgRNA targeting mouse antithrombin (mAT) to the liver. This restored thrombin production in hemophilia mouse models, improved clotting and bleeding parameters, and caused no detectable off-target effects, hepatotoxicity, or severe immune responses [109]. Additionally, valoctocogene roxaparvovec, an AAV-based gene therapy for severe hemophilia A, has received conditional marketing approval from the EMA.
4.5. Cardiovascular Disease
The CRISPR-Cas system is widely used for gene editing in cardiovascular disease. Proprotein convertase subtilisin/kexin type 9 (PCSK9) is a key target, mainly produced in the liver, and elevates plasma low-density lipoprotein cholesterol (LDL-C) levels [110]. Musunuru et al. used an LNP-delivered CRISPR-Cas system to knock out PCSK9 in live monkeys, successfully inducing loss of PCSK9 function. This led to approximately 90% and 60% reductions in circulating PCSK9 and LDL-C levels, respectively [111].
Another cardiovascular gene editing target is ANGPTL3, also primarily produced by the liver. ANGPTL3 inhibits both lipoprotein lipase and endothelial lipase, thereby regulating muscle free fatty acid uptake, adipose tissue lipogenesis, and hepatic LDL-C and cholesterol uptake. In a Phase 1 trial (NCT06164715), 15 patients with refractory dyslipidemia received a single intravenous dose of CTX310, an LNP-encapsulated CRISPR-Cas9 therapy targeting hepatic ANGPTL3. The treatment was well tolerated, with no dose-limiting toxicities, and resulted in dose-dependent reductions in ANGPTL3 protein, LDL-C, and triglycerides, with reductions of up to approximately 50% in LDL-C and 55% in triglycerides at higher doses [112].
mRNA-based CAR-T cell therapy has also been applied to treat cardiac fibrosis. Aghajanian et al. demonstrated that CAR-T cells could target and eliminate activated cardiac fibroblasts to restore heart function [113]. Additionally, Rurik et al. generated transiently functional CAR-T cells in vivo by delivering modified mRNA using T-cell-targeted LNPs. This strategy led to a marked reduction in cardiac fibrosis and restoration of normal heart size and function in C57BL/6 mice [114].
5. Strategies for Next-Generation mRNA Therapeutics
5.1. Strategies for Extrahepatic Targeted Delivery
Systemic administration of mRNA-LNPs is inherently biased toward liver accumulation, a property largely governed by the adsorption of apolipoprotein E (ApoE) and low-density lipoprotein receptor (LDLR) mediated uptake by hepatocytes [6,115]. While this natural tropism is advantageous for treating hepatic diseases, it severely limits the application of mRNA therapeutics to extrahepatic disorders. To overcome this fundamental barrier, two major strategies have been pursued: alternative administration routes and carrier engineering approaches that redirect LNPs biodistribution.
5.1.1. Advances in Administration Routes
For pulmonary diseases, inhalation delivery is a highly attractive strategy for achieving efficient mRNA enrichment in the lungs. Although the high shear forces generated during nebulization pose substantial challenges to the stability of both mRNA and nanocarriers, several studies have successfully developed strategies to overcome these barriers [116,117]. Liu et al. developed a charge-assisted stabilization (CAS) strategy that induces electrostatic repulsion among LNPs to enhance colloidal stability, thereby enabling efficient pulmonary mRNA delivery in mice, dogs, and pigs [118]. Jiang et al. replaced the PEG-lipid with a zwitterionic polymer-lipid conjugate, whose hydration layer buffers the shear stress during nebulization, significantly enhancing aerosol stability [119].
Intraperitoneal administration offers an efficient strategy for the treatment of pancreatic diseases. Studies have shown that nanocarriers delivered via the intraperitoneal route can achieve more effective targeting and penetration of pancreatic tissues relative to other organs [120]. Qiu et al. developed a library of thioketal-incorporated ionizable lipids (TBILs) for pancreas-targeted mRNA delivery. The optimized formulation achieved 98.3% pancreatic targeting specificity upon intraperitoneal injection [121].
The presence of the blood-brain barrier (BBB) remains a critical barrier to mRNA-based therapies for brain diseases, as conventional carriers generally cannot cross this barrier effectively [122]. Intranasal administration has been shown to bypass the BBB via the olfactory/trigeminal nerve pathways, effectively promoting the enrichment of LNPs in brain tissues [123]. Intracerebral injection, while enabling more direct delivery to the brain parenchyma, is limited by its high invasiveness and technical demands [124]. In contrast, intrathecal injection directly delivers mRNA into the cerebrospinal fluid (CSF), bypassing the BBB and achieving efficient expression in the central nervous system (CNS) [125].
5.1.2. Optimization of Delivery Systems
Surface modification with targeting ligands represents the most commonly employed active targeting strategy for extrahepatic delivery, including targeting peptides, antibodies, and aptamers [126,127,128,129]. However, targeting ligand modification strategies are still hampered by inherent limitations such as complex conjugation chemistry, poor in vivo stability, and protein corona shielding [130]. This has prompted growing interest in endogenous targeting strategies that exploit the intrinsic protein corona by tuning LNP lipid composition to achieve organ-specific delivery. De novo design of carriers represents another attractive strategy, with numerous studies synthesizing and screening polymers and ionizable lipids to achieve organ and cell targeting [131]. Deng et al. reported a series of acylhydrazone-based ionizable lipids that exploit pH-responsive E/Z isomerization to modulate LNP membrane properties, enabling spleen-specific targeting and potent immune activation [132]. Chen et al. designed a class of crown-like biodegradable ionizable lipids (CBILs) that enable lung-selective mRNA delivery in vivo through zinc coordination [133].
Compared with de novo screening of novel ionizable lipids, introducing a fifth component into conventional four-component LNPs represents a more straightforward and widely adopted strategy for extrahepatic targeting, known as selective organ targeting (SORT) [134]. Cheng et al. demonstrated that incorporating permanently cationic quaternary ammonium lipids into LNPs markedly enhanced lung tropism, whereas inclusion of anionic lipids conferred spleen-targeting properties. Further studies revealed that this targeting specificity is mediated by the interaction between surface-bound proteins on LNPs and cognate receptors highly expressed in specific tissues [135]. This strategy has recently been extended by the same group to polymer systems bearing diverse charged moieties [136].
In addition to the strategies described above, other non-conventional approaches have also been explored to expand the delivery landscape. Nie et al. covalently conjugated mRNA-LNPs onto erythrocytes to achieve selective mRNA delivery to splenic myeloid cells via red blood cell homing [137]. Huang et al. developed an engineered RNACap capsule for oral mRNA delivery to the intestine, enabling release via pH-responsive coating and peristaltic contraction [138].
5.2. AI for mRNA Therapies
Artificial intelligence (AI) is emerging as a transformative force in mRNA therapeutics, reshaping sequence design, lipid discovery, and formulation optimization. Traditional approaches, heavily reliant on empirical screening and iterative cycles, are frequently constrained by the vast complexity of sequence space and chemical diversity. AI, in contrast, can learn complex relationships from large-scale data and explore this vast design space efficiently, thereby opening up new avenues for mRNA therapeutic development [139,140].
5.2.1. Neoantigen Discovery
Although mRNA vaccines have emerged as powerful tools against infectious diseases and cancers, the conventional “trial-and-error” approach to antigen optimization often falls short in responding to emerging outbreaks. In the context of personalized cancer vaccines, efficiently screening immunogenic neoantigens from each patient’s mutanome has become a critical bottleneck constraining their development. AI is fundamentally reshaping this landscape, reducing neoantigen identification timelines from weeks to hours, and opening new avenues for rapid-response mRNA vaccines and personalized cancer immunotherapy [141]. Que et al. reported deepAntigen, a graph convolutional network-based framework for atomic-level T cell antigen prediction, validated by ELISPOT assays in lung, breast, and pancreatic cancer patients [142]. Zhao et al. reported UniPMT for peptide-MHC/TCR binding prediction, achieving SOTA performance and a 17.6% AUPR gain on validated tumor neoantigen datasets [143].
5.2.2. mRNA Sequence Design
AI is also revolutionizing mRNA sequence engineering, from UTR design to full-length coding sequence optimization. Xiong et al. reported a BERT-based language model that uses dual tokenization to enable precise 5′UTR design and CDS optimization [144]. Rajbanshi et al. reported a generative language model codonGPT trained on 338,417 sequences that applies reinforcement learning to balance expression, stability, and GC content [145]. Zhang et al. developed GEMORNA, a generative framework for de novo mRNA design. It outperformed benchmarks by 41-fold in luciferase expression, twofold over BNT162b2 in antibody titers, and 15- to 150-fold in erythropoietin expression [146].
5.2.3. Delivery System Design
Ionizable lipids are the core functional components of LNPs. Traditional discovery relies on empirical screening and iterative synthesis, which is time-consuming, costly, and constrained by limited chemical space. AI is fundamentally changing this paradigm by enabling rapid virtual screening of vast lipid libraries and predictive modeling of LNP performance [147]. Witten et al. developed LiON, a deep-learning method that evaluated 1.6 million lipids in silico using directed message-passing neural networks. Trained on over 9,000 LNP activity measurements, the model identified two novel structures that efficiently delivered mRNA to ferret lungs [148]. Xu et al. reported the AGILE platform, which combines deep learning with combinatorial chemistry to enable efficient ionizable lipid library design and in silico screening via deep neural networks [149]. Xu et al. developed LUMI-lab, a self-driving platform that integrates a transformer-based foundation model with an active-learning workflow and autonomously screened over 1700 LNPs, identifying brominated lipid tails as a novel feature for enhanced mRNA delivery [150].
6. Summary and Outlook
Since its discovery in 1961, messenger RNA has evolved from a basic biological concept into a versatile therapeutic platform. The unprecedented success of COVID-19 mRNA vaccines has not only validated the technology but also accelerated its application across diverse disease areas. Currently, mRNA-based therapies are being investigated for cancer, infectious diseases, genetic disorders, autoimmune diseases, and cardiovascular conditions, employing strategies such as mRNA vaccines, protein replacement, monoclonal antibodies, CAR engineering, and CRISPR-based gene editing. Key advantages of mRNA include transient expression without insertional mutagenesis, rapid, scalable manufacturing, and the ability to encode any functional protein. Lipid nanoparticles have become the leading delivery system, enabling extrahepatic targeting and repeated administration. Novel mRNA formats such as self-amplifying mRNA, trans-amplifying mRNA, and circular RNA extend protein expression duration and reduce immunogenicity.
mRNA therapy has potential for development in a variety of disease types, as summarized in Table 2. The clinical translation of mRNA therapeutics now encompasses three major strategies that often converge at the level of delivery and formulation. The first strategy uses mRNA to encode antigens or immunostimulatory molecules for vaccination against cancer and infectious diseases, as seen in personalized neoantigen vaccines that improve recurrence-free survival, especially when combined with checkpoint inhibitors [36,37]. The second strategy delivers mRNA to replace missing or defective proteins, exemplified by mRNA-3927 for propionic acidemia, which achieved a 76% reduction in metabolic decompensation events, as well as candidates for cystic fibrosis and glycogen storage disease type 1a [81]. The third strategy employs mRNA to encode CRISPR-Cas9 components, base editors, or prime editors for durable gene correction, as demonstrated by NTLA-2001 for hereditary amyloidosis with over 90% mutant protein reduction and NTLA-2002 for hereditary angioedema with up to 92% kallikrein reduction [107,151].
Table 2. Current status of mRNA therapy in different diseases.
|
Therapeutic Areas |
Therapeutic Strategy |
Application Field |
Drug |
Encoded Protein |
|---|---|---|---|---|
|
Oncology |
Vaccine |
Pancreatic |
BNT122 |
Multiple neoantigens |
|
Melanoma |
mRNA-4157 |
Multiple neoantigens |
||
|
HPV16-positive solid tumors |
BNT113 |
HPV16 E6 and E7 oncoproteins |
||
|
mRNA encoding Immunostimulants |
Solid tumors |
MEDI1191 |
IL-12 |
|
|
Solid tumors |
mRNA-2752 |
IL-23, IL-36, and OX40L |
||
|
Melanoma |
TriMix mRNA |
Multiple neoantigens |
||
|
Antibody |
Acute lymphocytic leukemia |
None |
bispecific T cell-engaging antibodies (bsAbs) |
|
|
mRNA encoding tumour suppressors |
prostate cancer, hepatocellular carcinoma, and non-small-cell lung cancer |
None |
PTEN, TP53 |
|
|
CAR-T |
metastatic colorectal cancer |
CAR-NK cell |
natural killer group 2 member D |
|
|
Gene editing |
glioblastoma |
None |
Cas9 protein |
|
|
Infectious diseases |
Vaccine |
COVID-19 |
BNT162b2 |
S protein |
|
COVID-19 |
mRNA-1273 |
S protein |
||
|
Rabies |
CV7201 |
Rabies virus glycoprotein |
||
|
Antibody |
ZIKV117 |
None |
ZIKV117 |
|
|
Gene editing |
AIDS |
EBT-101 |
HIV |
|
|
Autoimmune disorders |
Subcutaneous administration |
Treg cell function regulation |
mRNA-6231 |
HSA-IL2m |
|
CAR-T |
Myasthenia gravis |
DESCARTES-08 |
Modified T cells |
|
|
Genetic diseases |
Protein replacement |
PA |
mRNA-3927 |
PCC α, β subunits |
|
OTCD |
ARCT-810 |
OTC protein |
||
|
Gene editing |
ATTR |
NTLA-2001 |
TTR gene |
|
|
HAE |
NTLA-2002 |
KLKB1 gene |
||
|
Cardiovascular diseases |
mRNA encoding VEGF |
Cardiovascular disease |
AZD8601 |
VEGF |
|
Gene editing |
hypercholesterolemia |
None |
PCSK9 gene |
|
|
Other diseases |
Inhaled mRNA therapy |
cystic fibrosis |
MRT5005 |
CFTR |
Across these strategies, mRNA can also encode antibodies, bispecific T cell engagers, and chimeric antigen receptors. Transient mRNA-based CAR-T therapy, such as DESCARTES-08 for myasthenia gravis, has shown clinical improvement with a favorable safety profile, while in vivo generation of CAR-T cells using T-cell-targeted LNPs for cardiac fibrosis eliminates ex vivo manipulation [114,152]. For autoimmune diseases, mRNA-encoded immunomodulators like IL-2 mutein aim to restore immune tolerance, illustrating how the same platform can be redirected from oncologic to non-oncologic indications [153].
Despite these advances, challenges persist in delivery beyond the liver, immunogenicity upon repeated administration, manufacturing costs for personalized products, and regulatory pathways for combination therapies. Looking forward, the next decade may witness several trends. Non-COVID mRNA therapies, likely for ATTR or PA, may soon receive approval. In vivo CAR-T and gene editing are expected to expand into autoimmune diseases. Multi-functional LNPs capable of co-delivering mRNA and small molecules are under development. Artificial intelligence promises to optimize both mRNA sequences and LNP designs. RNA-based therapies for central nervous system disorders may emerge with improved blood-brain barrier crossing.
In conclusion, mRNA technology has matured into a broadly applicable therapeutic modality. With continued innovation in delivery, engineering, and clinical trial design, mRNA-based drugs are poised to address many intractable diseases, fulfilling their long-promised potential.
Statement of the Use of Generative AI and AI-Assisted Technologies in the Writing Process
During the preparation of this manuscript, the authors used ChatGPT and DeepSeek in order to assist with language editing, structural organization, and refinement of scientific presentation. After using these tools, the authors reviewed and edited the content as needed and take full responsibility for the content of the published article. The authors conceived all scientific concepts, hypotheses, interpretations, and conclusions.
Acknowledgments
The authors thank other lab members for their administrative and technical support.
Author Contributions
J.Z. (Jun Zhao), X.W. and Y.S. drafted, developed, and revised the paper, and conceived the figures. Q.H. and W.J. prepared some of the figures. H.W. and J.Z. (Jia Zhang) organized the tables. Y.L. and X.L. provided valuable and constructive suggestions on the outline and the content, and revised the paper. All authors have read and approved the final version of this paper.
Ethics Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
No new data were generated or analyzed in this review. All data discussed are derived from previously published studies and are cited in the reference list. Data sharing is not applicable to this article.
Funding
This work was funded by the “Pioneer” and “Leading Goose” R&D program of Zhejiang (2025C01109 and 2024DYXS0001), and the joint research program of eye research center (ERC202502), and the support from 2025ZZBS03 of Hangzhou Institute of Medicine, Chinese Academy of Sciences.
Declaration of Competing Interest
The authors declare no conflicts of interest.
References
-
Rohner E, Yang R, Foo KS, Goedel A, Chien KR. Unlocking the promise of mRNA therapeutics. Nat. Biotechnol. 2022, 40, 1586–1600. DOI:10.1038/s41587-022-01491-z [Google Scholar]
-
Chaudhary N, Weissman D, Whitehead KA. mRNA vaccines for infectious diseases: Principles, delivery and clinical translation. Nat. Rev. Drug Discov. 2021, 20, 817–838. DOI:10.1038/s41573-021-00283-5 [Google Scholar]
-
Grippin AJ, Marconi C, Copling S, Li N, Braun C, Woody C, et al. SARS-CoV-2 mRNA vaccines sensitize tumours to immune checkpoint blockade. Nature 2025, 647, 488–497. DOI:10.1038/s41586-025-09655-y [Google Scholar]
-
Sayour EJ, Boczkowski D, Mitchell DA, Nair SK. Cancer mRNA vaccines: Clinical advances and future opportunities. Nat. Rev. Clin. Oncol. 2024, 21, 489–500. DOI:10.1038/s41571-024-00902-1 [Google Scholar]
-
Parhiz H, Atochina-Vasserman EN, Weissman D. mRNA-based therapeutics: Looking beyond COVID-19 vaccines. Lancet 2024, 403, 1192–1204. DOI:10.1016/S0140-6736(23)02444-3 [Google Scholar]
-
Cullis PR, Felgner PL. The 60-year evolution of lipid nanoparticles for nucleic acid delivery. Nat. Rev. Drug Discov. 2024, 23, 709–722. DOI:10.1038/s41573-024-00977-6 [Google Scholar]
-
Dimitriadis GJ. Translation of rabbit globin mRNA introduced by liposomes into mouse lymphocytes. Nature 1978, 274, 923–924. DOI:10.1038/274923a0 [Google Scholar]
-
Wolff JA, Malone RW, Williams P, Chong W, Acsadi G, Jani A, et al. Direct gene transfer into mouse muscle in vivo. Science 1990, 247, 1465–1468. DOI:10.1126/science.1690918 [Google Scholar]
-
Shi Y, Shi M, Wang Y, You J. Progress and prospects of mRNA-based drugs in pre-clinical and clinical applications. Signal Transduct. Target. Ther. 2024, 9, 322. DOI:10.1038/s41392-024-02002-z [Google Scholar]
-
Eygeris Y, Gupta M, Kim J, Sahay G. Chemistry of lipid nanoparticles for RNA delivery. Acc. Chem. Res. 2022, 55, 2–12. DOI:10.1021/acs.accounts.1c00544 [Google Scholar]
-
Xiao Y, Tang Z, Huang X, Chen W, Zhou J, Liu H, et al. Emerging mRNA technologies: Delivery strategies and biomedical applications. Chem. Soc. Rev. 2022, 51, 3828–3845. DOI:10.1039/D1CS00617G [Google Scholar]
-
Joshi R, Sharma S, Kapoor DU, Prajapati BG, Huanbutta K, Sriamornsak P. mRNA-based therapeutics: Advances in drug delivery, comparative innovations, and biomedical applications. Mol. Pharm. 2026, 23, 583–621. DOI:10.1021/acs.molpharmaceut.5c00774 [Google Scholar]
-
Guasp P, Reiche C, Sethna Z, Balachandran VP. RNA vaccines for cancer: Principles to practice. Cancer Cell 2024, 42, 1163–1184. DOI:10.1016/j.ccell.2024.05.005 [Google Scholar]
-
Yaremenko AV, Khan MM, Zhen X, Tang Y, Tao W. Clinical advances of mRNA vaccines for cancer immunotherapy. Med 2025, 6, 100562. DOI:10.1016/j.medj.2024.11.015 [Google Scholar]
-
Le T, Sun C, Chang J, Zhang G, Yin X. mRNA vaccine development for emerging animal and zoonotic diseases. Viruses 2022, 14, 401. DOI:10.3390/v14020401 [Google Scholar]
-
Pardi N, Hogan MJ, Porter FW, Weissman D. mRNA vaccines—A new era in vaccinology. Nat. Rev. Drug Discov. 2018, 17, 261–279. DOI:10.1038/nrd.2017.243 [Google Scholar]
-
Jiang Z, Xu Y, Du G, Sun X. Emerging advances in delivery systems for mRNA cancer vaccines. J. Control. Release 2024, 370, 287–301. DOI:10.1016/j.jconrel.2024.04.039 [Google Scholar]
-
Sun X, Setrerrahmane S, Li C, Hu J, Xu H. Nucleic acid drugs: Recent progress and future perspectives. Signal Transduct. Target. Ther. 2024, 9, 316. DOI:10.1038/s41392-024-02035-4 [Google Scholar]
-
Karikó K, Buckstein M, Ni H, Weissman D. Suppression of RNA recognition by Toll-like receptors: The impact of nucleoside modification and the evolutionary origin of RNA. Immunity 2005, 23, 165–175. DOI:10.1016/j.immuni.2005.06.008 [Google Scholar]
-
Karikó K, Muramatsu H, Welsh FA, Ludwig J, Kato H, Akira S, et al. Incorporation of pseudouridine into mRNA yields superior nonimmunogenic vector with increased translational capacity and biological stability. Mol. Ther. 2008, 16, 1833–1840. DOI:10.1038/mt.2008.200 [Google Scholar]
-
Fang E, Liu X, Li M, Zhang Z, Song L, Zhu B, et al. Advances in COVID-19 mRNA vaccine development. Signal Transduct. Target. Ther. 2022, 7, 94. DOI:10.1038/s41392-022-00950-y [Google Scholar]
-
Heiser A, Coleman D, Dannull J, Yancey D, Maurice MA, Lallas CD, et al. Autologous dendritic cells transfected with prostate-specific antigen RNA stimulate CTL responses against metastatic prostate tumors. J. Clin. Investig. 2002, 109, 409–417. DOI:10.1172/JCI14364 [Google Scholar]
-
Eli G, David B, Smita KN. The quest for mRNA vaccines. Nucleic Acid Ther. 2022, 32, 449–456. DOI:10.1089/nat.2021.0103 [Google Scholar]
-
Blass E, Ott PA. Advances in the development of personalized neoantigen-based therapeutic cancer vaccines. Nat. Rev. Clin. Oncol. 2021, 18, 215–229. DOI:10.1038/s41571-020-00460-2 [Google Scholar]
-
Li M, Wang H, Tian L, Pang Z, Yang Q, Huang T, et al. COVID-19 vaccine development: Milestones, lessons and prospects. Signal Transduct. Target. Ther. 2022, 7, 146. DOI:10.1038/s41392-022-00996-y [Google Scholar]
-
Sun S, Liu L, Zhang J, Sun L, Shu W, Yang Z, et al. The role of neoantigens and tumor mutational burden in cancer immunotherapy: Advances, mechanisms, and perspectives. J. Hematol. Oncol. 2025, 18, 84. DOI:10.1186/s13045-025-01732-z [Google Scholar]
-
Garzia I, Nocchi L, Avalle L, Troise F, Leoni G, Seclì L, et al. Tumor burden dictates the neoantigen features required to generate an effective cancer vaccine. Cancer Immunol. Res. 2024, 12, 440–452. DOI:10.1158/2326-6066.CIR-23-0609 [Google Scholar]
-
Lichtenegger FS, Schnorfeil FM, Rothe M, Deiser K, Altmann T, Bücklein VL, et al. Toll-like receptor 7/8-matured RNA-transduced dendritic cells as post-remission therapy in acute myeloid leukaemia: Results of a phase I trial. Clin. Transl. Immunol. 2020, 9, e1117. DOI:10.1002/cti2.1117 [Google Scholar]
-
Lin C, Smith C, Rutka J. Current immunotherapeutic approaches to diffuse intrinsic pontine glioma. Front. Genet. 2024, 15, 1349612. DOI:10.3389/fgene.2024.1349612 [Google Scholar]
-
Kranz LM, Diken M, Haas H, Kreiter S, Loquai C, Reuter KC, et al. Systemic RNA delivery to dendritic cells exploits antiviral defence for cancer immunotherapy. Nature 2016, 534, 396–401. DOI:10.1038/nature18300 [Google Scholar]
-
Sahin U, Oehm P, Derhovanessian E, Jabulowsky RA, Vormehr M, Gold M, et al. An RNA vaccine drives immunity in checkpoint-inhibitor-treated melanoma. Nature 2020, 585, 107–112. DOI:10.1038/s41586-020-2537-9 [Google Scholar]
-
Miao L, Zhang Y, Huang L. mRNA vaccine for cancer immunotherapy. Mol. Cancer 2021, 20, 41. DOI:10.1186/s12943-021-01335-5 [Google Scholar]
-
Shi J, Wang J, Luo H, Zhao Q, Yao Z, Wu G, et al. Neoantigen-based T cell vaccines design strategies, therapeutic barriers, and clinical advances. Vaccine 2026, 83, 128659. DOI:10.1016/j.vaccine.2026.128659 [Google Scholar]
-
Sahin U, Derhovanessian E, Miller M, Kloke B-P, Simon P, Löwer M, et al. Personalized RNA mutanome vaccines mobilize poly-specific therapeutic immunity against cancer. Nature 2017, 547, 222–226. DOI:10.1038/nature23003 [Google Scholar]
-
Wei J, Hui A-M. The paradigm shift in treatment from COVID-19 to oncology with mRNA vaccines. Cancer Treat. Rev. 2022, 107, 102405. DOI:10.1016/j.ctrv.2022.102405 [Google Scholar]
-
Weber JS, Carlino MS, Khattak A, Meniawy T, Ansstas G, Taylor MH, et al. Individualised neoantigen therapy mRNA-4157 (V940) plus pembrolizumab versus pembrolizumab monotherapy in resected melanoma (KEYNOTE-942): A randomised, phase 2b study. Lancet 2024, 403, 632–644. DOI:10.1016/S0140-6736(23)02268-7 [Google Scholar]
-
Rojas LA, Sethna Z, Soares KC, Olcese C, Pang N, Patterson E, et al. Personalized RNA neoantigen vaccines stimulate T cells in pancreatic cancer. Nature 2023, 618, 144–150. DOI:10.1038/s41586-023-06063-y [Google Scholar]
-
Polack Fernando P, Thomas Stephen J, Kitchin N, Absalon J, Gurtman A, Lockhart S, et al. Safety and Efficacy of the BNT162b2 mRNA COVID-19 Vaccine. N. Engl. J. Med. 2020, 383, 2603–2615. DOI:10.1056/NEJMoa2034577 [Google Scholar]
-
Baden Lindsey R, El Sahly Hana M, Essink B, Kotloff K, Frey S, Novak R, et al. Efficacy and safety of the mRNA-1273 SARS-CoV-2 vaccine. N. Engl. J. Med. 2021, 384, 403–416. DOI:10.1056/NEJMoa2035389 [Google Scholar]
-
Krawczyk PS, Mazur M, Orzeł W, Gewartowska O, Jeleń S, Antczak W, et al. Re-adenylation by TENT5A enhances efficacy of SARS-CoV-2 mRNA vaccines. Nature 2025, 641, 984–992. DOI:10.1038/s41586-025-08842-1 [Google Scholar]
-
Soler S, Maser K, Zillinger T, Bartok E. To modify or not to modify—That is still the question for some mRNA applications. Mol. Ther. Nucleic Acids 2025, 36, 102655. DOI:10.1016/j.omtn.2025.102655 [Google Scholar]
-
Tiwari HK, Gogoi-Tiwari J, Robertson ID. Eliminating dog-mediated rabies: Challenges and strategies. Anim. Dis. 2021, 1, 19. DOI:10.1186/s44149-021-00023-7 [Google Scholar]
-
Alberer M, Gnad-Vogt U, Hong HS, Mehr KT, Backert L, Finak G, et al. Safety and immunogenicity of a mRNA rabies vaccine in healthy adults: An open-label, non-randomised, prospective, first-in-human phase 1 clinical trial. Lancet 2017, 390, 1511–1520. DOI:10.1016/S0140-6736(17)31665-3 [Google Scholar]
-
Kwon H, Kim M, Seo Y, Moon YS, Lee HJ, Lee K, et al. Emergence of synthetic mRNA: In vitro synthesis of mRNA and its applications in regenerative medicine. Biomaterials 2018, 156, 172–193. DOI:10.1016/j.biomaterials.2017.11.034 [Google Scholar]
-
Jahanafrooz Z, Baradaran B, Mosafer J, Hashemzaei M, Rezaei T, Mokhtarzadeh A, et al. Comparison of DNA and mRNA vaccines against cancer. Drug Discov. Today 2020, 25, 552–560. DOI:10.1016/j.drudis.2019.12.003 [Google Scholar]
-
Schmidt C, Schnierle BS. Self-amplifying RNA vaccine candidates: Alternative platforms for mRNA vaccine development. Pathogens 2023, 12, 138. DOI:10.3390/pathogens12010138 [Google Scholar]
-
Okechukwu Paul-Chima U, Michael Ben O, Fabian CO, Jovita Nnenna U, Chinyere NU. Self-amplifying RNA (saRNA) and circular RNA (circRNA) vaccines: Progress, evidence gaps, and translational pathways for durable and scalable immunization. Hum. Vaccines Immunother. 2026, 22, 2661120. DOI:10.1080/21645515.2026.2661120 [Google Scholar]
-
McGee JE, Kirsch JR, Kenney D, Cerbo F, Chavez EC, Shih T-Y, et al. Complete substitution with modified nucleotides in self-amplifying RNA suppresses the interferon response and increases potency. Nat. Biotechnol. 2025, 43, 720–726. DOI:10.1038/s41587-024-02306-z [Google Scholar]
-
Beissert T, Perkovic M, Vogel A, Erbar S, Walzer KC, Hempel T, et al. A Trans-amplifying RNA vaccine strategy for induction of potent protective immunity. Mol. Ther. 2020, 28, 119–128. DOI:10.1016/j.ymthe.2019.09.009 [Google Scholar]
-
Perkovic M, Gawletta S, Hempel T, Brill S, Nett E, Sahin U, et al. A trans-amplifying RNA simplified to essential elements is highly replicative and robustly immunogenic in mice. Mol. Ther. 2023, 31, 1636–1646. DOI:10.1016/j.ymthe.2023.01.019 [Google Scholar]
-
Xie J, Ye F, Deng X, Tang Y, Liang J-Y, Huang X, et al. Circular RNA: A promising new star of vaccine. J. Transl. Intern. Med. 2023, 11, 372–381. DOI:10.2478/jtim-2023-0122 [Google Scholar]
-
Liu C-X, Chen L-L. Circular RNAs: Characterization, cellular roles, and applications. Cell 2022, 185, 2016–2034. DOI:10.1016/j.cell.2022.04.021 [Google Scholar]
-
An L, Li S, Zhang K. Structural insights and engineering of the T4 td intron for improved RNA circularization. Nat. Catal. 2025, 8, 1281–1294. DOI:10.1038/s41929-025-01445-z [Google Scholar]
-
Huang Y, Chen Y-Q, Lou S-Y, Gao X, Liu Y-X, Zhang Y-L, et al. IRES–cargo interplay structurally modulates circular RNA translation. Cell Res. 2026, 36, 377–380. DOI:10.1038/s41422-026-01233-9 [Google Scholar]
-
Rokade S, Damani AM, Oft M, Emmerich J. IL-2 based cancer immunotherapies: An evolving paradigm. Front. Immunol. 2024, 15, 1433989. DOI:10.3389/fimmu.2024.1433989 [Google Scholar]
-
Kim C, Lee Y, Lee H, Kim B-S. Advances in mRNA-lipid nanoparticle engineering for immune cell targeting and immune modulation. Small Methods 2025, 9, e01401. DOI:10.1002/smtd.202501401 [Google Scholar]
-
Beck JD, Diken M, Suchan M, Streuber M, Diken E, Kolb L, et al. Long-lasting mRNA-encoded interleukin-2 restores CD8+ T cell neoantigen immunity in MHC class I-deficient cancers. Cancer Cell 2024, 42, 568–582.e511. DOI:10.1016/j.ccell.2024.02.013 [Google Scholar]
-
Lai I, Swaminathan S, Baylot V, Mosley A, Dhanasekaran R, Gabay M, et al. Lipid nanoparticles that deliver IL-12 messenger RNA suppress tumorigenesis in MYC oncogene-driven hepatocellular carcinoma. J. ImmunoTherapy Cancer 2018, 6, 125. DOI:10.1186/s40425-018-0431-x [Google Scholar]
-
Hewitt SL, Bailey D, Zielinski J, Apte A, Musenge F, Karp R, et al. Intratumoral IL12 mRNA therapy promotes TH1 transformation of the tumor microenvironment. Clin. Cancer Res. 2020, 26, 6284–6298. DOI:10.1158/1078-0432.CCR-20-0472 [Google Scholar]
-
Hewitt SL, Bai A, Bailey D, Ichikawa K, Zielinski J, Karp R, et al. Durable anticancer immunity from intratumoral administration of IL-23, IL-36γ, and OX40L mRNAs. Sci. Transl. Med. 2019, 11, eaat9143. DOI:10.1126/scitranslmed.aat9143 [Google Scholar]
-
Jansen Y, Kruse V, Corthals J, Schats K, van Dam P-J, Seremet T, et al. A randomized controlled phase II clinical trial on mRNA electroporated autologous monocyte-derived dendritic cells (TriMixDC-MEL) as adjuvant treatment for stage III/IV melanoma patients who are disease-free following the resection of macrometastases. Cancer Immunol. Immunother. 2020, 69, 2589–2598. DOI:10.1007/s00262-020-02618-4 [Google Scholar]
-
Stadler CR, Bähr-Mahmud H, Celik L, Hebich B, Roth AS, Roth RP, et al. Elimination of large tumors in mice by mRNA-encoded bispecific antibodies. Nat. Med. 2017, 23, 815–817. DOI:10.1038/nm.4356 [Google Scholar]
-
Rybakova Y, Kowalski PS, Huang Y, Gonzalez JT, Heartlein MW, DeRosa F, et al. mRNA delivery for therapeutic anti-HER2 antibody expression in vivo. Mol. Ther. 2019, 27, 1415–1423. DOI:10.1016/j.ymthe.2019.05.012 [Google Scholar]
-
Wu L, Wang W, Tian J, Qi C, Cai Z, Yan W, et al. Intravenous delivery of RNA encoding anti-PD-1 human monoclonal antibody for treating intestinal cancer. J. Cancer 2022, 13, 579–588. DOI:10.7150/jca.63991 [Google Scholar]
-
Huang C, Duan X, Wang J, Tian Q, Ren Y, Chen K, et al. Lipid nanoparticle delivery system for mRNA encoding B7H3-redirected bispecific antibody displays potent antitumor effects on malignant tumors. Adv. Sci. 2023, 10, 2205532. DOI:10.1002/advs.202205532 [Google Scholar]
-
Lee Y-R, Chen M, Pandolfi PP. The functions and regulation of the PTEN tumour suppressor: New modes and prospects. Nat. Rev. Mol. Cell Biol. 2018, 19, 547–562. DOI:10.1038/s41580-018-0015-0 [Google Scholar]
-
Islam MA, Xu Y, Tao W, Ubellacker JM, Lim M, Aum D, et al. Restoration of tumour-growth suppression in vivo via systemic nanoparticle-mediated delivery of PTEN mRNA. Nat. Biomed. Eng. 2018, 2, 850–864. DOI:10.1038/s41551-018-0284-0 [Google Scholar]
-
Lin Y-X, Wang Y, Ding J, Jiang A, Wang J, Yu M, et al. Reactivation of the tumor suppressor PTEN by mRNA nanoparticles enhances antitumor immunity in preclinical models. Sci. Transl. Med. 2021, 13, eaba9772. DOI:10.1126/scitranslmed.aba9772 [Google Scholar]
-
Kong N, Tao W, Ling X, Wang J, Xiao Y, Shi S, et al. Synthetic mRNA nanoparticle-mediated restoration of p53 tumor suppressor sensitizes p53-deficient cancers to mTOR inhibition. Sci. Transl. Med. 2019, 11, eaaw1565. DOI:10.1126/scitranslmed.aaw1565 [Google Scholar]
-
Zhou H, Liao Y, Han X, Chen DS, Hong X, Zhou K, et al. ROS-responsive nanoparticle delivery of mRNA and photosensitizer for combinatorial cancer therapy. Nano Lett. 2023, 23, 3661–3668. DOI:10.1021/acs.nanolett.2c03784 [Google Scholar]
-
Taylor PC, Adams AC, Hufford MM, de la Torre I, Winthrop K, Gottlieb RL. Neutralizing monoclonal antibodies for treatment of COVID-19. Nat. Rev. Immunol. 2021, 21, 382–393. DOI:10.1038/s41577-021-00542-x [Google Scholar]
-
Pinto D, Park Y-J, Beltramello M, Walls AC, Tortorici MA, Bianchi S, et al. Cross-neutralization of SARS-CoV-2 by a human monoclonal SARS-CoV antibody. Nature 2020, 583, 290–295. DOI:10.1038/s41586-020-2349-y [Google Scholar]
-
Tiwari PM, Vanover D, Lindsay KE, Bawage SS, Kirschman JL, Bhosle S, et al. Engineered mRNA-expressed antibodies prevent respiratory syncytial virus infection. Nat. Commun. 2018, 9, 3999. DOI:10.1038/s41467-018-06508-3 [Google Scholar]
-
Kose N, Fox JM, Sapparapu G, Bombardi R, Tennekoon RN, de Silva AD, et al. A lipid-encapsulated mRNA encoding a potently neutralizing human monoclonal antibody protects against chikungunya infection. Sci. Immunol. 2019, 4, eaaw6647. DOI:10.1126/sciimmunol.aaw6647 [Google Scholar]
-
Erasmus JH, Archer J, Fuerte-Stone J, Khandhar AP, Voigt E, Granger B, et al. Intramuscular delivery of replicon RNA encoding ZIKV-117 human monoclonal antibody protects against Zika Virus infection. Mol. Ther. —Methods Clin. Dev. 2020, 18, 402–414. DOI:10.1016/j.omtm.2020.06.011 [Google Scholar]
-
Song Y, Li J, Wu Y. Evolving understanding of autoimmune mechanisms and new therapeutic strategies of autoimmune disorders. Signal Transduct. Target. Ther. 2024, 9, 263. DOI:10.1038/s41392-024-01952-8 [Google Scholar]
-
Berry CT, Frazee CS, Herman PJ, Chen S, Chen A, Kuo Y, et al. Current advancements in cellular immunotherapy for autoimmune disease. Semin. Immunopathol. 2025, 47, 7. DOI:10.1007/s00281-024-01034-5 [Google Scholar]
-
Savguira M, Chen DXW, Dong S, Li B. RNA immunotherapy: Revolutionizing cancer and autoimmune disease treatments. Trends Mol. Med. 2026, 32, 181–196. DOI:10.1016/j.molmed.2025.06.008 [Google Scholar]
-
Zhou H, Wei D, Chen Z, Chen H, Dong C, Yao W, et al. The mRNA-based innovative strategy: Progress and challenges. Nano-Micro Lett. 2026, 18, 118. DOI:10.1007/s40820-025-01906-x [Google Scholar]
-
Baek R, Coughlan K, Jiang L, Liang M, Ci L, Singh H, et al. Characterizing the mechanism of action for mRNA therapeutics for the treatment of propionic acidemia, methylmalonic acidemia, and phenylketonuria. Nat. Commun. 2024, 15, 3804. DOI:10.1038/s41467-024-47460-9 [Google Scholar]
-
Koeberl D, Schulze A, Sondheimer N, Lipshutz GS, Geberhiwot T, Li L, et al. Interim analyses of a first-in-human phase 1/2 mRNA trial for propionic acidaemia. Nature 2024, 628, 872–877. DOI:10.1038/s41586-024-07266-7 [Google Scholar]
-
Perez-Garcia CG, Diaz-Trelles R, Vega JB, Bao Y, Sablad M, Limphong P, et al. Development of an mRNA replacement therapy for phenylketonuria. Mol. Ther. Nucleic Acids 2022, 28, 87–98. DOI:10.1016/j.omtn.2022.02.020 [Google Scholar]
-
McNutt M, Vockley J, Zori R, Basel D, Breilyn M, Longo N, et al. IT translates: An update on the ARCT-810 mRNA therapy for OTC deficiency. Mol. Genet. Metab. 2024, 141, 108161. DOI:10.1016/j.ymgme.2024.108161 [Google Scholar]
-
Zhou Z, Chen W, Yu H, Tabas I, Foo RSY, Tao W. mRNA medicine for cardiovascular disease. Nat. Cardiovasc. Res. 2026, 5, 291–307. DOI:10.1038/s44161-026-00804-8 [Google Scholar]
-
Wang R, Zhang R, Zhou J, Ran J. Crosstalk between anti-angiogenic and pro-angiogenic pathways in disease: Mechanisms and therapeutic strategies. Pharmacol. Ther. 2025, 276, 108934. DOI:10.1016/j.pharmthera.2025.108934 [Google Scholar]
-
Gan L-M, Lagerström-Fermér M, Carlsson LG, Arfvidsson C, Egnell A-C, Rudvik A, et al. Intradermal delivery of modified mRNA encoding VEGF-A in patients with type 2 diabetes. Nat. Commun. 2019, 10, 871. DOI:10.1038/s41467-019-08852-4 [Google Scholar]
-
Anttila V, Saraste A, Knuuti J, Hedman M, Jaakkola P, Laugwitz K-L, et al. Direct intramyocardial injection of VEGF mRNA in patients undergoing coronary artery bypass grafting. Mol. Ther. 2023, 31, 866–874. DOI:10.1016/j.ymthe.2022.11.017 [Google Scholar]
-
Singh RN, Horn MM, Juko M, Kampshoff A, Schmid J, Omran H, et al. Restoration of defective CFTR in human nasal respiratory epithelial cells by CFTR modulators and mRNA transfection. Int. J. Mol. Sci. 2026, 27, 2063. DOI:10.3390/ijms27042063 [Google Scholar]
-
Robinson E, MacDonald KD, Slaughter K, McKinney M, Patel S, Sun C, et al. Lipid nanoparticle-delivered chemically modified mRNA restores chloride secretion in cystic fibrosis. Mol. Ther. 2018, 26, 2034–2046. DOI:10.1016/j.ymthe.2018.05.014 [Google Scholar]
-
Rowe SM, Zuckerman JB, Dorgan D, Lascano J, McCoy K, Jain M, et al. Inhaled mRNA therapy for treatment of cystic fibrosis: Interim results of a randomized, double-blind, placebo-controlled phase 1/2 clinical study. J. Cyst. Fibros. 2023, 22, 656–664. DOI:10.1016/j.jcf.2023.04.008 [Google Scholar]
-
Makarova KS, Shmakov SA, Wolf YI, Mutz P, Altae-Tran H, Beisel CL, et al. An updated evolutionary classification of CRISPR–Cas systems including rare variants. Nat. Microbiol. 2025, 10, 3346–3361. DOI:10.1038/s41564-025-02180-8 [Google Scholar]
-
Jinek M, Chylinski K, Fonfara I, Hauer M, Doudna JA, Charpentier E. A programmable dual-RNA–guided DNA endonuclease in adaptive bacterial immunity. Science 2012, 337, 816–821. DOI:10.1126/science.1225829 [Google Scholar]
-
Fu Y, Sander JD, Reyon D, Cascio VM, Joung JK. Improving CRISPR-Cas nuclease specificity using truncated guide RNAs. Nat. Biotechnol. 2014, 32, 279–284. DOI:10.1038/nbt.2808 [Google Scholar]
-
Rozners E. Chemical modifications of CRISPR RNAs to improve gene-editing activity and specificity. J. Am. Chem. Soc. 2022, 144, 12584–12594. DOI:10.1021/jacs.2c02633 [Google Scholar]
-
Rahdar M, McMahon MA, Prakash TP, Swayze EE, Bennett CF, Cleveland DW. Synthetic CRISPR RNA-Cas9–guided genome editing in human cells. Proc. Natl. Acad. Sci. 2015, 112, E7110–E7117. DOI:10.1073/pnas.1520883112 [Google Scholar]
-
Barber HM, Pater AA, Gagnon KT, Damha MJ, O’Reilly D. Chemical engineering of CRISPR–Cas systems for therapeutic application. Nat. Rev. Drug Discov. 2025, 24, 209–230. DOI:10.1038/s41573-024-01086-0 [Google Scholar]
-
Yin H, Song C-Q, Suresh S, Wu Q, Walsh S, Rhym LH, et al. Structure-guided chemical modification of guide RNA enables potent non-viral in vivo genome editing. Nat. Biotechnol. 2017, 35, 1179–1187. DOI:10.1038/nbt.4005 [Google Scholar]
-
Wang H-X, Li M, Lee CM, Chakraborty S, Kim H-W, Bao G, et al. CRISPR/Cas9-based genome editing for disease modeling and therapy: Challenges and opportunities for nonviral delivery. Chem. Rev. 2017, 117, 9874–9906. DOI:10.1021/acs.chemrev.6b00799 [Google Scholar]
-
Li W, Wang C, Lu Y. When mRNA meets gene editing. Nano Res. 2024, 17, 7337–7356. DOI:10.1007/s12274-024-6729-8 [Google Scholar]
-
Rosenblum D, Gutkin A, Kedmi R, Ramishetti S, Veiga N, Jacobi AM, et al. CRISPR-Cas9 genome editing using targeted lipid nanoparticles for cancer therapy. Sci. Adv. 2020, 6, eabc9450. DOI:10.1126/sciadv.abc9450 [Google Scholar]
-
Kim M, Song ES, Chen JC, Chatterjee S, Sun Y, Lee SM, et al. Dual SORT LNPs for multi-organ base editing. Nat. Biotechnol. 2026, 44, 578–586. DOI:10.1038/s41587-025-02675-z [Google Scholar]
-
Farbiak L, Cheng Q, Wei T, Álvarez-Benedicto E, Johnson LT, Lee S, et al. All-in-one dendrimer-based lipid Nanoparticles enable precise HDR-mediated gene editing in vivo. Adv. Mater. 2021, 33, 2006619. DOI:10.1002/adma.202006619 [Google Scholar]
-
Xu L, Yang H, Gao Y, Chen Z, Xie L, Liu Y, et al. CRISPR/Cas9-mediated CCR5 ablation in human hematopoietic stem/progenitor cells confers HIV-1 resistance in vivo. Mol. Ther. 2017, 25, 1782–1789. DOI:10.1016/j.ymthe.2017.04.027 [Google Scholar]
-
Xu L, Wang J, Liu Y, Xie L, Su B, Mou D, et al. CRISPR-edited stem cells in a patient with HIV and acute lymphocytic leukemia. N. Engl. J. Med. 2019, 381, 1240–1247. DOI:10.1056/NEJMoa1817426 [Google Scholar]
-
Mancuso P, Chen C, Kaminski R, Gordon J, Liao S, Robinson JA, et al. CRISPR based editing of SIV proviral DNA in ART treated non-human primates. Nat. Commun. 2020, 11, 6065. DOI:10.1038/s41467-020-19821-7 [Google Scholar]
-
Roth TL, Puig-Saus C, Yu R, Shifrut E, Carnevale J, Li PJ, et al. Reprogramming human T cell function and specificity with non-viral genome targeting. Nature 2018, 559, 405–409. DOI:10.1038/s41586-018-0326-5 [Google Scholar]
-
Gillmore Julian D, Gane E, Taubel J, Kao J, Fontana M, Maitland Michael L, et al. CRISPR-Cas9 in vivo gene editing for transthyretin amyloidosis. N. Engl. J. Med. 2021, 385, 493–502. DOI:10.1056/NEJMoa2107454 [Google Scholar]
-
Cohn Danny M, Gurugama P, Magerl M, Katelaris Constance H, Launay D, Bouillet L, et al. CRISPR-based therapy for hereditary angioedema. N. Engl. J. Med. 2025, 392, 458–467. DOI:10.1056/NEJMoa2405734 [Google Scholar]
-
Han JP, Kim M, Choi BS, Lee JH, Lee GS, Jeong M, et al. In vivo delivery of CRISPR-Cas9 using lipid nanoparticles enables antithrombin gene editing for sustainable hemophilia A and B therapy. Sci. Adv. 2022, 8, eabj6901. DOI:10.1126/sciadv.abj6901 [Google Scholar]
-
Qi C, Fan D, Wang L, Guo L, Jiang H, Wang L. Mechanisms of action and therapeutic potential of PCSK9-regulating drugs. Pharm. Biol. 2025, 63, 428–446. DOI:10.1080/13880209.2025.2514021 [Google Scholar]
-
Musunuru K, Chadwick AC, Mizoguchi T, Garcia SP, DeNizio JE, Reiss CW, et al. In vivo CRISPR base editing of PCSK9 durably lowers cholesterol in primates. Nature 2021, 593, 429–434. DOI:10.1038/s41586-021-03534-y [Google Scholar]
-
Laffin Luke J, Nicholls Stephen J, Scott Russell S, Clifton Peter M, Baker J, Sarraju A, et al. Phase 1 trial of CRISPR-Cas9 gene editing targeting ANGPTL3. N. Engl. J. Med. 2025, 393, 2119–2130. DOI:10.1056/NEJMoa2511778 [Google Scholar]
-
Aghajanian H, Kimura T, Rurik JG, Hancock AS, Leibowitz MS, Li L, et al. Targeting cardiac fibrosis with engineered T cells. Nature 2019, 573, 430–433. DOI:10.1038/s41586-019-1546-z [Google Scholar]
-
Rurik JG, Tombácz I, Yadegari A, Méndez Fernández PO, Shewale SV, Li L, et al. CAR T cells produced in vivo to treat cardiac injury. Science 2022, 375, 91–96. DOI:10.1126/science.abm0594 [Google Scholar]
-
Hou X, Zaks T, Langer R, Dong Y. Lipid nanoparticles for mRNA delivery. Nat. Rev. Mater. 2021, 6, 1078–1094. DOI:10.1038/s41578-021-00358-0 [Google Scholar]
-
Kim J, Jozic A, Lin Y, Eygeris Y, Bloom E, Tan X, et al. Engineering Lipid Nanoparticles for Enhanced Intracellular Delivery of mRNA through Inhalation. ACS Nano 2022, 16, 14792–14806. DOI:10.1021/acsnano.2c05647 [Google Scholar]
-
Lokugamage MP, Vanover D, Beyersdorf J, Hatit MZC, Rotolo L, Echeverri ES, et al. Optimization of lipid nanoparticles for the delivery of nebulized therapeutic mRNA to the lungs. Nat. Biomed. Eng. 2021, 5, 1059–1068. DOI:10.1038/s41551-021-00786-x [Google Scholar]
-
Liu S, Wen Y, Shan X, Ma X, Yang C, Cheng X, et al. Charge-assisted stabilization of lipid nanoparticles enables inhaled mRNA delivery for mucosal vaccination. Nat. Commun. 2024, 15, 9471. DOI:10.1038/s41467-024-53914-x [Google Scholar]
-
Jiang AY, Lathwal S, Meng S, Witten J, Beyer E, McMullen P, et al. Zwitterionic Polymer-Functionalized Lipid Nanoparticles for the Nebulized Delivery of mRNA. J. Am. Chem. Soc. 2024, 146, 32567–32574. DOI:10.1021/jacs.4c11347 [Google Scholar]
-
Lei J, Yang K, Cao W, Qi S, Du X, Li H, et al. Pancreatic-targeted lipid nanoparticles based on organ capsule filtration. Nature 2026, 652, 220–229. DOI:10.1038/s41586-026-10158-7 [Google Scholar]
-
Qiu X, Yang Y, Ma Q, Zheng B, Chen Z, Wu F, et al. Thioketal-Incorporated Biodegradable Lipid Nanoparticles Deliver mRNA to Ductal Epithelial Cells for Improved Pancreatic Cancer Treatment. J. Am. Chem. Soc. 2025, 147, 44605–44616. DOI:10.1021/jacs.5c19387 [Google Scholar]
-
Youn K, Oh S, Gil H, Choi Y, Keum G, Bang E-K. Delivery strategies of messenger RNA therapeutics for brain disorders. Bull. Korean Chem. Soc. 2025, 46, 1186–1204. DOI:10.1002/bkcs.70083 [Google Scholar]
-
Yu X, Deng X-M, Lin Y, Ren H, Jia L, Meng Y, et al. Nose-to-Brain Delivery of mRNA-Loaded Lipid Nanoparticles Bypasses the Blood–Brain Barrier for Effective Brain Disease Therapy. ACS Nano 2026, 20, 15589–15605. DOI:10.1021/acsnano.6c04580 [Google Scholar]
-
García-González N, Gonçalves-Sánchez J, Gómez-Nieto R, Gonçalves-Estella JM, López DE. Advances and Challenges in Gene Therapy for Neurodegenerative Diseases: A Systematic Review. Int. J. Mol. Sci. 2024, 25, 12485. DOI:10.3390/ijms252312485 [Google Scholar]
-
Xue Y, Wang C, Li H, Du S, Zhong Y, Zhang Y, et al. Lipid Nanoparticles Enhance mRNA Delivery to the Central Nervous System Upon Intrathecal Injection. Adv. Mater. 2025, 37, 2417097. DOI:10.1002/adma.202417097 [Google Scholar]
-
Han EL, Tang S, Kim D, Murray AM, Swingle KL, Hamilton AG, et al. Peptide-Functionalized Lipid Nanoparticles for Targeted Systemic mRNA Delivery to the Brain. Nano Lett. 2024, 25, 800–810. DOI:10.1021/acs.nanolett.4c05186 [Google Scholar]
-
Geisler HC, Ghalsasi AA, Safford HC, Swingle KL, Thatte AS, Mukalel AJ, et al. EGFR-targeted ionizable lipid nanoparticles enhance in vivo mRNA delivery to the placenta. J. Control. Release 2024, 371, 455–469. DOI:10.1016/j.jconrel.2024.05.036 [Google Scholar]
-
Chen MZ, Yuen D, McLeod VM, Yong KW, Smyth CH, Herling BR, et al. A versatile antibody capture system drives specific in vivo delivery of mRNA-loaded lipid nanoparticles. Nat. Nanotechnol. 2025, 20, 1273–1284. DOI:10.1038/s41565-025-01954-9 [Google Scholar]
-
Shah S, Ranasinghe M, Decker J, Fraser K, Wang Y, Kinlaw S, et al. Lipid nanoparticles with aptamers enable targeted mRNA delivery to CD4⁺ T cells. Drug Deliv. 2026, 33, 2637266. DOI:10.1080/10717544.2026.2637266 [Google Scholar]
-
Li J, Yu J, Song J, Zhang Y, Li N, Wang Z, et al. Galloylated liposomes enable targeted drug delivery by overcoming protein corona shielding. Nat. Commun. 2025, 16, 7926. DOI:10.1038/s41467-025-63198-4 [Google Scholar]
-
Wang Z, Zhang J, Wang Y, Zhou J, Jiao X, Han M, et al. Overcoming Endosomal Escape Barriers in Gene Drug Delivery Using De Novo Designed pH-Responsive Peptides. ACS Nano 2024, 18, 10324–10340. DOI:10.1021/acsnano.4c02400 [Google Scholar]
-
Deng X, Li Y, Zhu X, Du Y, Chi H, Cheng M, et al. pH-Isomerizable Acylhydrazone-Based Ionizable Lipids for Spleen-Targeted mRNA Vaccines. J. Am. Chem. Soc. 2025, 147, 47428–47442. DOI:10.1021/jacs.5c16121 [Google Scholar]
-
Chen Z, Yang Y, Qiu X, Zhou H, Wang R, Xiong H. Crown-like Biodegradable Lipids Enable Lung-Selective mRNA Delivery and Dual-Modal Tumor Imaging In Vivo. J. Am. Chem. Soc. 2024, 146, 34209–34220. DOI:10.1021/jacs.4c14500 [Google Scholar]
-
Cheng Q, Wei T, Farbiak L, Johnson LT, Dilliard SA, Siegwart DJ. Selective organ targeting (SORT) nanoparticles for tissue-specific mRNA delivery and CRISPR–Cas gene editing. Nat. Nanotechnol. 2020, 15, 313–320. DOI:10.1038/s41565-020-0669-6 [Google Scholar]
-
Dilliard SA, Cheng Q, Siegwart DJ. On the mechanism of tissue-specific mRNA delivery by selective organ targeting nanoparticles. Proc. Natl. Acad. Sci. USA 2021, 118, e2109256118. DOI:10.1073/pnas.2109256118 [Google Scholar]
-
Wang X, Tian Z, Pacheco Benitez A, Bian X, Vaidya A, Guerrero E, et al. Tunable polymers for polymer–lipid hybrid nanoparticles facilitate controlled organ-selective RNA delivery. Nat. Chem. Eng. 2026. DOI:10.1038/s44286-026-00425-9 [Google Scholar]
-
Nie X, Liu Y, Song Y, Yao X, Chen Y, Lee H-Y, et al. In vivo generation of CAR myeloid cells through erythrocyte-mediated mRNA delivery for cancer immunotherapy. Sci. Transl. Med. 2025, 18, eady6730. DOI:10.1126/scitranslmed.ady6730 [Google Scholar]
-
Huang X, Liu C, Sharma SN, You X, Chen S, Li Y, et al. Oral delivery of liquid mRNA therapeutics by an engineered capsule for treatment of preclinical intestinal disease. Sci. Transl. Med. 2025, 17, eadu1493. DOI:10.1126/scitranslmed.adu1493 [Google Scholar]
-
Zhao H, Xu J, Gao X, Zhu J, He Z. Artificial intelligence in the rational design of lipid nanoparticles for mRNA therapeutics. Innov. Drug Discov. 2026, 1, 100006. DOI:10.59717/j.xinn-drugdisc.2026.100006 [Google Scholar]
-
Su K, Qiu J, Xu T, Liu S. Artificial intelligence-guided design of lipid nanoparticles for mRNA delivery. Acta Pharm. Sin. B 2026, 16, 709–727. DOI:10.1016/j.apsb.2025.11.029 [Google Scholar]
-
Yang B, Liu J, Li Y, Liu X. mRNA Cancer Vaccines: From Pandemic Paradigm to Personalized Oncology Therapeutics. Cancer Innov. 2025, 4, e70041. DOI:10.1002/cai2.70041 [Google Scholar]
-
Que J, Xue G, Wang T, Jin X, Wang Z, Cai Y, et al. Identifying T cell antigen at the atomic level with graph convolutional network. Nat. Commun. 2025, 16, 5171. DOI:10.1038/s41467-025-60461-6 [Google Scholar]
-
Zhao Y, Yu J, Su Y, Shu Y, Ma E, Wang J, et al. A unified deep framework for peptide–major histocompatibility complex–T cell receptor binding prediction. Nat. Mach. Intell. 2025, 7, 650–660. DOI:10.1038/s42256-025-01002-0 [Google Scholar]
-
Xiong Y, Wang A, Kang Y, Shen C, Hsieh C-Y, Hou T. mRNABERT: Advancing mRNA sequence design with a universal language model and comprehensive dataset. Nat. Commun. 2025, 16, 10371. DOI:10.1038/s41467-025-65340-8 [Google Scholar]
-
Rajbanshi B, Guruacharya A. codonGPT: Reinforcement learning on a generative language model enables scalable mRNA design. Nucleic Acids Res. 2025, 53, gkaf1345. DOI:10.1093/nar/gkaf1345 [Google Scholar]
-
Zhang H, Liu H, Xu Y, Huang H, Liu Y, Wang J, et al. Deep generative models design mRNA sequences with enhanced translational capacity and stability. Science 2025, 390, eadr8470. DOI:10.1126/science.adr8470 [Google Scholar]
-
Zeng J, Chen R, He S, Zhang C, Liu W-C, Song H, et al. High-throughput, AI-assisted design and optimization of lipid nanoparticles for drug delivery. J. Control. Release 2026, 391, 114573. DOI:10.1016/j.jconrel.2025.114573 [Google Scholar]
-
Witten J, Raji I, Manan RS, Beyer E, Bartlett S, Tang Y, et al. Artificial intelligence-guided design of lipid nanoparticles for pulmonary gene therapy. Nat. Biotechnol. 2025, 43, 1790–1799. DOI:10.1038/s41587-024-02490-y. [Google Scholar]
-
Xu Y, Ma S, Cui H, Chen J, Xu S, Gong F, et al. AGILE platform: A deep learning powered approach to accelerate LNP development for mRNA delivery. Nat. Commun. 2024, 15, 6305. DOI:10.1038/s41467-024-50619-z [Google Scholar]
-
Xu Y, Cui H, Pang K, Li G, Gong F, Dong S, et al. LUMI-lab: A foundation model-driven autonomous platform enabling discovery of ionizable lipid designs for mRNA delivery. Cell 2026, 189, 1620–1635.e1625. DOI:10.1016/j.cell.2026.01.012 [Google Scholar]
-
Longhurst Hilary J, Lindsay K, Petersen Remy S, Fijen Lauré M, Gurugama P, Maag D, et al. CRISPR-Cas9 in vivo gene editing of KLKB1 for hereditary angioedema. N. Engl. J. Med. 2024, 390, 432–441. DOI:10.1056/NEJMoa2309149 [Google Scholar]
-
Howard JF. Descartes-08: Unlocking the potential of mRNA CAR T-cell therapy in myasthenia gravis. Mol. Ther. 2026, 34, 2561–2563. DOI:10.1016/j.ymthe.2026.04.008 [Google Scholar]
-
de Picciotto S, DeVita N, Hsiao CJ, Honan C, Tse S-W, Nguyen M, et al. Selective activation and expansion of regulatory T cells using lipid encapsulated mRNA encoding a long-acting IL-2 mutein. Nat. Commun. 2022, 13, 3866. DOI:10.1038/s41467-022-31130-9 [Google Scholar]