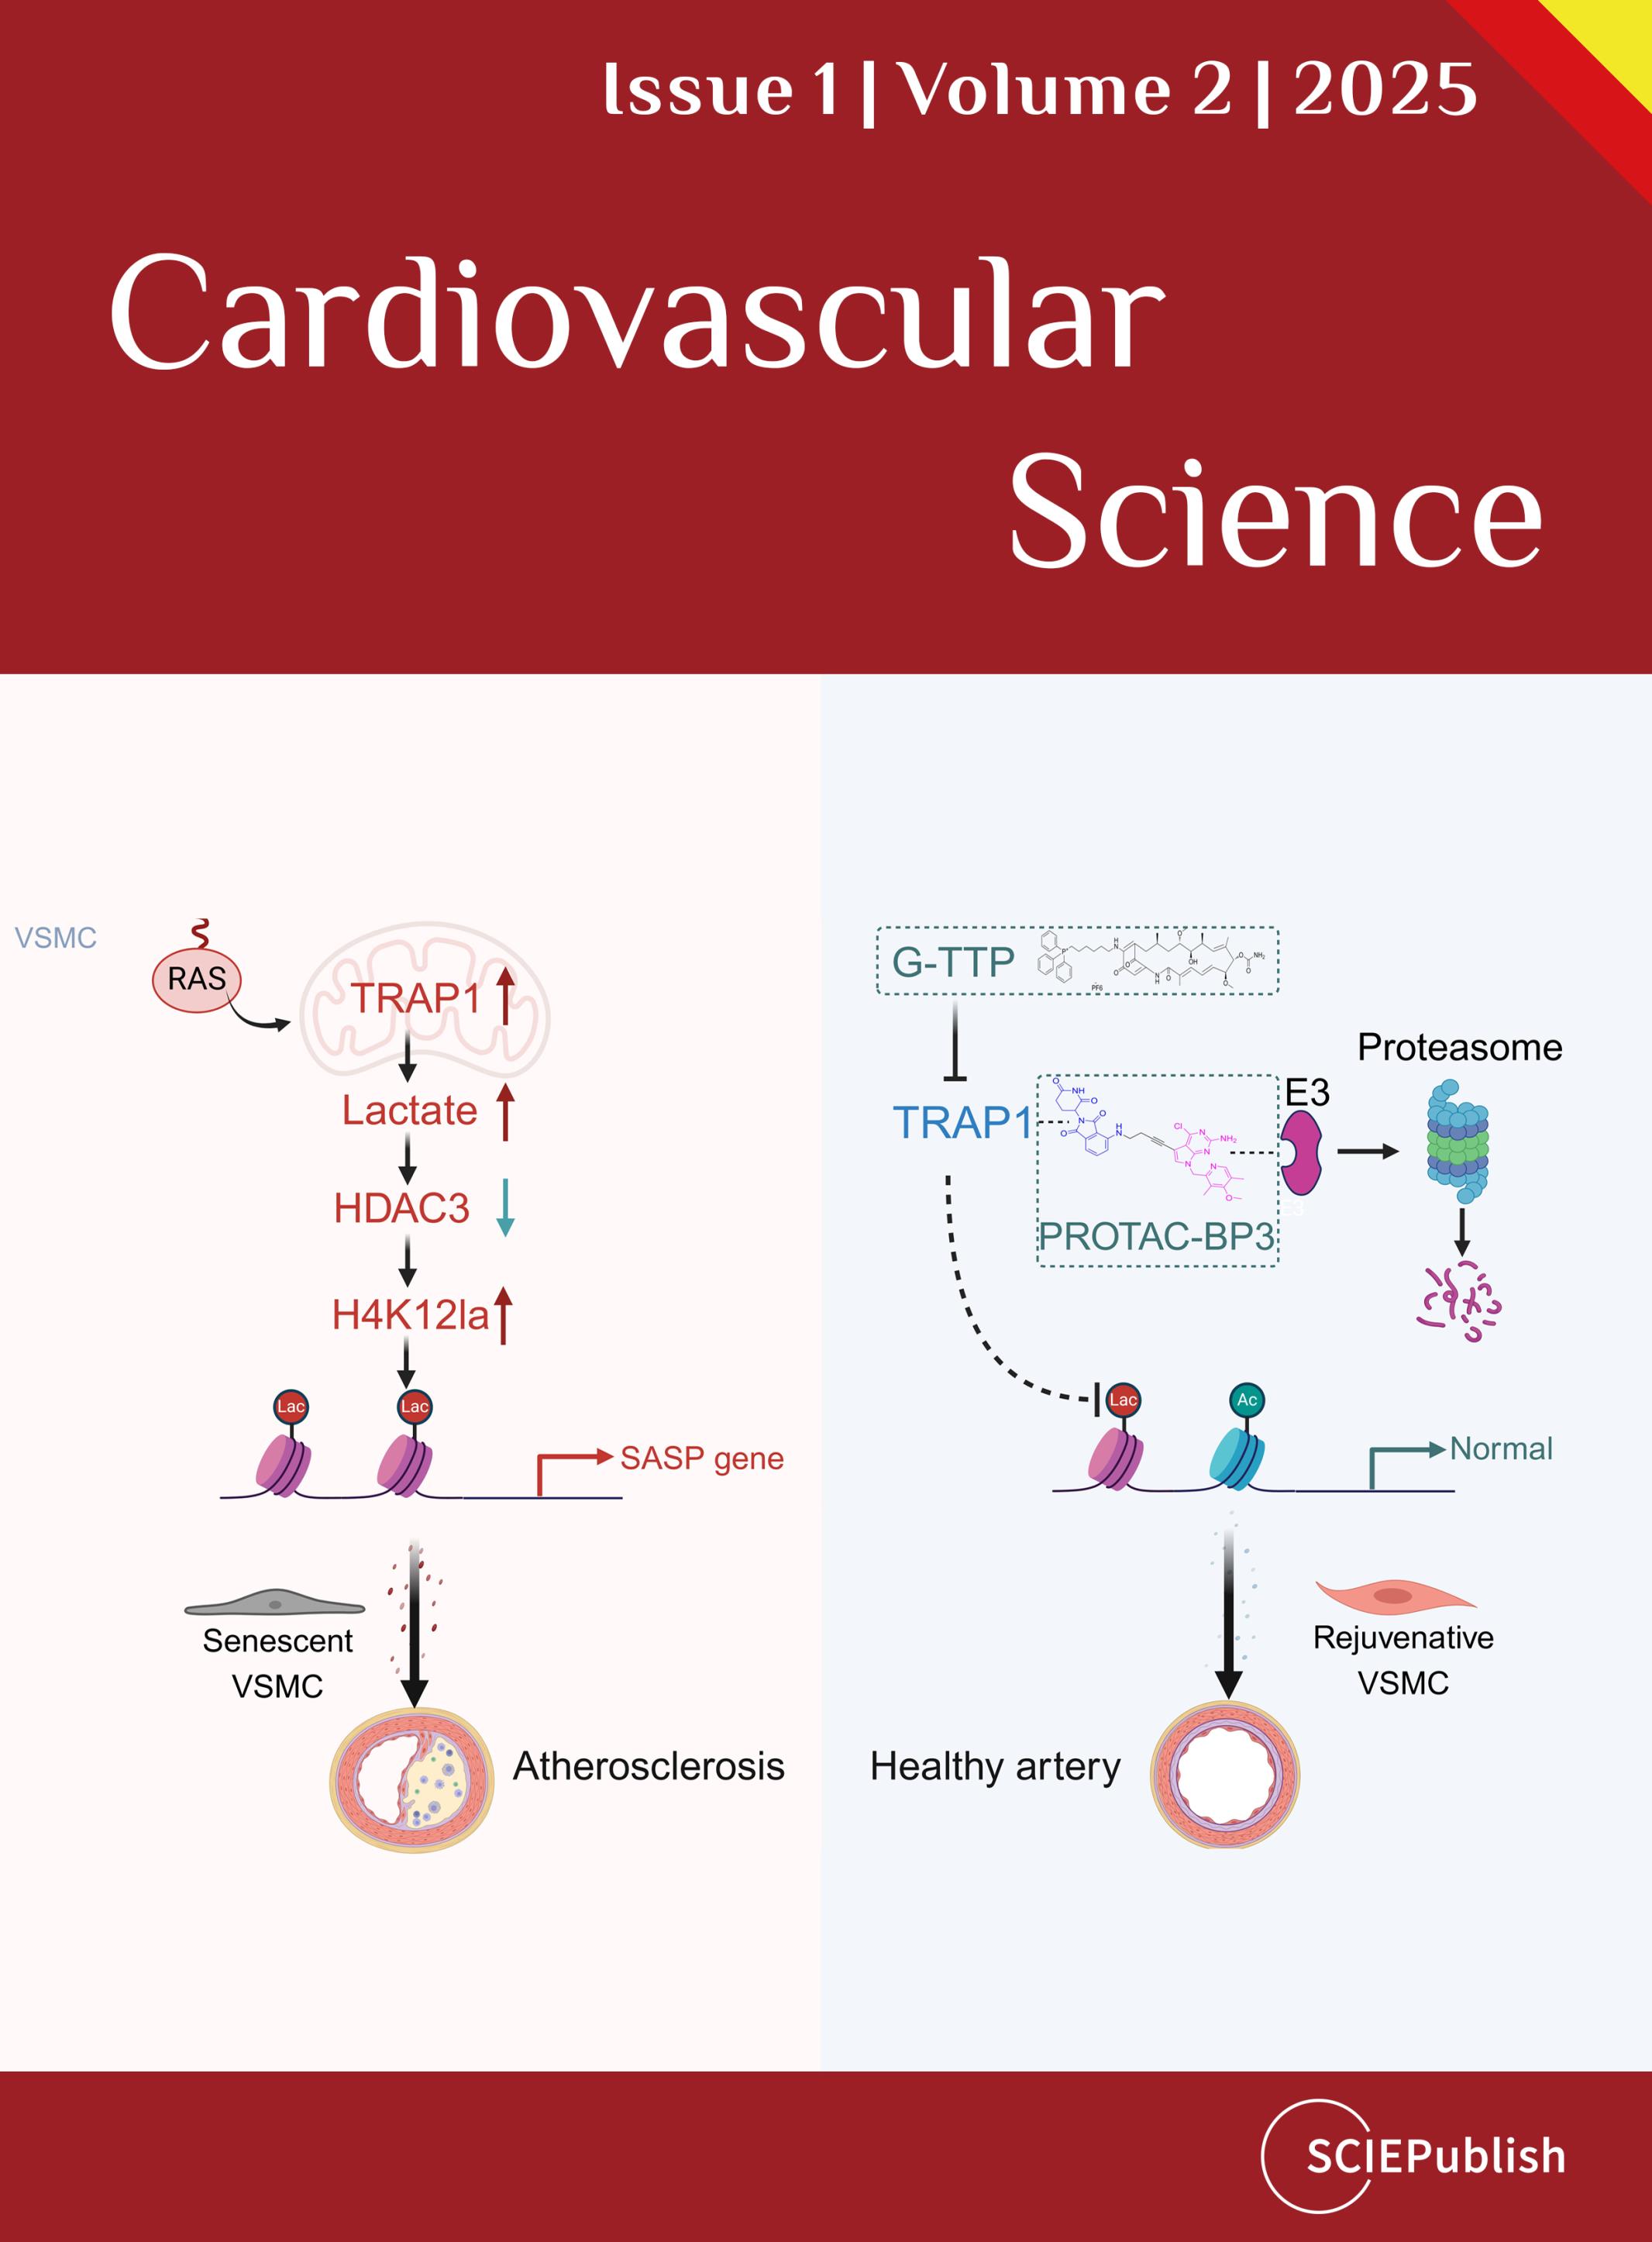
Atherosclerosis is a chronic inflammatory disease closely associated with vascular smooth muscle cell (VSMC) senescence. This Research Highlight explores the emerging role of tumour necrosis factor receptor-associated protein 1 (TRAP1) in linking metabolic reprogramming to vascular aging and atherosclerosis. By promoting the shift from oxidative phosphorylation to aerobic glycolysis, TRAP1 drives lactate accumulation and suppresses HDAC3 expression, thereby enhancing histone H4 lysine 12 lactylation (H4K12la) and activating the senescence-associated secretory phenotype (SASP). These interconnected mechanisms reveal a previously underappreciated metabolic–epigenetic pathway underlying VSMC senescence and atherosclerotic progression. Furthermore, evidence that pharmacological inhibition of TRAP1 and targeted protein degradation can alleviate atherosclerotic changes highlights promising therapeutic opportunities. This work provides valuable insights into the molecular mechanisms connecting cellular metabolism, epigenetic regulation, and vascular aging, opening new avenues for the development of targeted interventions against atherosclerosis.
Assessment of Fontan pressures during exercise has been previously challenging. We report our experience with 4 children, in whom implanted hemodynamic monitor was utilized to assess Fontan pressures during exercise. Data was used to modify treatment in one case. The device provided useful insight into exercise-related changes in Fontan patients.

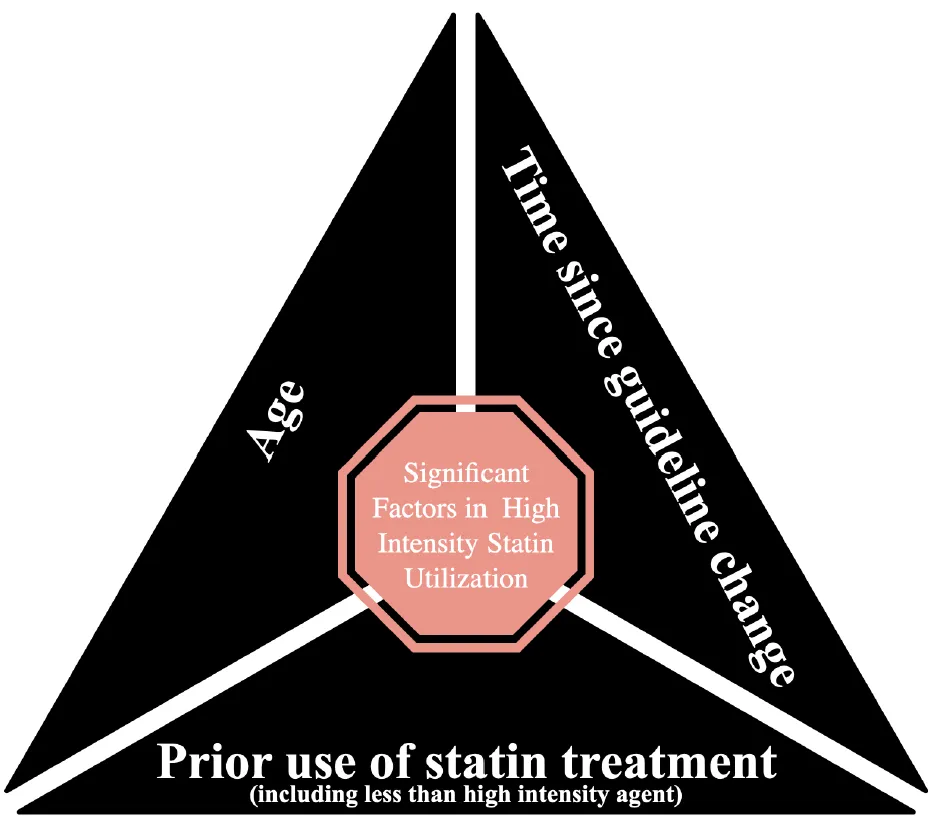
High intensity statin (HIS) therapy decreases LDL cholesterol and risk of recurrent cardiovascular events after acute myocardial infarction (MI). Recognizing the therapeutic significance of HIS, the ACC/AHA cholesterol treatment guidelines have recommended HIS for all patients following acute MI since 2013.The authors sought to define factors that result in continued underutilization and limited adherence to HIS among individuals post MI. This is a retrospective observational analysis of patients who had a diagnosis of MI between 2013 and 2018 at a single, large academic medical center. There was a significant increase in HIS prescriptions upon discharge after MI following, versus prior to 2013. Within the first year of guideline change (2013–2014), only 35.3% of patients with MI were discharged on a HIS compared to 80.1% in 2018. There was no significant difference between race or gender regarding HIS utilization. However, older age predicted a lower likelihood of being appropriately discharged on HIS. The use of statin therapy prior to hospitalization decreased the probability of being appropriately up titrated to HIS on discharge. Strikingly, HIS use was associated with a reduction in the 30-day readmission rate (4.7% versus 6.8%). Increased age was associated with lower rates of HIS use, which could stem from prior statin exposure uncovering titrational statin intolerance prior to the index event, a process that would be much less likely in younger patients, who tend to be statin naive. Although HIS have historically been underutilized in Blacks, this was not observed in the current study. Individuals discharged on HIS had lower readmission rates; while confounding factors separate from a pure treatment effect of HIS attenuating readmission rate may be represented, this remains a key finding underscoring the benefits of statin therapy in lowering societal burden of cardiovascular disease and associated costs.
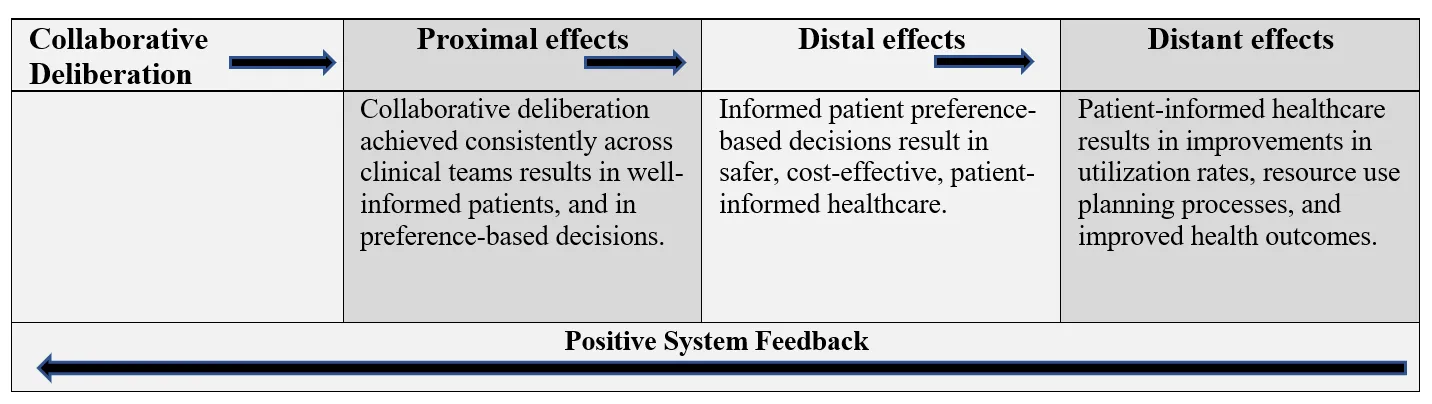
Pulmonary artery (PA) pressure can be monitored remotely by a microelectromechanical sensor (MEMS) permanently implanted in the pulmonary artery. This device allows early management of fluid overload in heart failure so that diuresis can be initiated promptly, and hospitalization and other adverse events can be prevented. To test the methods and measures proposed to explore patient and provider perceptions of Shared Decision Making for the CardioMEMS pulmonary artery pressure monitoring device. A convenience sample of eight patient-provider dyads was enrolled at an ambulatory academic cardiology clinic and completed the shared decision making questionnaire in the clinic prior to the procedure. The majority of providers reported complete agreement that shared decision making occurred. Patients’ survey responses varied but remained positive. The survey used was feasible and effective. Dyad perceptions were positive and concordant in this small convenience sample. Future studies with larger samples are needed to develop interventions to promote behaviors necessary for shared decision making.